QMed — Investor Presentation (November 2006)
54 slides from QMed's investor presentation, Nov 9, 2006

Slide 1

Slide 2: Forward-Looking Statements
tatements

Slide 3: Special Needs Plans
Special Needs Plans

Slide 4: QMed Background
QMed Background

Slide 5: QMedCare
QMedCare

Slide 6: CMS and Congress
CMS and Congress Congressional Democrats & Republicans both support SNPs = The importance of being truly “Special” = The contracting model is not in favor in Congress = SNP RAPS eliminates the artificial transfer of funds to traditional MCOs = The care model for the Medicare beneficiary is definitel

Slide 7

Slide 8

Slide 9: Medicare Modernization Act
Medicare Modernization Act = Part D — Pharmacy Benefit = RX Reimbursement for HMO’s = RAPS (Risk Adjusted Premium System) = 2006 - 75% Adjusted = 2007 - 100% Adjusted = Special Needs Plan (SNP) = Duals = Institutionalized = Chronics — CMS Approval

Slide 10: QMedCare Expansion
QMedCare Expansion HMO Expansion = Timing Considerations = HMO License = CMS Approval = New Markets = Population size / Healthcare Systems = Actuarial analysis « Reimbursement / 5% Sample

Slide 11: Subsidiary and Insurance Structure
Beg oit Ine > Subsidiary Assumes Underwriting Risk for all costs =» HMO - Certificate of Authority = Captive Insurance Company = LakeShore Captive Insurance Company « Reinsurance Alliance = ACE

Slide 12: Future Opportunities
Future Opportunities Product Offerings = C3/ RAPS Dual Eligible SNPs = Chronic Dual Eligible SNPs = SNP Partnerships

Slide 13: Early Lessons
Early Lessons

Slide 14: Jane Murray
Jane Murray

Slide 15
Slide 16

Slide 17: Keys to Enrollment
s to Enrollment = Meet the needs of hospitals = Meet the needs of physicians Meet the needs of patients = Market, market, market -- intelligently

Slide 18: Benefits to Joining
enefits to Joining

Slide 19: Physician Benefits to Joining
sician Benefits to Joining = 100% (non-discounted) Medicare rates = One Plan - A, B, D, Supplemental = One Bill — No Deductibles and No co-pays « No Patient A/Rs = No bad debt or write offs = No Referrals = Comprehensive Formulary (100% of top 100 Drugs) = Covers the ‘doughnut hole’ — Brand included

Slide 20
Slide 21: Proposition
oposition

Slide 22: Marketing Strategy
Marketing Strategy = Consumer focus groups = Key findings = Messaging = Target Part D Rx and supplemental policy holders = Lead Generation = Media = Direct Mail = Pharmacy Meetings = Community Centers = Gated Communities (NJ only) a Partnerships = Walgreen's = Medical groups = Hospital systems

Slide 23

Slide 24

Slide 25

Slide 26: QMed Experience
QMed Experience

Slide 27: Pioneers in DM
Pioneers in DM
Slide 28: Experience in Seniors
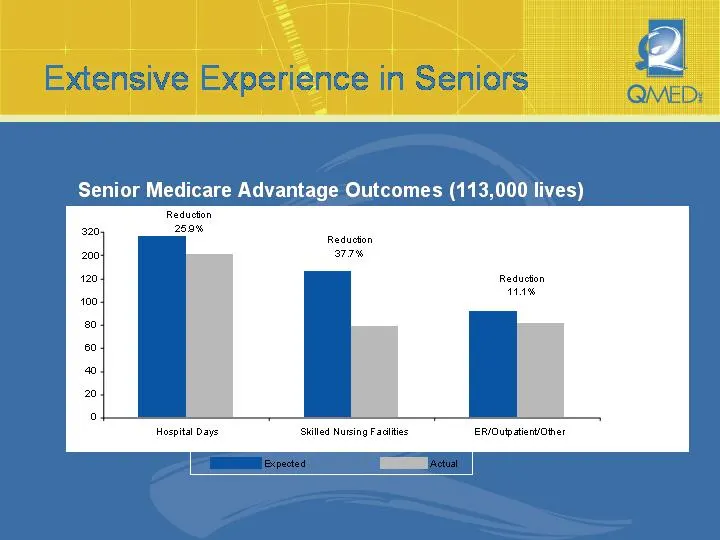
A io ence in Seniors Hospital Days Skilled Nutsing Facies Expected ‘actual ER/Oupatien/Oher
Slide 29: Evidence Based Medicine
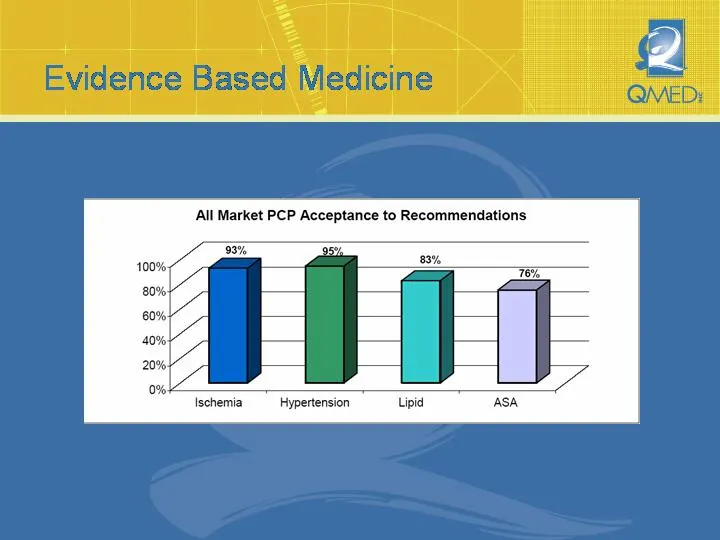
Evidence Based Medicine All Market PCP Acceptance to Recommendations 93% 7 76%, Ischemia” Hypertension Lipid ASA
Slide 30: Evidence Based Medicine
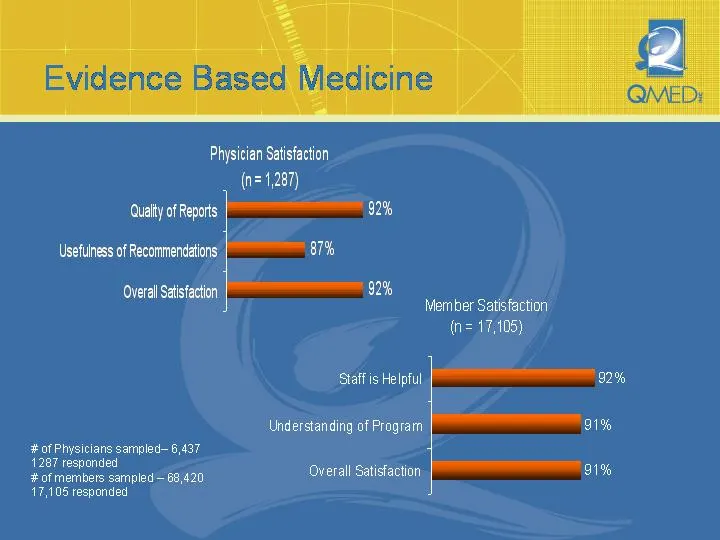
Evidence Based Medicine Physician Satisfaction (n= 1,287) Quaity of Reports 92% Usefulness of Recommendations 87% Overal Satisfaction 92% Member Satisfaction (n= 17,105) Staff is Helpful 92% Understanding of Program 91% +# of Physicians sampled 6,437 1287 responded f gamates areca Overall Satisfacti
Slide 31: Care Management Engine
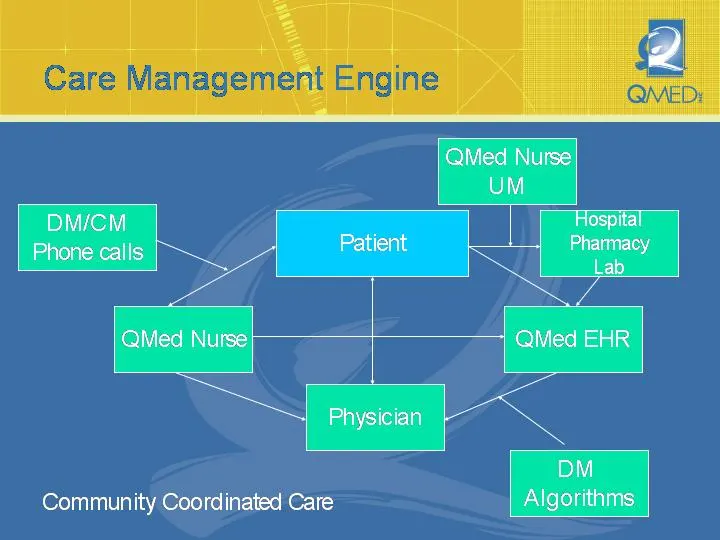
Care Management Engine QMed Nurse UM DM/CM Hospital Phone calls Patient Bh Pharmacy Lab Cee Ise QMed EHR Physician DM Community Coordinated Care Algorithms

Slide 32: Disease States Managed
Disease States Managed Health Promotion and Prevention Coronary Artery Disease Heart Failure Diabetes Hypertension Stroke COPD and Asthma Hyperlipidemia Obesity/Weight Management
Slide 33: DM Algorithm
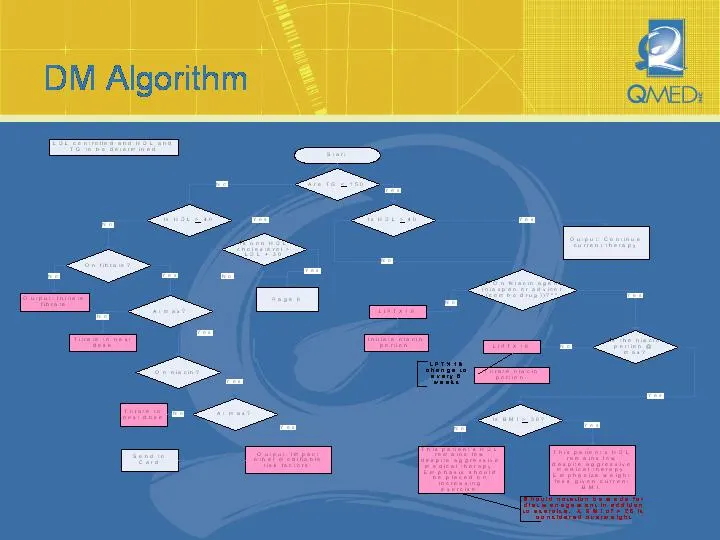
DM Algorithm

Slide 34: Benefits of Optimal Management
Benefits of Optimal Management = Decrease healthcare utilization = Optimize healthcare utilization
Slide 35: So, How are we doing
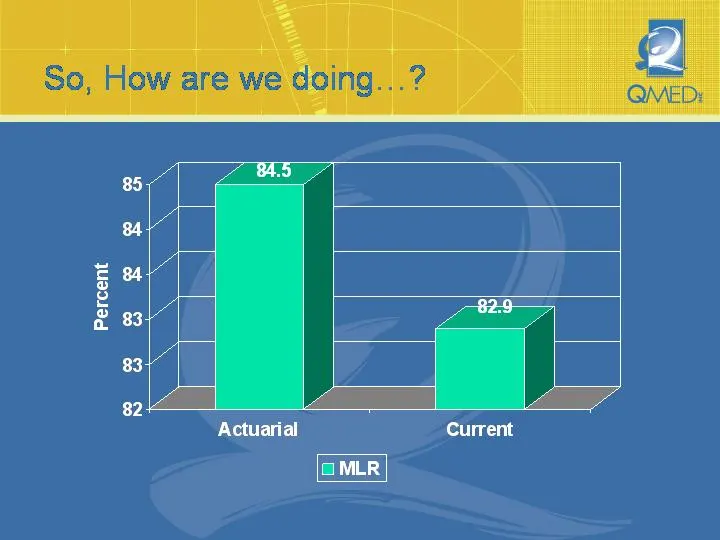
So, How are we doing Percent 82 5 Actuarial OMLR Current
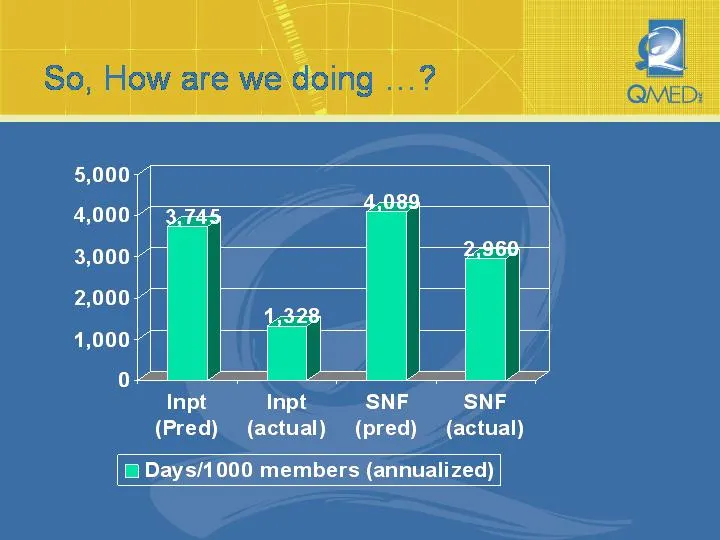
Slide 36: So, How are we doing ...?
So, How are we doing ...?
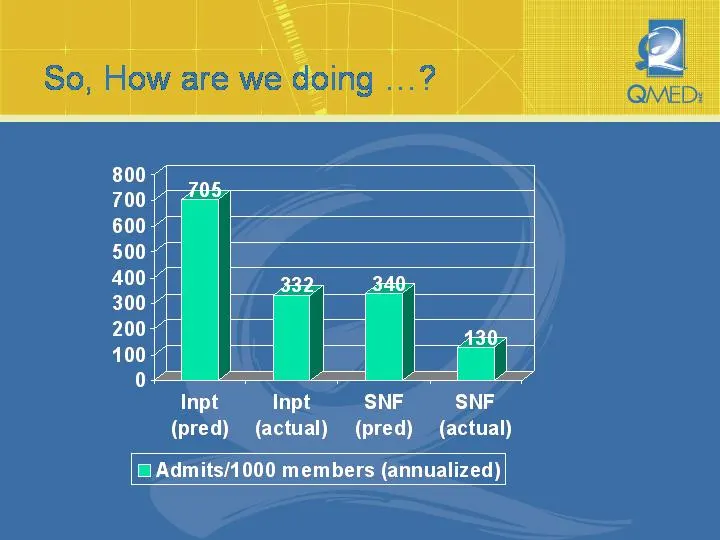
Slide 37: So, How are we doing ...?
So, How are we doing ...?
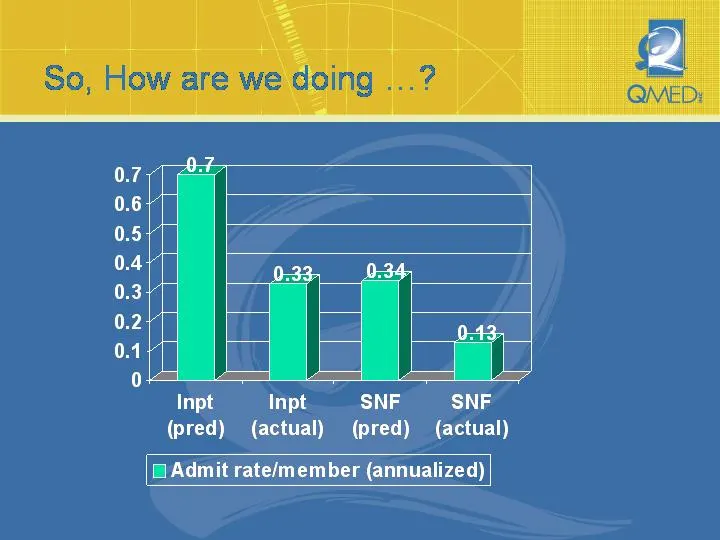
Slide 38: So, How are we doing ...?
So, How are we doing ...? Inpt Inpt SNF SNF (pred) (actual) (pred) (actual) Admit rate‘member (annualized)

Slide 39: So, How are we doing ...?
So, How are we doing ...?
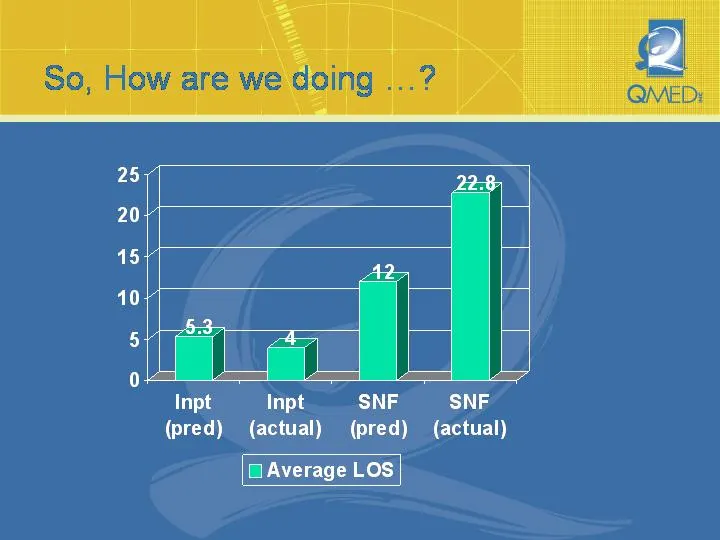
Slide 40: So, How are we doing ...?
So, How are we doing ...? 5 vf io 4 2 Inpt Inpt SNF SNF (pred) (actual) (pred) (actual) G Average LOS
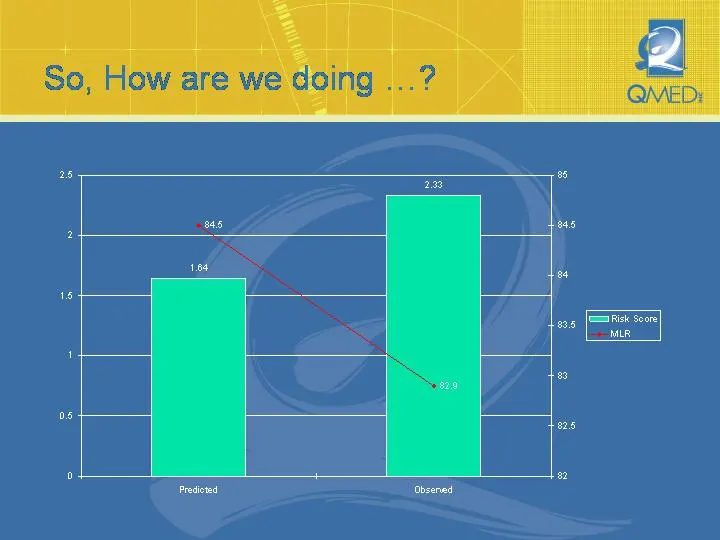
Slide 41: So, How are we doing
So, How are we doing 25 85 _ 845 eas 4 [Sariax Soore __ MUR 2 os Predicted ‘Obeered
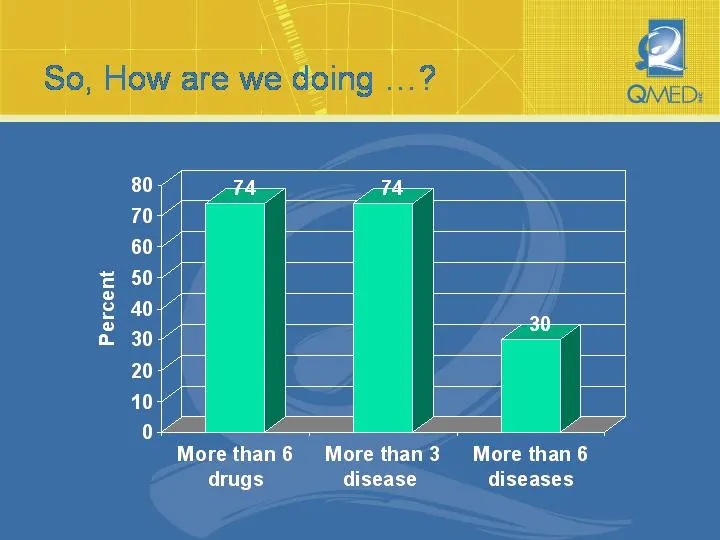
Slide 42: So, How are we doing ...?
So, How are we doing ...? 80 70 60 50 40 30 20 10 0 Percent Morethan6 Morethan3 More than6 drugs disease diseases

Slide 43

Slide 44

Slide 45: Transition From Vendor to SNP
Transition From Vendor to SNP = Risks as a middleman = Industry consolidation = Internalizing of DM functions = Aggregator of Premium = Section 231 paves the way = RAPS accelerates top line = Greater Long-Term Growth Opportunities = C-SNPs South Dakota Chronic & Duals = New Jersey: Chronics In4 Coun
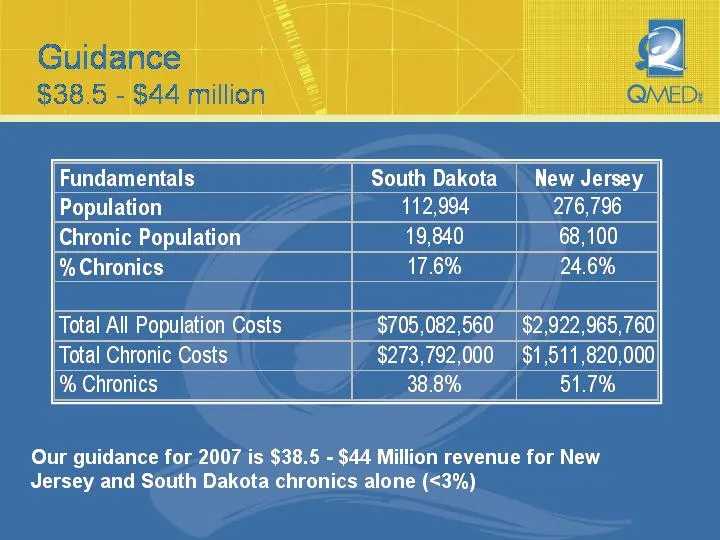
Slide 46: Guidance
Guidance

Slide 47: Transition Progress
Transition Progress

Slide 48: Requirements
Requirements = Reserve Requirements = Captive insurance company Ratio 10 -1 requirement » NJHMO 300% Risk Based Capital requirement = Due Diligence by New Jersey Department of Banking & Insurance = Meet reserve needs and financial stability

Slide 49: Infrastructure Progress
Infrastructure Progress

Slide 50

Slide 51: QMedCare Conclusion
QMedCare® Conclusion

Slide 52: Investment Perspective
Investment Perspective
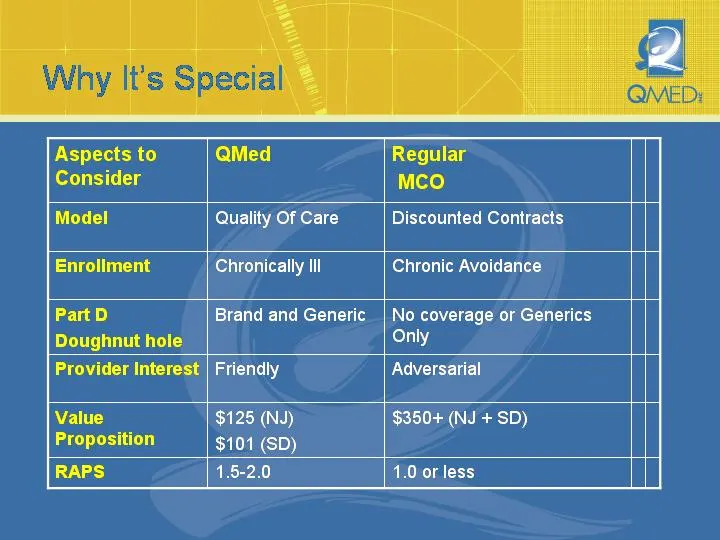
Slide 53: Why It's Special
Why It's Special

Slide 54
Source: SEC EDGAR · 8-K filed Nov 9, 2006

