Health Net — Investor Day (February 2010)
64 slides from Health Net's investor day presentation, Feb 11, 2010

Slide 1: Health Net, Inc. 2010 Investor Day
Health Net, Inc. Health Net, Inc. 2010 Investor Day 2010 Investor Day February 11, 2010 Exhibit 99.1

Slide 2: Cautionary Statement
Cautionary Statement All statements in this presentation, other than statements of historical information provided herein, including but not limited to the guidance for future periods included herein and the assumptions and underlying such projections, may be deemed to be forward-looking statements

Slide 3: Non-GAAP Measures
Non-GAAP Measures These presentations include quarterly and full-year income statement measurements that are not calculated and presented in accordance with Generally Accepted Accounting Principles. Audience participants should refer to the reconciliation table included in the Appendix to the presen

Slide 4: Overview
Health Net, Inc. Health Net, Inc. 2010 Investor Day 2010 Investor Day Overview Overview Jay Gellert President and Chief Executive Officer

Slide 5: 2009 Summary
2009 Summary Improve Medicare performance Solidify commercial base Close Northeast transaction Strengthen balance sheet Strong TRICARE performance Position for the future

Slide 6: Our Positioning
Our Positioning Commercial product approach Diverse portfolio, consistent performance DoD / VA franchise Simplified administration and medical management Available cash

Slide 7: Aligned with Environment
Aligned with Environment New face of consumer Ongoing affordability pressures Not overinvested in high risk areas Leverage with economic recovery Opportunities from reform

Slide 8: To Do Today
To Do Today Comfortable with 2010 Approach that leads into 2011 Administrative savings line of sight Can handle TRICARE transition Have cash, will use it wisely Longer term margin expansion opportunities Well-positioned for the future

Slide 9: 2010 Earnings Guidance
2010 Earnings Guidance 2010 Earnings Guidance Year-end Membership Commercial: -1% to -2% Medicaid: +5% to +6% Medicare Advantage: -2% to -3% PDP: +1% to +2% Consolidated Revenues $13 billion to $13.5 billion Commercial Premium Yields (b) ~ 8.3% to 8.8% (Western Region 2009: ~$316 PMPM) Commercial He

Slide 10: Earnings Guidance Bridge 2009-2010
Earnings Earnings Guidance Guidance Bridge Bridge 2009-2010 2009-2010 (a) (a) Expect pretax margin to improve by ~60 basis points G&A ratio to improve by 70 to 90 basis points Health plan MCR to rise by ~20 basis points Selling costs improve by ~30 basis points Government contracts cost ratio flat N

Slide 11: Our Goal
Our Goal Simple Transparent Aligned Tailwinds over headwinds Flexible

Slide 12: Operations Review
Operations Review Operations Review Jim Woys Executive Vice President and Chief Operating Officer

Slide 13: 2010 and Long-Term Focus
2010 and Long-Term Focus 2010 and Long-Term Focus Expand Western commercial revenues and margins Sustain Medicare membership and margins “Stay the course” in Medi-Cal Maintain and then grow Government contracts Manage health care costs in a capitated group setting Reduce administrative expenses to d

Slide 14: Commercial Business
Commercial Business Commercial Business Steven Sell President, Western Region Health Plan President, Health Net of California

Slide 15: Commercial Plan: Build on Strength
Commercial Plan: Build on Strength Commercial Plan: Build on Strength Strong California HMO position – Gaining market share Strategically changing the mix – Geographies, small and mid-market and low cost products – Positioned for changes in the market Build on provider relationships – Multiple netwo
Slide 16: The New and Improved HMO
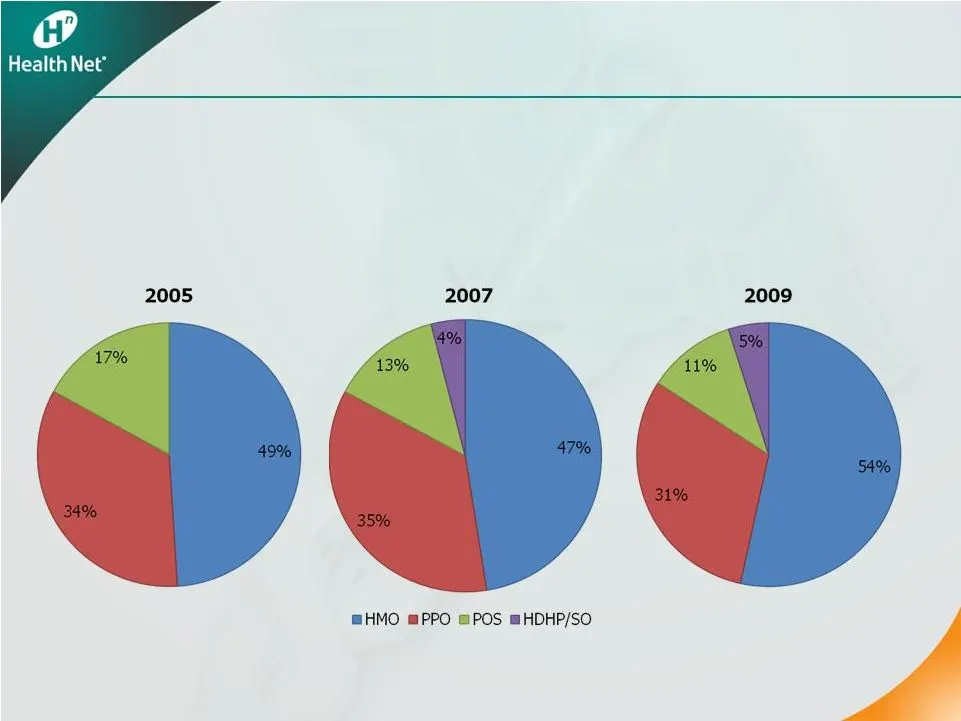
The New and Improved HMO The New and Improved HMO HMO strong in California HDHP growth has changed little since 2007 CA Commercial Market Share by Product Type Sources: California Health Care Foundation (CHCF)/NORC California Employer Health Benefits Survey: 2007-2009, 2005-2006, 2004, Kaiser/HRET C
Slide 17: Health Net Strong in Commercial HMO
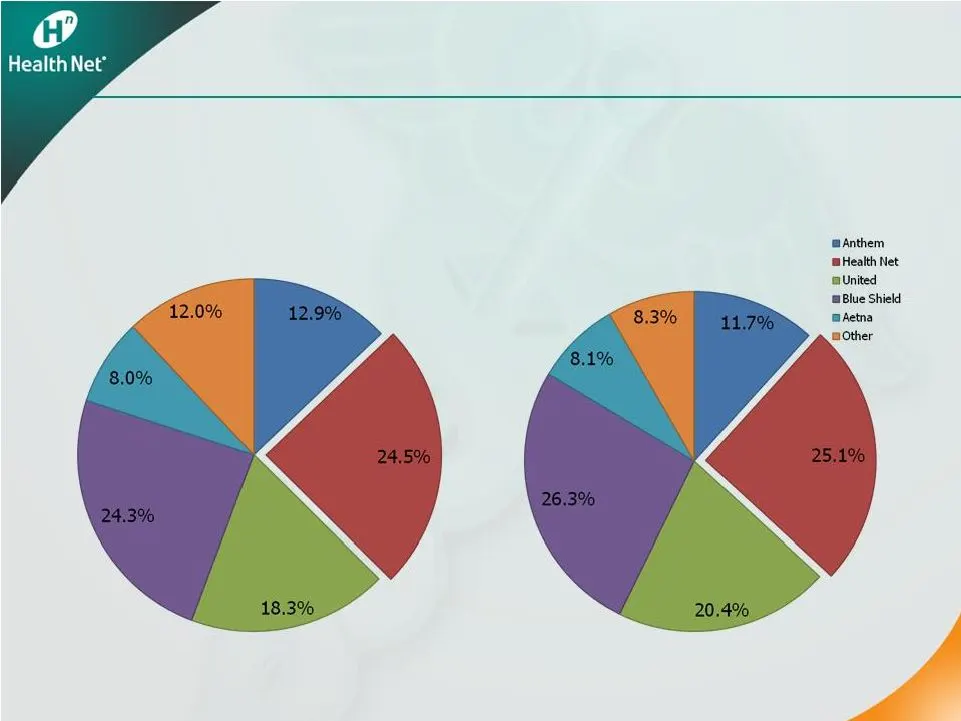
2009 Health Plan Market Share in CA (Commercial HMO/POS) Network HMO 2009 Health Plan Market Share in Inland Empire, Los Angeles, and Orange County (Commercial HMO/POS) Network HMO Health Net Strong in Commercial HMO Health Net Strong in Commercial HMO Note: Commercial HMO/POS excludes self-funded m

Slide 18: The New and Improved HMO
The New and Improved HMO The New and Improved HMO Integrated provider groups provide cost stability and predictability Low cost products meet “value shopper” needs Comprehensive benefits at competitive price points Prices for high deductible, consumer-directed products rising substantially Up to 40
Slide 19: Group Networks: Our Sweet Spot
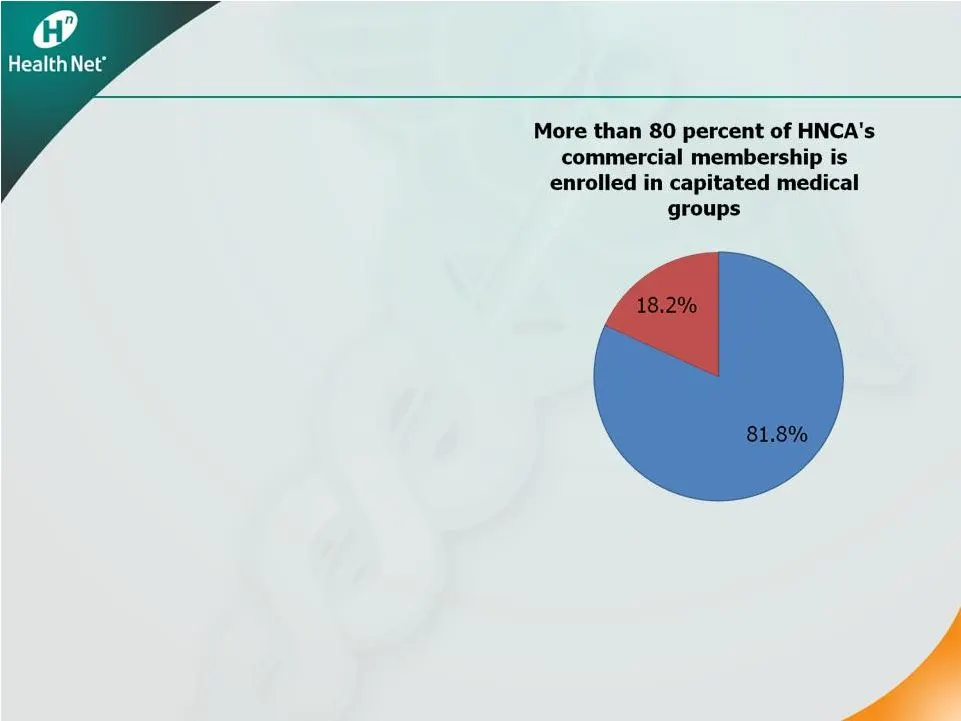
Group Networks: Our Sweet Spot Group Networks: Our Sweet Spot A staple of Western markets Health Net is the lead network model HMO player * More penetrated landscape in Southern California – Health Net’s best geography The most cost-effective delivery system – Reduces risk * Based on membership

Slide 20: The Value of the Group Model
The Value of the Group Model The Value of the Group Model More predictable costs and pricing Integrates care and avoids duplicative or unnecessary procedures Care starts at low cost setting, “steps-up” only as necessary Collaborate on cost and quality initiatives

Slide 21: Economy Driving to Affordable Products
Economy Driving to Affordable Products Economy Driving to Affordable Products Affordability issues – need for lower cost products – Small and mid-market Two approaches to lower cost products: – Narrow network products are growing – Consumer-driven, high deductible products not producing promised sav
Slide 22: Strength: Narrow Network Products
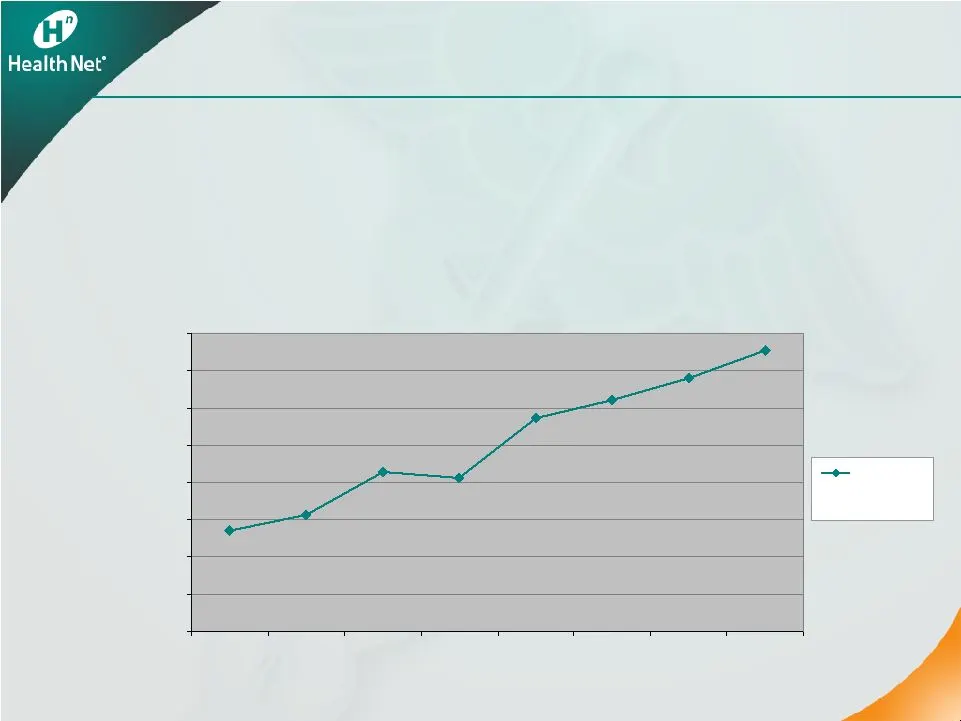
Strength: Narrow Network Products Strength: Narrow Network Products Steady growth in all narrow network products Success with a growing Latino population Growing interest in substantive coverage in lieu of broad access Health Net Narrow Network Products Membership 200,000 210,000 220,000 230,000 240

Slide 23: Strength: Small Group Segment
31% 36% 38% 69% 64% 62% 0% 20% 40% 60% 80% 100% Q1-2007 Q1-2008 Q1-2009 Small Group Network Model HMO Market Share Health Net has continued to gain market share in small groups in network model HMO from 1Q07 to 1Q09 (1) Strength: Small Group Segment Strength: Small Group Segment HNT small group memb

Slide 24: Expanding Gross Margin
Expanding Gross Margin Expanding Gross Margin Disciplined pricing – 20 to 40 basis points MCR improvement Segment shift to small and mid-markets Mix shift to narrow network products Geographic shift to profitable regions

Slide 25: Winning Strategy for Today's Market
Winning Strategy for Today’s Market Winning Strategy for Today’s Market Strong California HMO position Built on strong provider group relationships Change the mix to small and mid-group, lower costs and key geographies Sustained disciplined pricing Result: steady margin improvement

Slide 26: Medicare & State Programs
Medicare & Medicare & State Programs State Programs Scott Kelly Chief Government Programs Officer

Slide 27: Medicare Positioning
Medicare Positioning Medicare Positioning Focus on network model markets in Western region – Established and accepting of MA since before BBA – Best “age-in” opportunities Build on strength of capitated networks in California Balance cost, revenue and benefits/premiums to maintain margins in challen
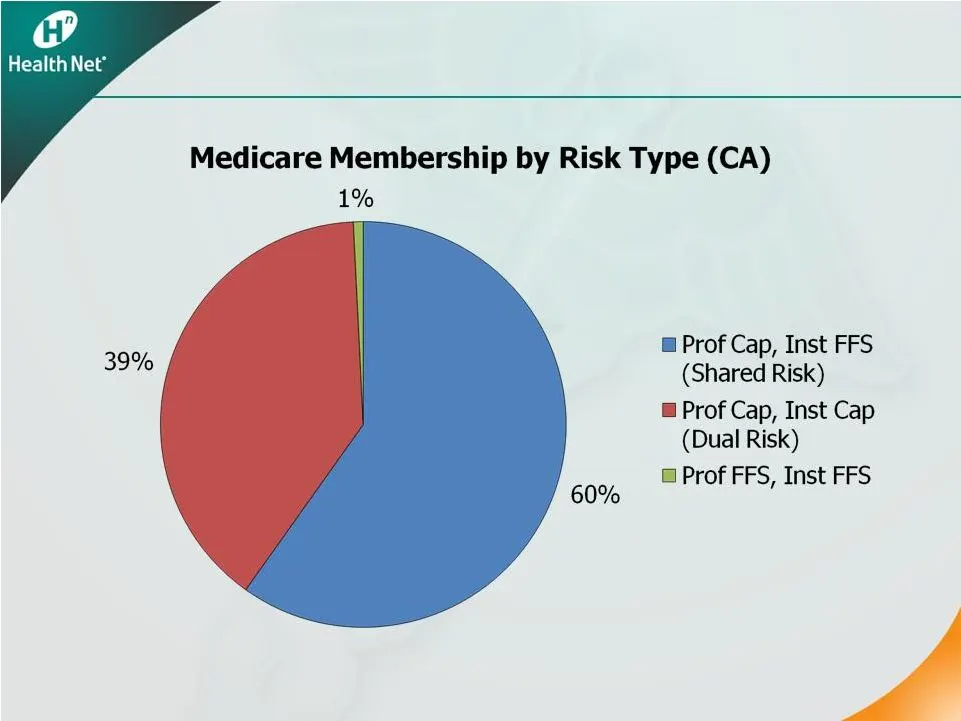
Slide 28: Medicare Membership by Risk Type (CA)
rH Health Net® Medicare Membership by Risk Type (CA) 1% @ Prof Cap, Inst FFS (Shared Risk) @ Prof Cap, Inst Cap (Dual Risk) @ Prof FFS, Inst FFS 39% 60%

Slide 29: Medicare Advantage 2009
Medicare Advantage 2009 Medicare Advantage 2009 Met goals in 2009 Emphasized margin with reasonable growth – Risk mitigation Improvement driven by targeted benefit and premium changes Improved risk adjuster data collection Stable enrollment – Exited Private Fee-for-Service

Slide 30: Medicare Advantage: 2010 Expectations
Medicare Advantage: 2010 Expectations Medicare Advantage: 2010 Expectations Early enrollment results positive MCR expected to improve Premium and benefit design Exit Private Fee-for-Service Margins consistent with long-term targets

Slide 31: Medicare Part D
Medicare Part D Medicare Part D Solid franchise 2009 enrollment slightly better than expected Returned to solid margins 2010 enrollment expected to increase 1 to 2 percent 2010 margins consistent with long-term targets

Slide 32: State Programs: Medi-Cal
State Programs: Medi-Cal State Programs: Medi-Cal Highest ranking HMO plan in California by U.S. News and World Report 702,000 members at year-end 2009, an increase of 12.5 percent year-over-year 2010 outlook – Expect 5 to 6 percent membership growth – Continued rate pressure – Continued provider pa
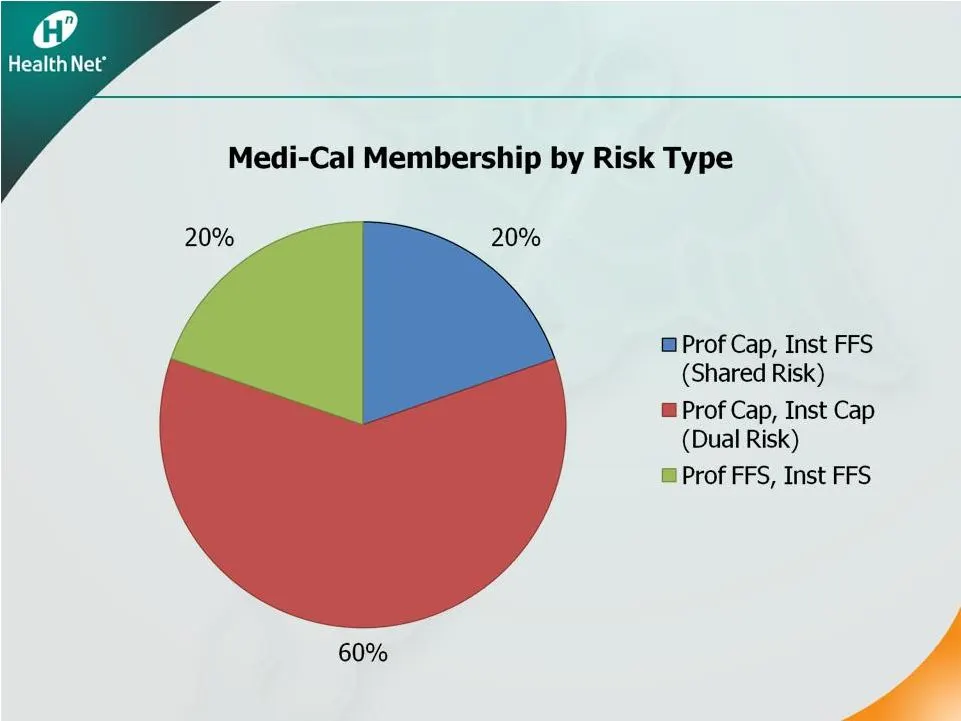
Slide 33: Medi-Cal Membership by Risk Type
rH Health Net® Medi-Cal Membership by Risk Type 20% 20% @ Prof Cap, Inst FFS. (Shared Risk) @ Prof Cap, Inst Cap (Dual Risk) @ Prof FFS, Inst FFS 60%

Slide 34: State Programs: Healthy Families
State Programs: Healthy Families State Programs: Healthy Families 153,000 members at year-end 2009, an increase of 10.3 percent year-over-year 2010 program outlook – Expect 5 to 6 percent membership gains – Continued rate pressure – Margin stability

Slide 35: Key Takeaways
Key Takeaways Key Takeaways Strong 2009 Medicare results lead to solid 2010 outlook based on benefits, premiums and enrollment Medicare margin stability in long-standing MA network-model markets – Predictable cost structure Maintain Medi-Cal stability and position in advance of health care reform –

Slide 36: Government Segment
Government Segment Government Segment Federal Services / MHN Federal Services / MHN Steve Tough President, Government Programs Division

Slide 37: 2009 Review and 2010 Outlook
2009 Review and 2010 Outlook 2009 Government contracts ratio of 94.6 percent – Better than planned due to lower health care cost trends and DoD behavioral health growth 2010 Expectations – Current TRICARE contract and terms to continue through March of 2011 – Revenue growth of approximately 10 perce

Slide 38: Status of TRICARE Award Protest
Status of TRICARE Award Protest GAO sustained Health Net’s protest Appearance of “conflict of interest” Evaluation of provider discounts GAO concluded errors could have impacted the DoD agreed to consider “conflict” issue first Awaiting next steps from DoD relative standing of the proposals

Slide 39: MFLC: DoD Behavioral Health Program
MFLC: DoD Behavioral Health Program Substantial year-over-year revenue growth, with 2009 revenues of more than $200 million More than 1,500 consultants at approximately 300 locations worldwide seeing over 1 million encounters per month Expect to achieve 2010 growth – Increasing demand for services (
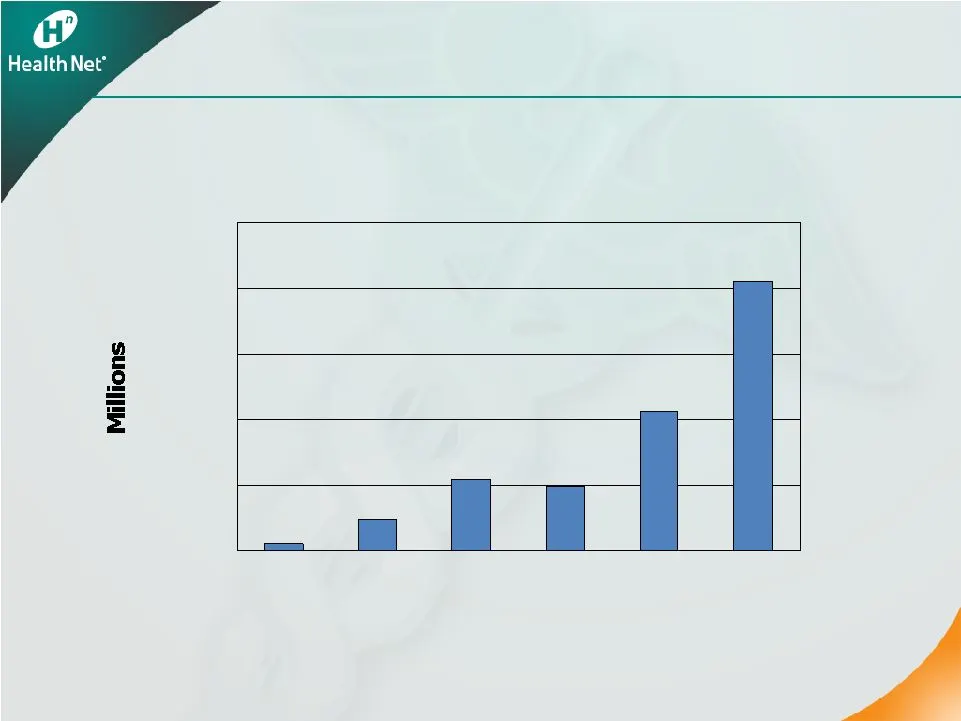
Slide 40: MFLC Program Revenue
MFLC Program Revenue MFLC Program Revenue $0 $50 $100 $150 $200 $250

Slide 41: Future Opportunities
Future Opportunities Department of Veterans Affairs Department of Defense – MFLC expansion Other government and commercial entities – Customized Behavioral Health & EAP for targeted market segments, including: Colleges and universities / student health Federal agencies Correctional health

Slide 42: Health Care Cost Management
Health Care Cost Health Care Cost Management Management John Sivori Health Care Services Officer

Slide 43: Health Care Cost Management
Health Care Cost Management 2009 commercial trends higher than initial expectations – H1N1 and COBRA Significant progress in network contracting Better management of trend is key element of long-term margin expansion Longer term opportunities with established capitated provider relationships – More

Slide 44: Expectations
Expectations Expect commercial costs to be 20 to 40 basis points better than premium yields Stable physician (~6 percent) and inpatient (~10 percent) trends Moderating outpatient trends (~12 percent) Lower Rx trends compared with 2009 (~10 percent) Assuming abatement in flu COBRA impact included in

Slide 45: Medical Management in a Capitated Group Setting
Medical Management in a Capitated Group Setting Focus on provider groups that optimize cost effectiveness and quality – Understand local delivery system issues – Influence with physician community – Support for complex management Offer tools and resources to providers for improved performance Target

Slide 46: Execution on the Basics
Execution on the Basics Care management – Active evidence-based interventions – Integrated with delegated providers and vendors Complex case management – Enroll the sickest and most complicated patients Monitor key measures – Inpatient days per thousand – ER visits per thousand – Re-admits

Slide 47: Provider Contracting Update
Provider Contracting Update Completed more than 80 percent of 2010 contracts on dollar-spend basis – 90 percent completed in California Expand cost-effective narrow network solutions with key provider groups ( Salud , Silver, Bronze) Enhance partnerships with key hospital systems Renew physician awa

Slide 48: Pharmacy Cost Management
Pharmacy Cost Management Utilization trends moderating Unit costs an area of focus 2009 impact from H1N1 flu Captive PBM allows aggressive formulary management Integrated specialty management Success with generics

Slide 49: Pharmacy Performance
Pharmacy Performance Industry-leading generic fill rate (72 percent in 2009 in Western health plans) Continued improvement in generic fill rate Key driver of overall trend management to near single digits for the last eight years

Slide 50: Key Takeaways
Key Takeaways Leveraging existing provider relationships to deliver products and a cost structure that meets customer needs Delegated model recognized as vehicle for cost containment Focused on improved execution of the basics in 2010

Slide 51: Operational Efficiency
Operational Efficiency Operational Efficiency Jim Woys Executive Vice President and Chief Operating Officer

Slide 52: Operations Strategy Rationale
Operations Strategy Rationale Operations Strategy Rationale 2007: cost structure inefficient and expensive 2009: repositioned G&A – efficient and cost- effective Improved operating performance The majority of key metrics in claims, call center and enrollment have shown year-over-year improvement Lon

Slide 53: Operations Strategy Results
Operations Strategy Results Operations Strategy Results A “high return” investment – Achieved more than $125 million in run-rate G&A savings since 2007 Operations strategy nearly complete – Application and infrastructure outsourcing and systems efficiencies: $53 million in run-rate savings – Busines

Slide 54: Operations Strategy Investments
Operations Strategy Investments Operations Strategy Investments Necessary charges of $191 million pretax to-date, with further charges of $16 million pretax in 2010 as headcount continues to decline – $43 million for noncash asset write-downs – $88 million for severance due to headcount reductions –
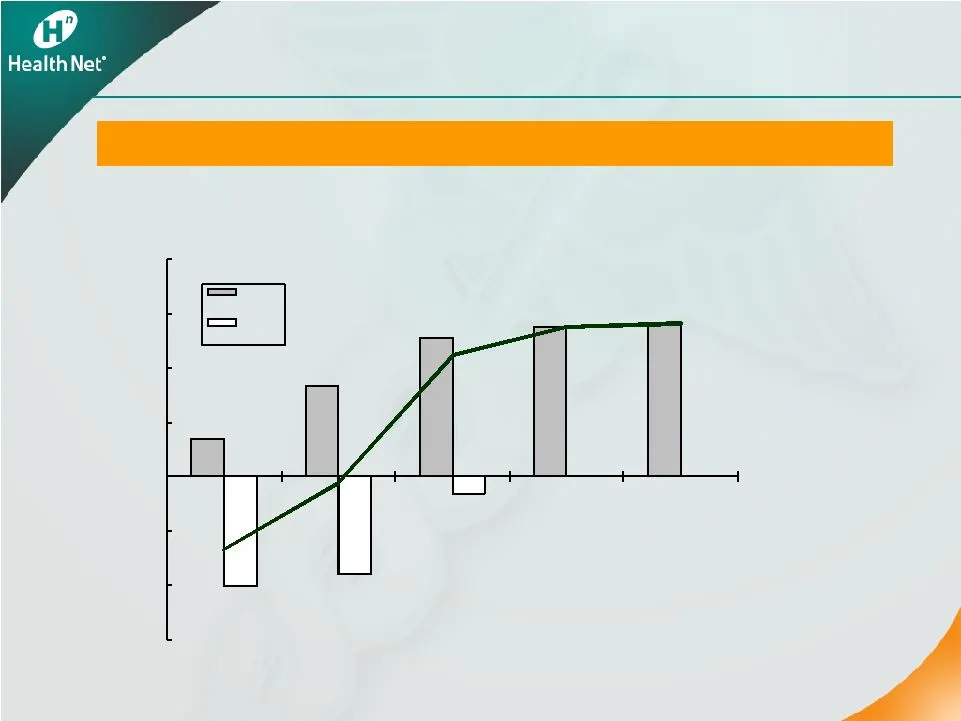
Slide 55: Ongoing savings exceed investments
Ongoing savings exceed investments Operations Strategy Results Operations Strategy Results Total charges = $207 million pretax Positive return realized in second half of 2010 Operations Strate g y Savin g s vs. Char g es $'s in millions -$150 -$100 -$50 $0 $50 $100 $150 $200 Savings Charge

Slide 56: Overhead Reductions
Overhead Reductions Overhead Reductions Further administrative cost savings necessary with Northeast sale Expect to achieve savings by reducing corporate overhead Eliminate $80 million to $100 million in run-rate G&A expenses by year-end 2011 New G&A base will be scalable as growth resumes

Slide 57: 2010 and Long-Term Focus
2010 and Long-Term Focus 2010 and Long-Term Focus Expand Western commercial revenues and margins Sustain Medicare membership and margins “Stay the course” in Medi-Cal Maintain and then grow Government contracts Manage health care costs in a capitated group setting Reduce administrative expenses to d

Slide 58: Financial Review
Financial Review Financial Review Joseph C. Capezza Executive Vice President and Chief Financial Officer

Slide 59: On the Right Track
On the Right Track On the Right Track Completed Northeast transaction Met 2009 expectations Fixed Medicare Contributed $100 million to subsidiaries in December RBC more than percent Strong cash at parent $450 million at year-end 2009 Expect 2010 cash flow of $300 million to $325 million

Slide 60: Northeast Transaction Cash
Northeast Transaction Cash Northeast Transaction Cash $377 million $ 23 million $ 90 million to $210 million Total $490 to $610 million

Slide 61: 2010 Cash Uses
Retained regulatory capital ~$ 90 million Debt repayment ~$140 million Share repurchase ~$ 90 million * Severance, capital expenditures and other expenses ~$ 80 million TOTAL ~$400 million * Assumes share repurchases equal to current authorization of approximately $103 million. 2010 Cash Uses 2010 C

Slide 62: Capital Summary
Capital Summary Capital Summary Parent cash 12/31/10 ~$350 million Revolver capacity 12/31/10 ~$485 million Additional Northeast payments ~$90 million to $210 million Total debt 12/31/10 ~$475 million

Slide 63: 2010 Earnings Guidance
2010 Earnings Guidance 2010 Earnings Guidance Year-end Membership Commercial: -1% to -2% Medicaid: +5% to +6% Medicare Advantage: -2% to -3% PDP: +1% to +2% Consolidated Revenues $13 billion to $13.5 billion Commercial Premium Yields ~ 8.3% to 8.8% Commercial Health Care Cost Trends ~ 20-40 bps < Pr

Slide 64: Appendix: Reconciliation of Non-GAAP Financial Measures
Health Net, Inc. Health Net, Inc. 2010 Investor Day 2010 Investor Day Appendix Appendix February 11, 2010 Health Net, Inc. Reconciliation of Non-GAAP Financial Measures Operating Results Excluding Charges (Amounts in thousands, except per share, PMPM and ratio data) This table presents the company’s
Source: SEC EDGAR · 8-K filed Feb 11, 2010
More decks from Health Net Inc
 Q2 2015 Earnings Presentation25 slides · Sep 23, 2015
 SPAC Merger (July 2015)18 slides · Jul 15, 2015
 SPAC Merger (July 2015)18 slides · Jul 14, 2015
 Merger or Acquisition (July 2015)13 slides · Jul 2, 2015
 Investor Day (February 2012)74 slides · Feb 16, 2012
 30th Annual J.P. Morgan Healthcare Conference (January 2012)13 slides · Jan 9, 2012