Lisata Therapeutics, Inc. · NASDAQ:LSTA
Lisata Therapeutics — Marea Therapeutics — Investor Presentation (November 2026)
22 slides from Lisata Therapeutics's investor presentation, November 2026

Slide 1: Marea Therapeutics: Transformative cardioendocrine therapies
November 2026 Marea Therapeutics Transformative cardioendocrine therapies ©2023 Marea Therapeutics 1

Slide 2: Forward Looking Statements & Disclaimers
Forward Looking Statements & Disclaimers This presentation contains forward-looking statements. Such statements include, but are not limited to, statements regarding Marea Therapeutics, Inc.’s (“Marea,” the “Company,” “we,” “us” or “our”) research, preclinical and clinical development activities, pl
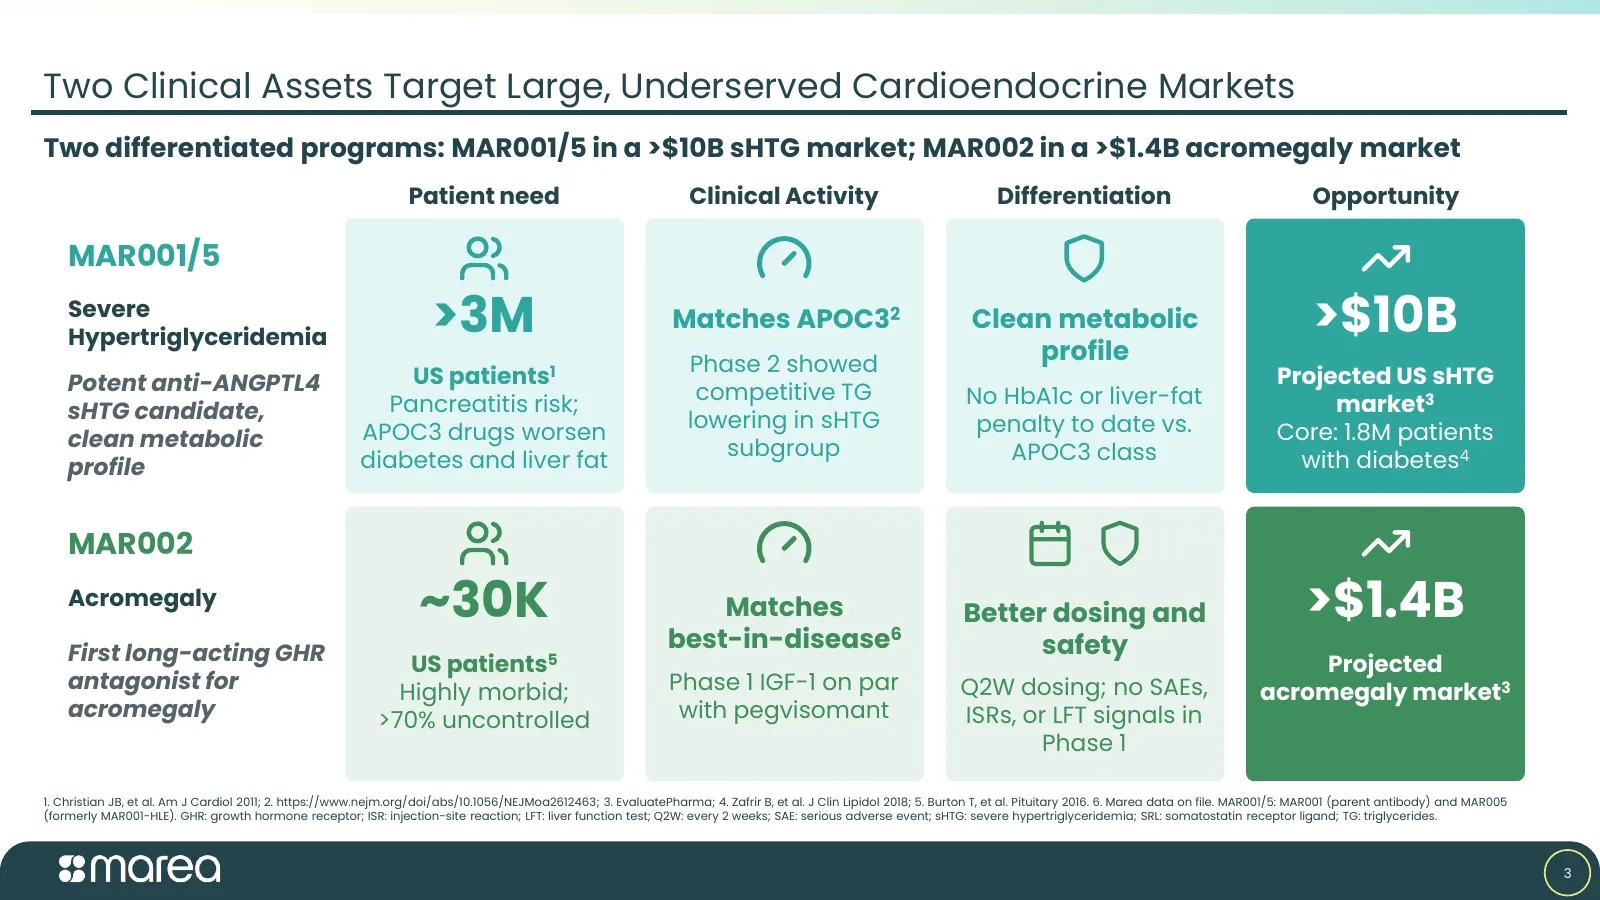
Slide 3: Two Clinical Assets Target Large, Underserved Cardioendocrine Markets
Two Clinical Assets Target Large, Underserved Cardioendocrine Markets Two differentiated programs: MAR001/5 in a >$10B sHTG market; MAR002 in a >$1.4B acromegaly market Patient need Clinical Activity Differentiation Opportunity MAR001/5 Severe Hypertriglyceridemia >3M Matches APOC32 Clean metabolic
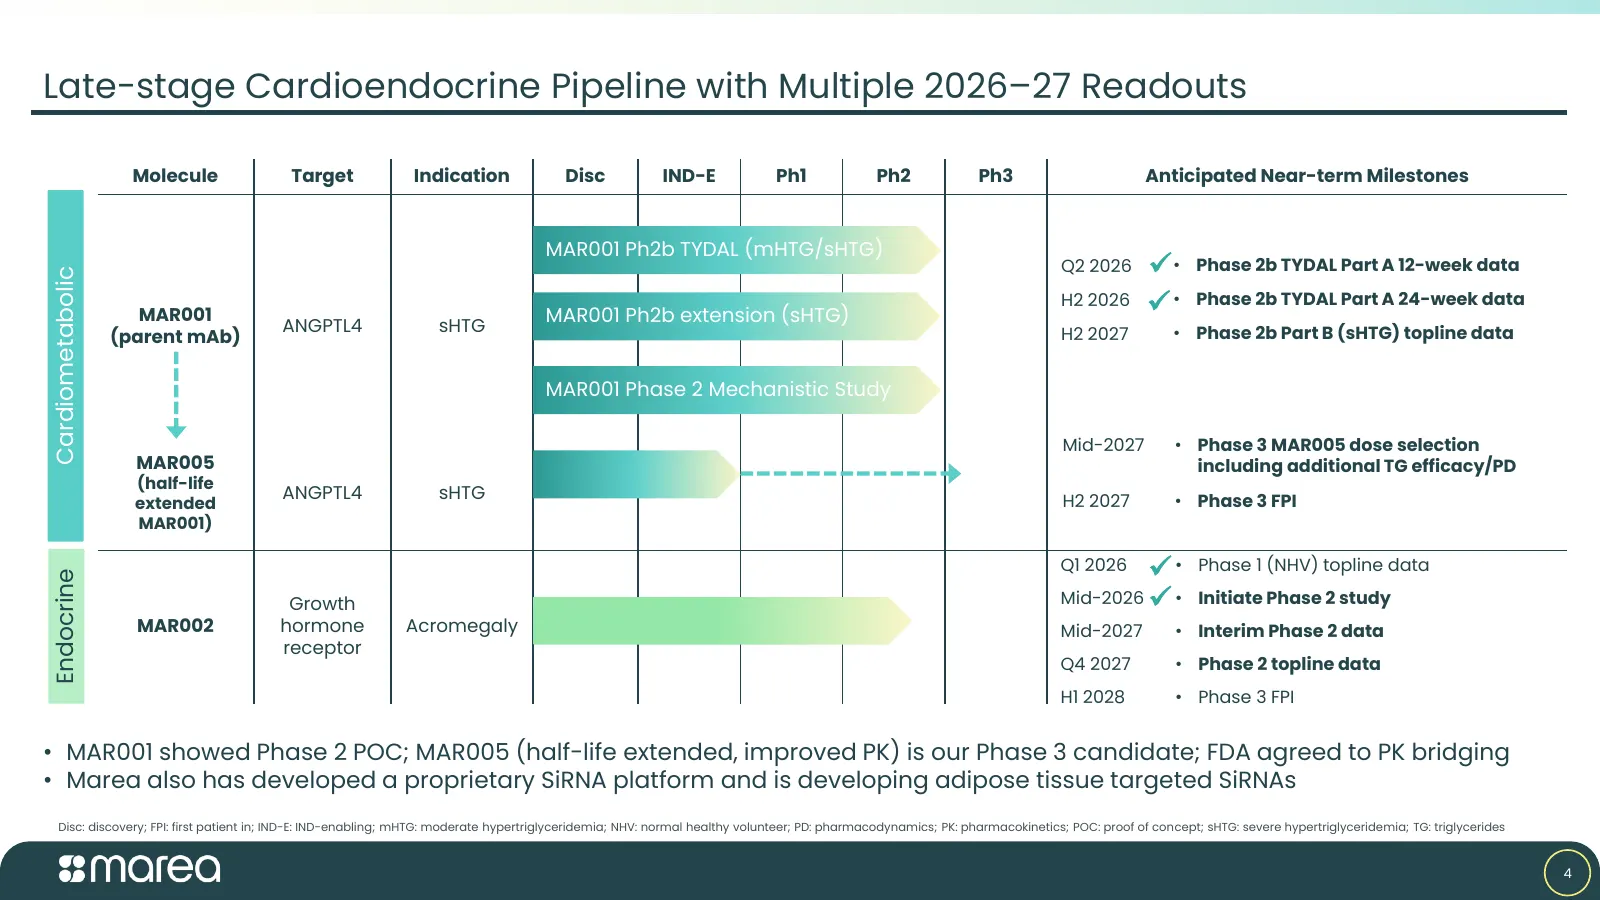
Slide 4: Late-stage Cardioendocrine Pipeline with Multiple 2026–27 Readouts
Late-stage Cardioendocrine Pipeline with Multiple 2026–27 Readouts Molecule Target Indication Disc IND-E Ph1 Ph2 Ph3 Anticipated Near-term Milestones MAR001 Ph2b TYDAL (mHTG/sHTG) Q2 2026 ✓ • Phase 2b TYDAL Part A 12-week data Cardiometabolic H2 2026 ✓ • Phase 2b TYDAL Part A 24-week data MAR001 ANG

Slide 5: MAR005 for sHTG
MAR005 for sHTG Potent sHTG candidate with a clean metabolic profile ©2023 Marea Therapeutics 5
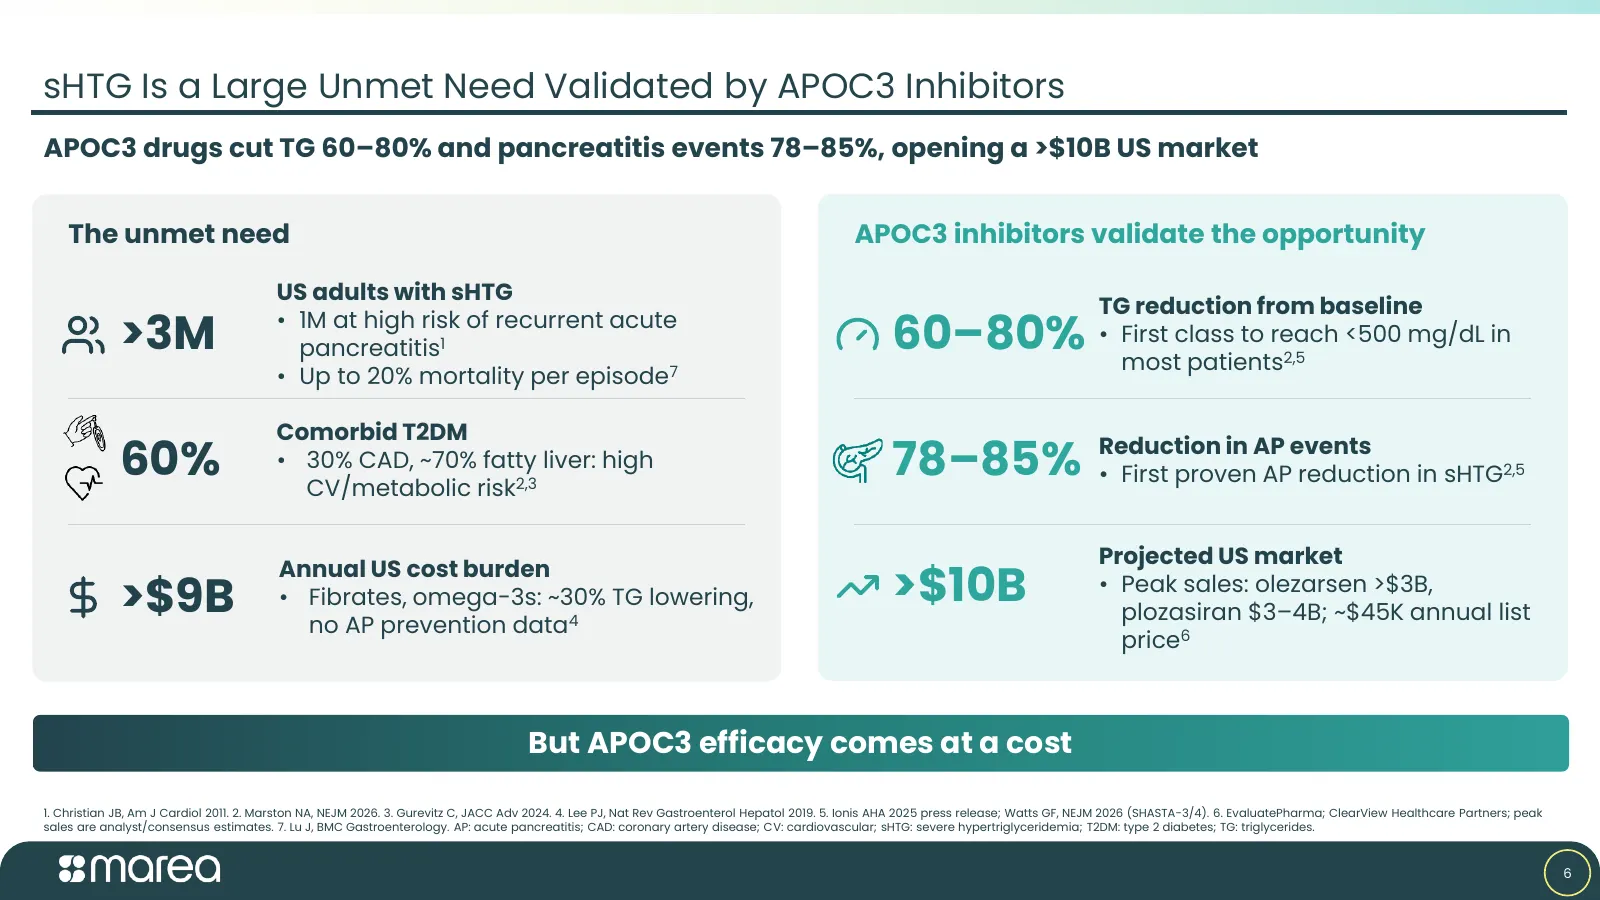
Slide 6: sHTG Is a Large Unmet Need Validated by APOC3 Inhibitors
sHTG Is a Large Unmet Need Validated by APOC3 Inhibitors APOC3 drugs cut TG 60–80% and pancreatitis events 78–85%, opening a >$10B US market The unmet need APOC3 inhibitors validate the opportunity US adults with sHTG TG reduction from baseline >3M • 1M at high risk of recurrent acute pancreatitis1
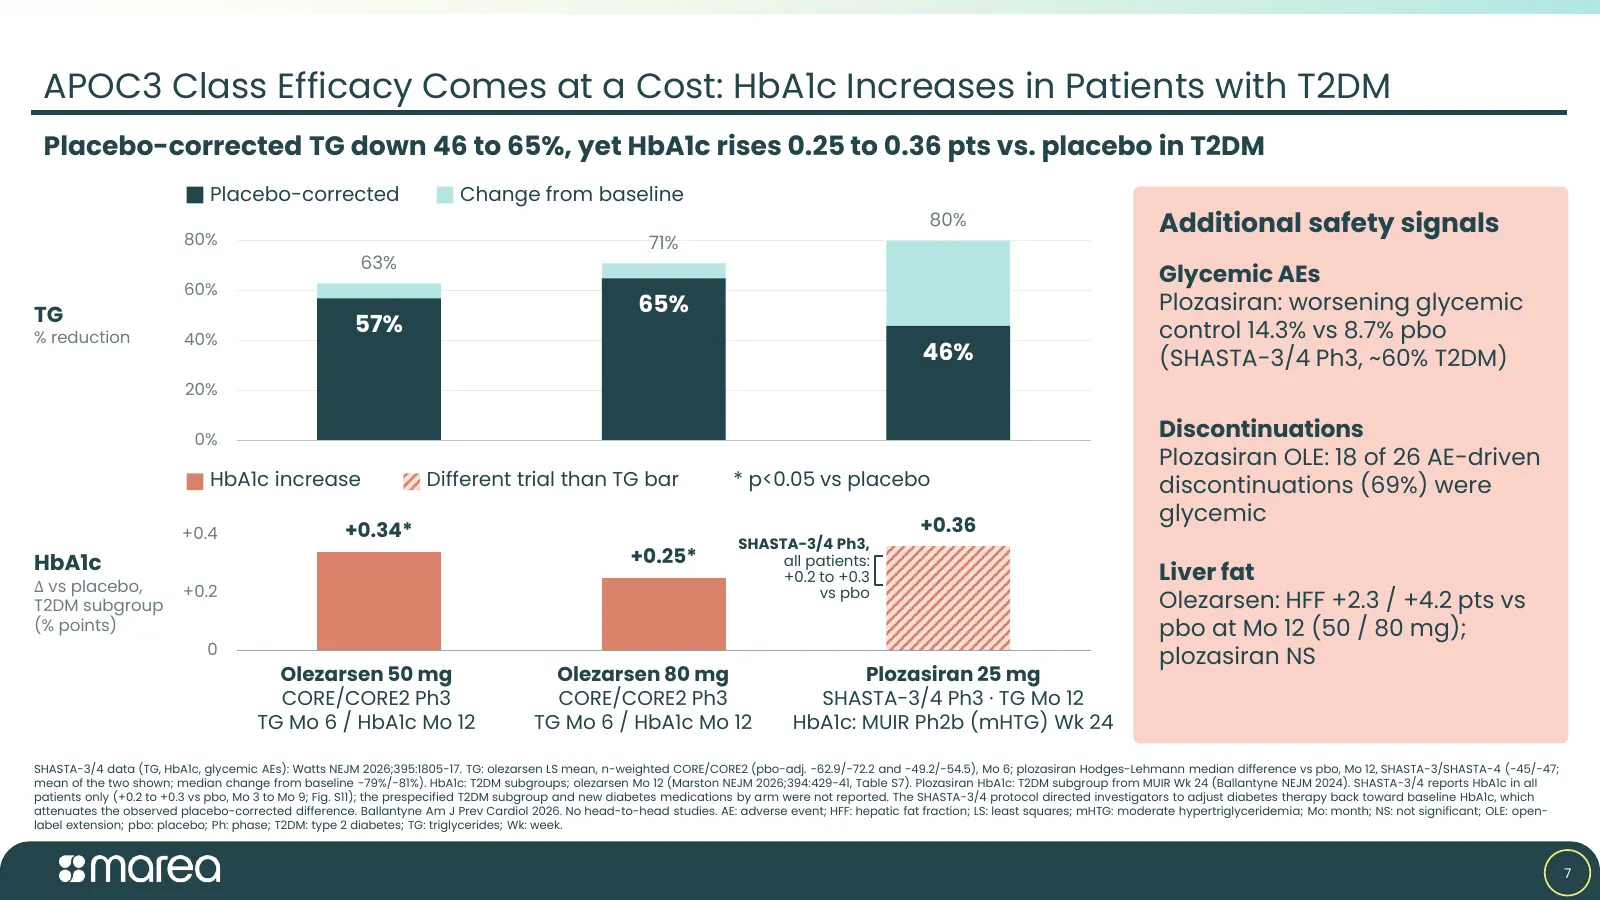
Slide 7: APOC3 Class Efficacy Comes at a Cost: HbA1c Increases in Patients with T2DM
APOC3 Class Efficacy Comes at a Cost: HbA1c Increases in Patients with T2DM Placebo-corrected TG down 46 to 65%, yet HbA1c rises 0.25 to 0.36 pts vs. placebo in T2DM Placebo-corrected Change from baseline 80% 80% Additional safety signals 71% 63% Glycemic AEs 60% TG 65% Plozasiran: worsening glycemi
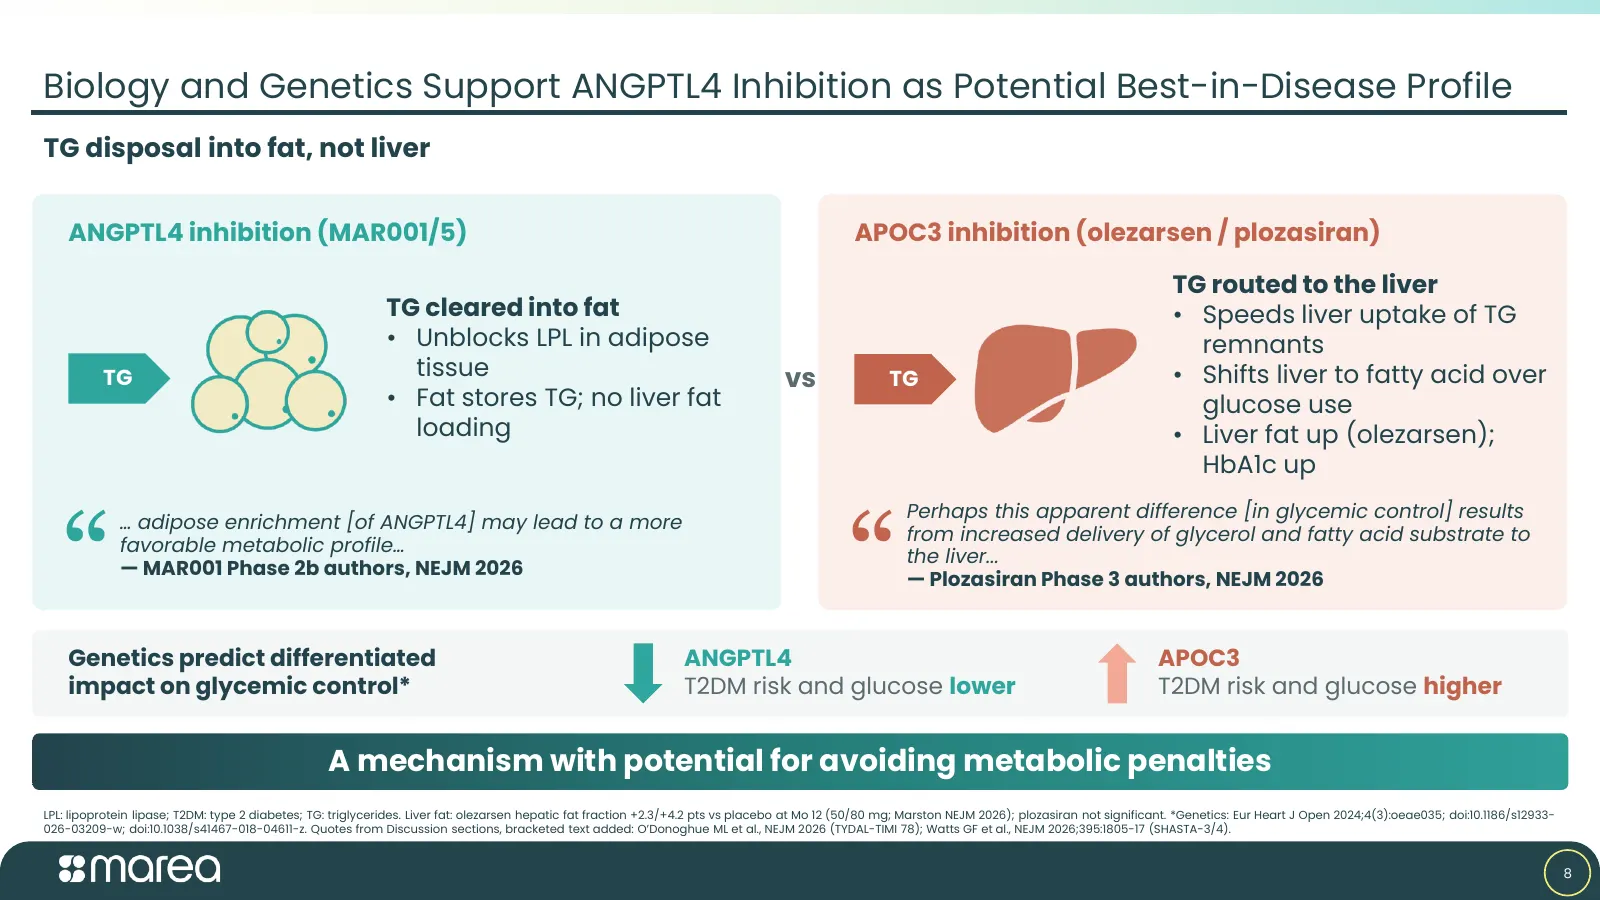
Slide 8: Biology and Genetics Support ANGPTL4 Inhibition as Potential Best-in-Disease Profile
Biology and Genetics Support ANGPTL4 Inhibition as Potential Best-in-Disease Profile TG disposal into fat, not liver ANGPTL4 inhibition (MAR001/5) APOC3 inhibition (olezarsen / plozasiran) TG routed to the liver TG cleared into fat • Speeds liver uptake of TG • Unblocks LPL in adipose remnants TG ti
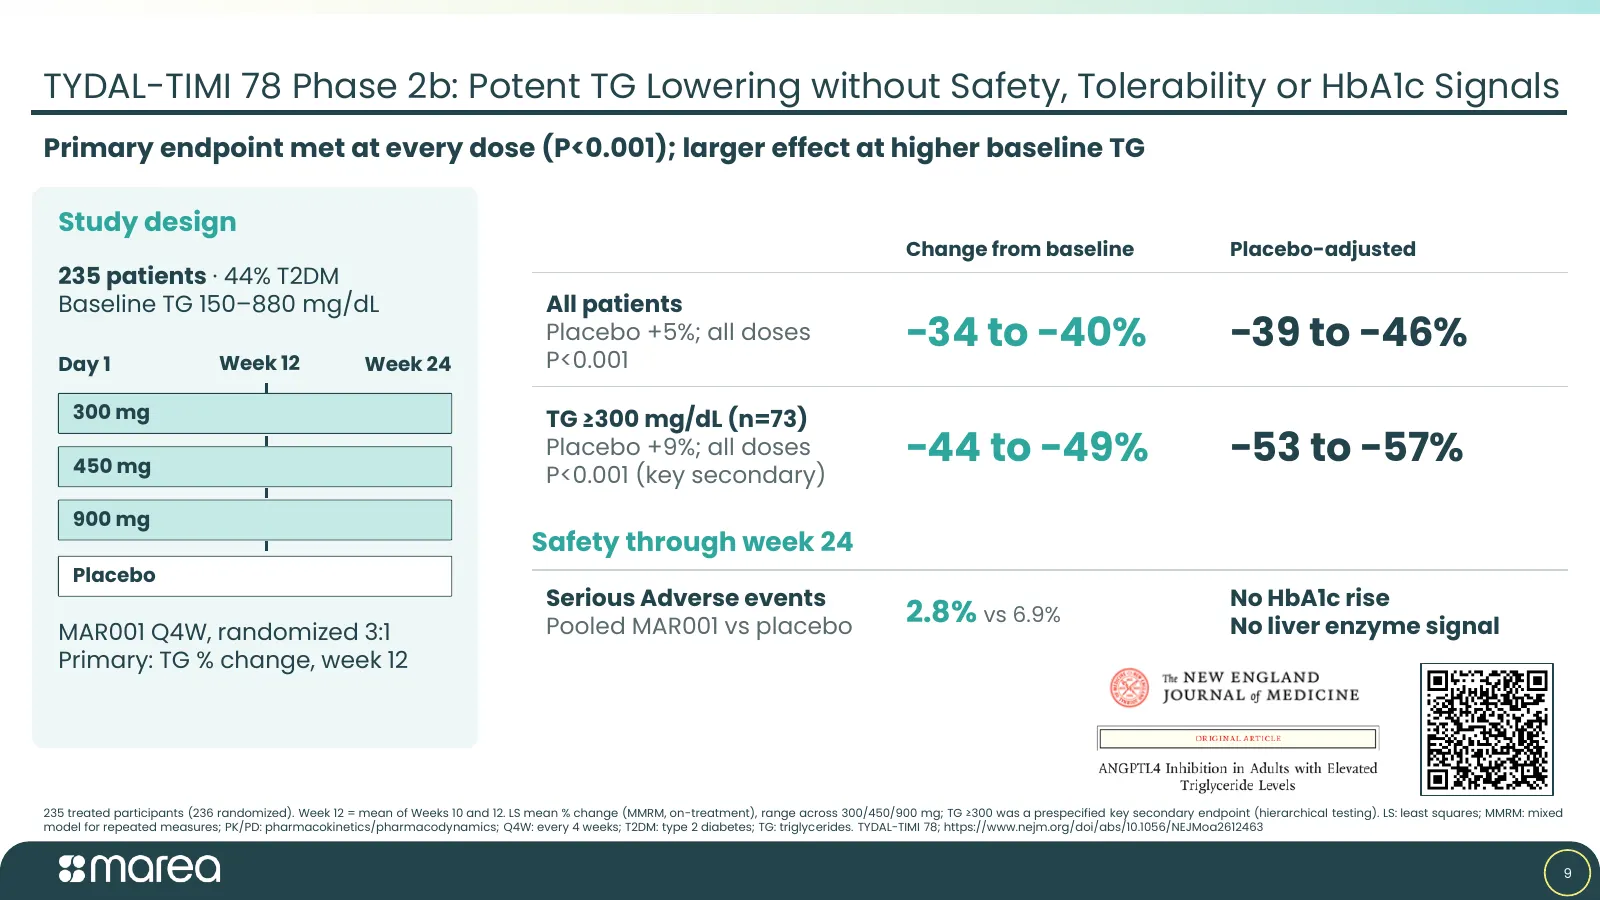
Slide 9: TYDAL-TIMI Phase 2b: Potent TG Lowering without Safety, Tolerability or HbA1c Signals
TYDAL-TIMI 78 Phase 2b: Potent TG Lowering without Safety, Tolerability or HbA1c Signals Primary endpoint met at every dose (P<0.001); larger effect at higher baseline TG Study design Change from baseline Placebo-adjusted 235 patients · 44% T2DM Baseline TG 150–880 mg/dL All patients Placebo +5%; al
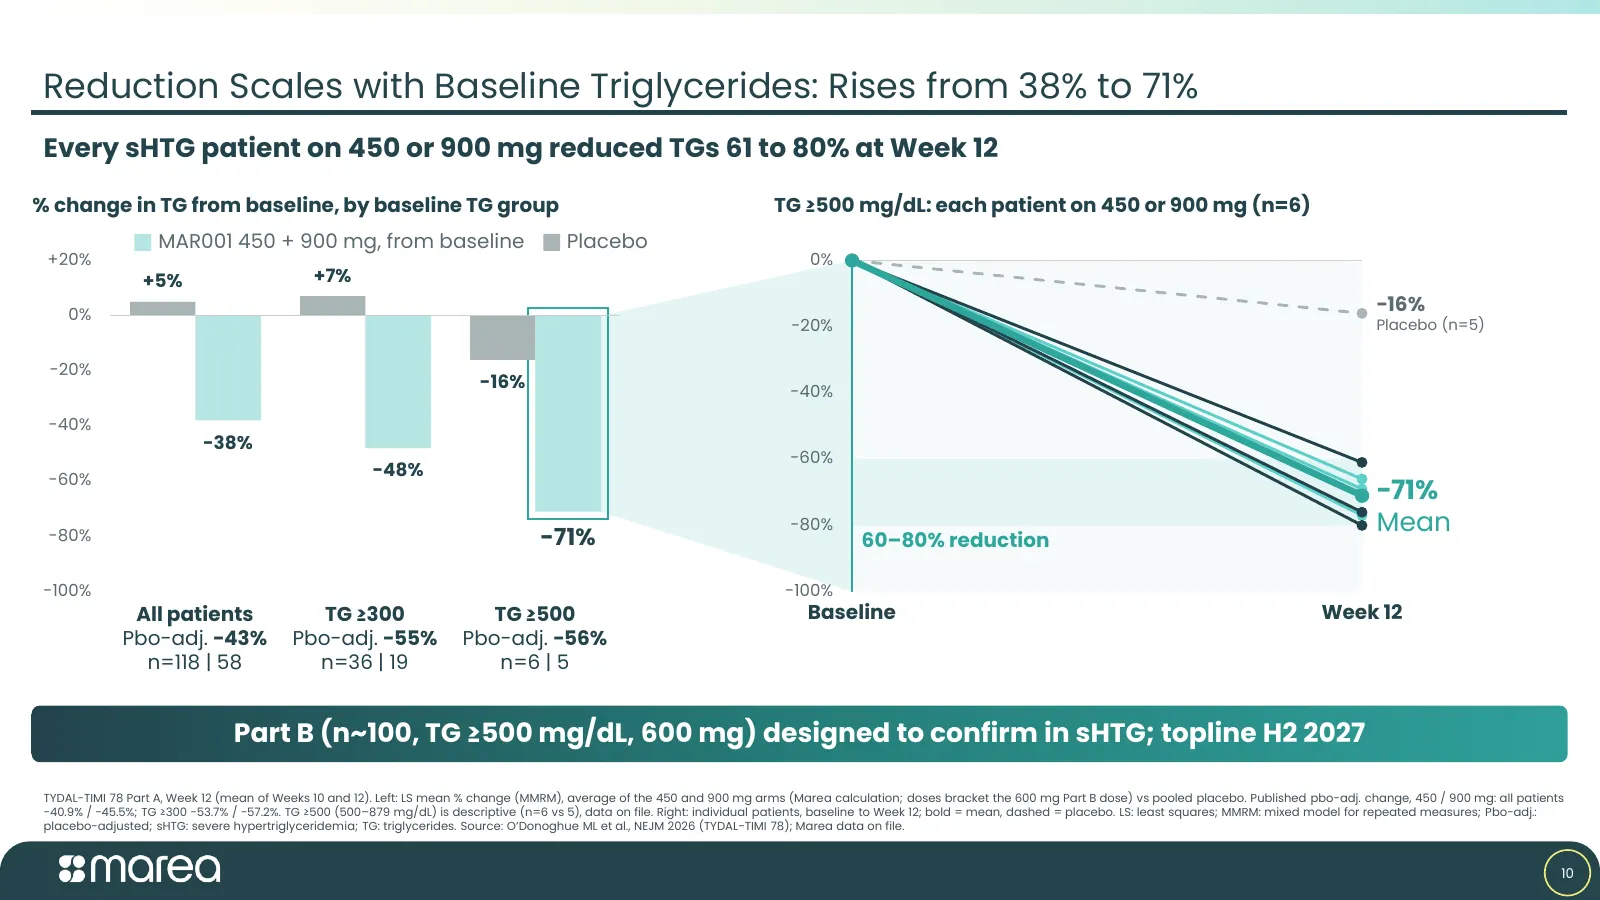
Slide 10: Reduction Scales with Baseline Triglycerides: Rises from 38% to 71%
Reduction Scales with Baseline Triglycerides: Rises from 38% to 71% Every sHTG patient on 450 or 900 mg reduced TGs 61 to 80% at Week 12 % change in TG from baseline, by baseline TG group TG ≥500 mg/dL: each patient on 450 or 900 mg (n=6) MAR001 450 + 900 mg, from baseline Placebo +20% 0% +5% +7% 0%
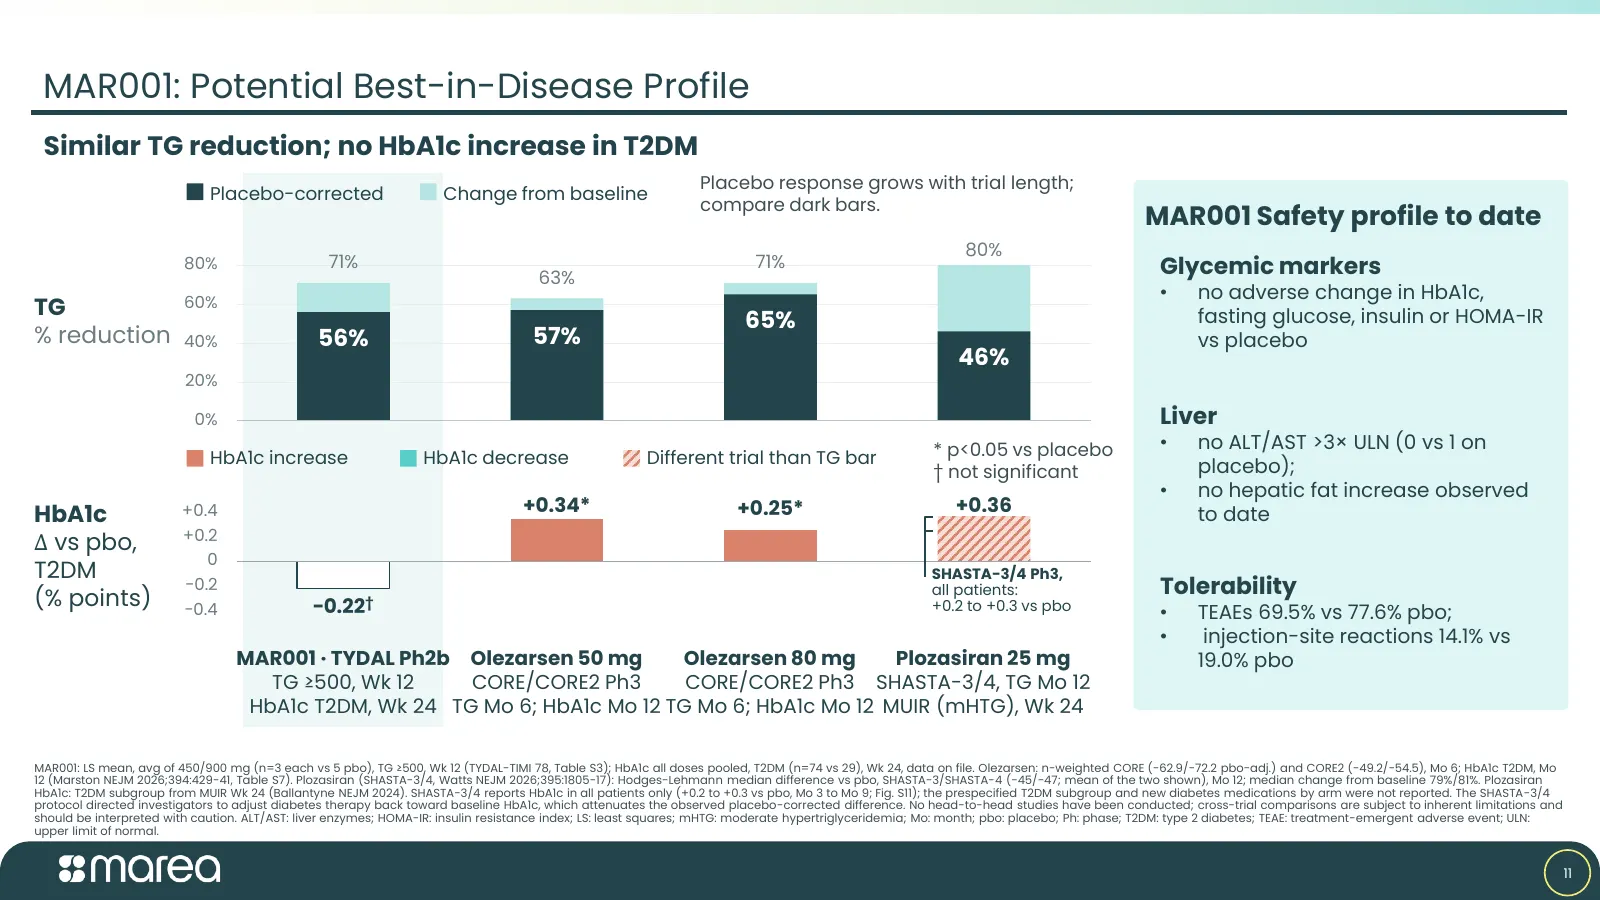
Slide 11: MAR001: Potential Best-in-Disease Profile
MAR001: Potential Best-in-Disease Profile Similar TG reduction; no HbA1c increase in T2DM Placebo response grows with trial length; Placebo-corrected Change from baseline compare dark bars. MAR001 Safety profile to date 80% 80% 71% 71% Glycemic markers 63% • no adverse change in HbA1c, TG 60% fastin
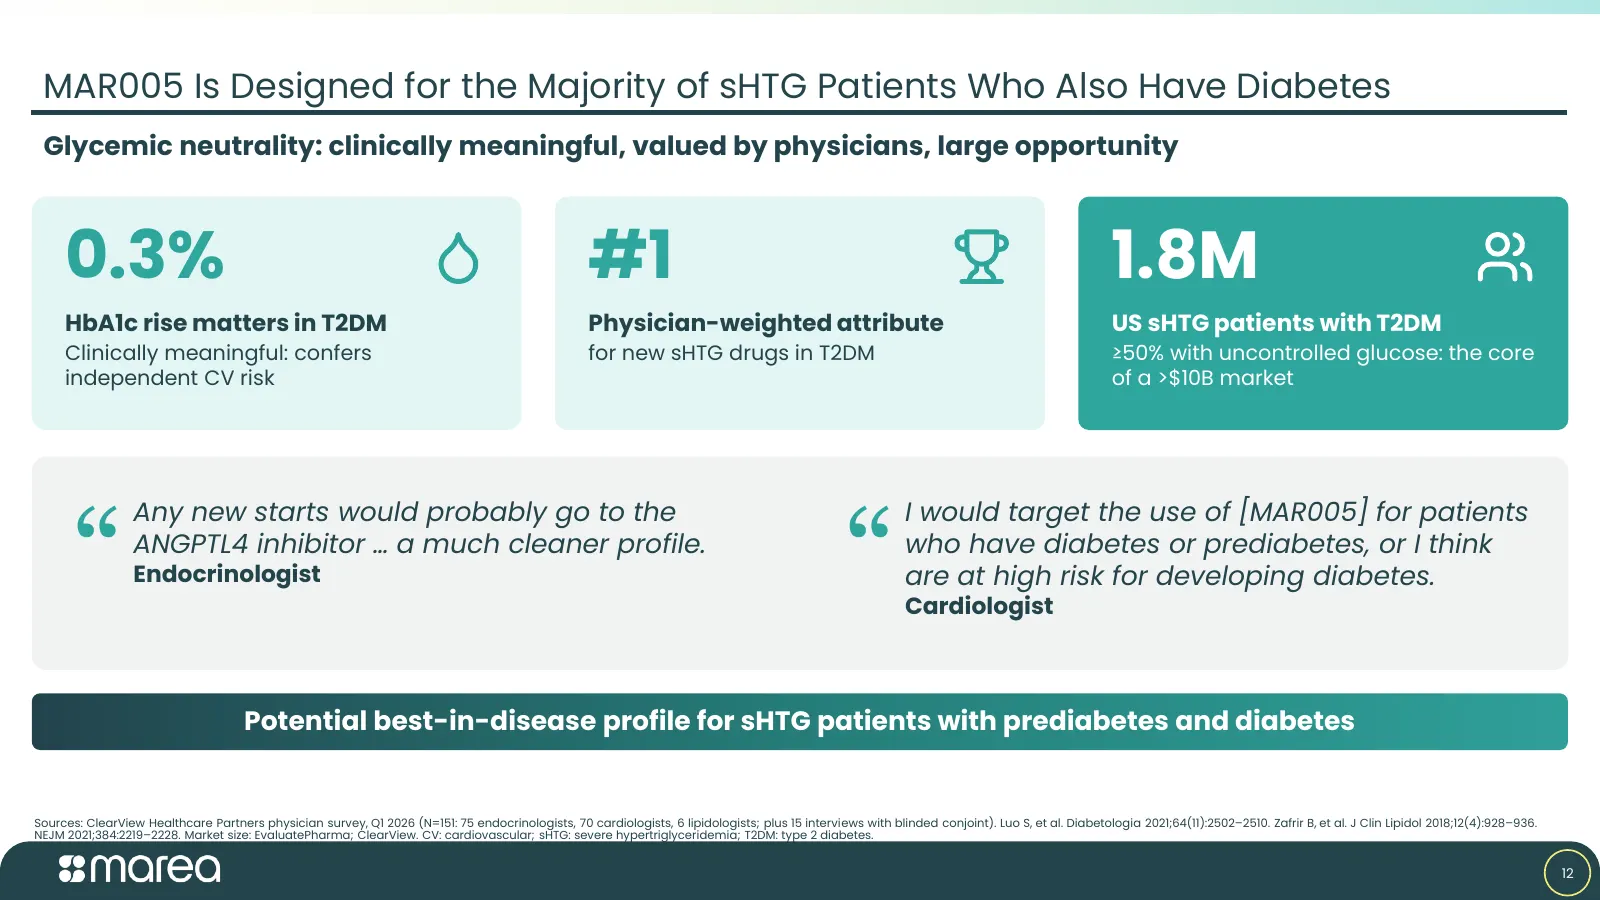
Slide 12: MAR005 Is Designed for the Majority of sHTG Patients Who Also Have Diabetes
MAR005 Is Designed for the Majority of sHTG Patients Who Also Have Diabetes Glycemic neutrality: clinically meaningful, valued by physicians, large opportunity 0.3% #1 1.8M HbA1c rise matters in T2DM Physician-weighted attribute US sHTG patients with T2DM Clinically meaningful: confers for new sHTG
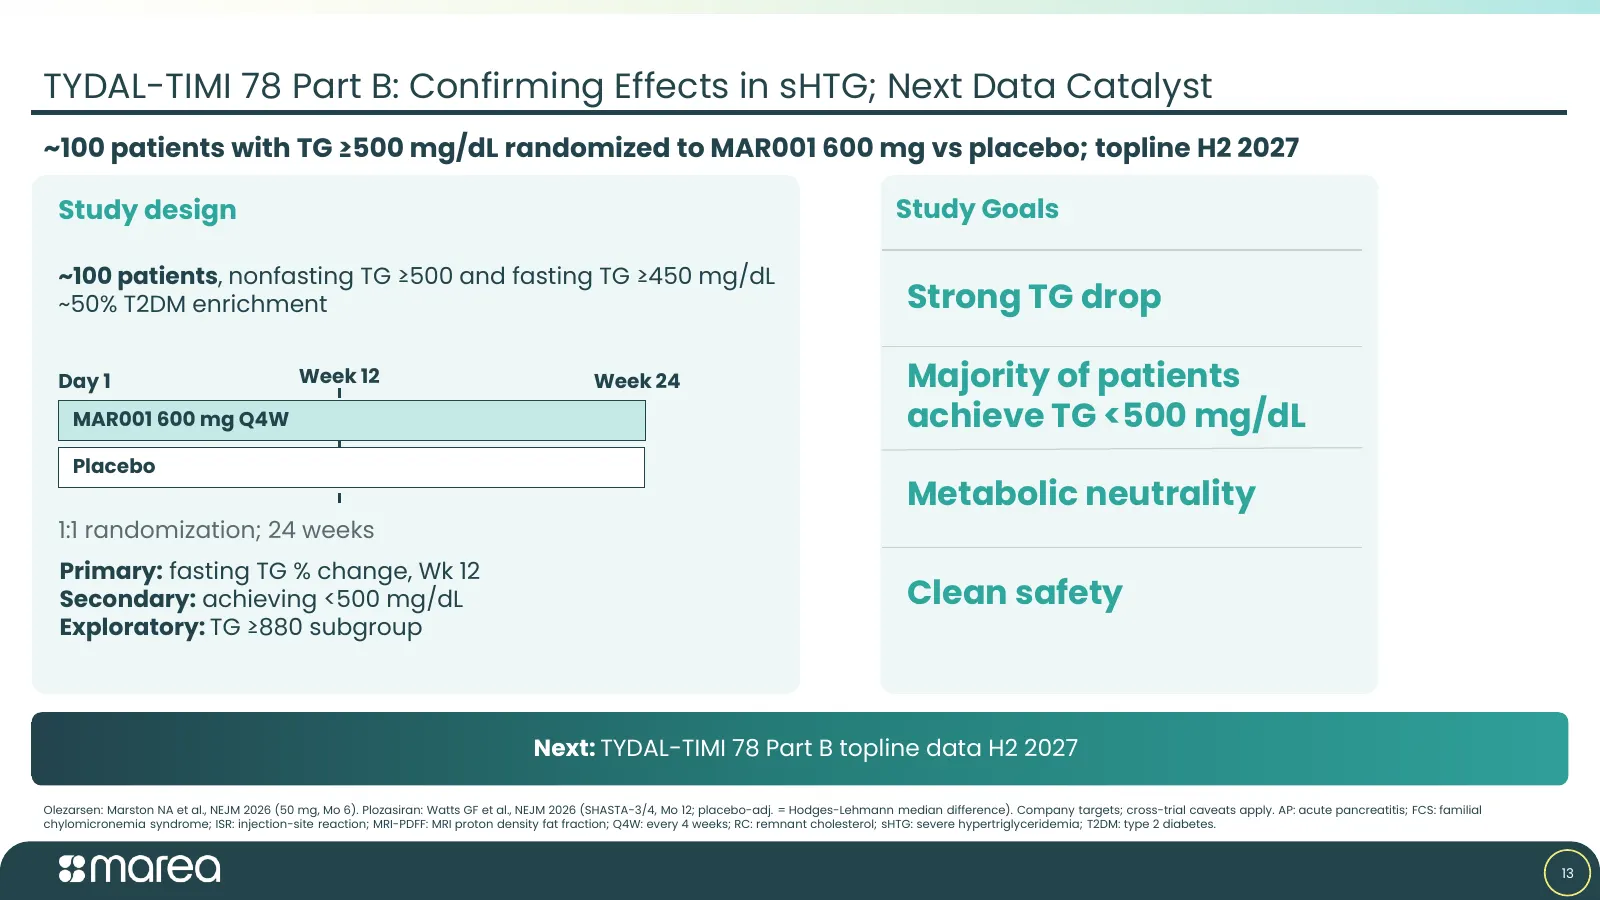
Slide 13: TYDAL-TIMI Part B: Confirming Effects in sHTG; Next Data Catalyst
TYDAL-TIMI 78 Part B: Confirming Effects in sHTG; Next Data Catalyst ~100 patients with TG ≥500 mg/dL randomized to MAR001 600 mg vs placebo; topline H2 2027 Study design Study Goals ~100 patients, nonfasting TG ≥500 and fasting TG ≥450 mg/dL ~50% T2DM enrichment Strong TG drop Day 1 Week 12 Week 24

Slide 14: MAR002 for Acromegaly
MAR002 for Acromegaly First long-acting GHR antagonist candidate for acromegaly ©2023 Marea Therapeutics 14
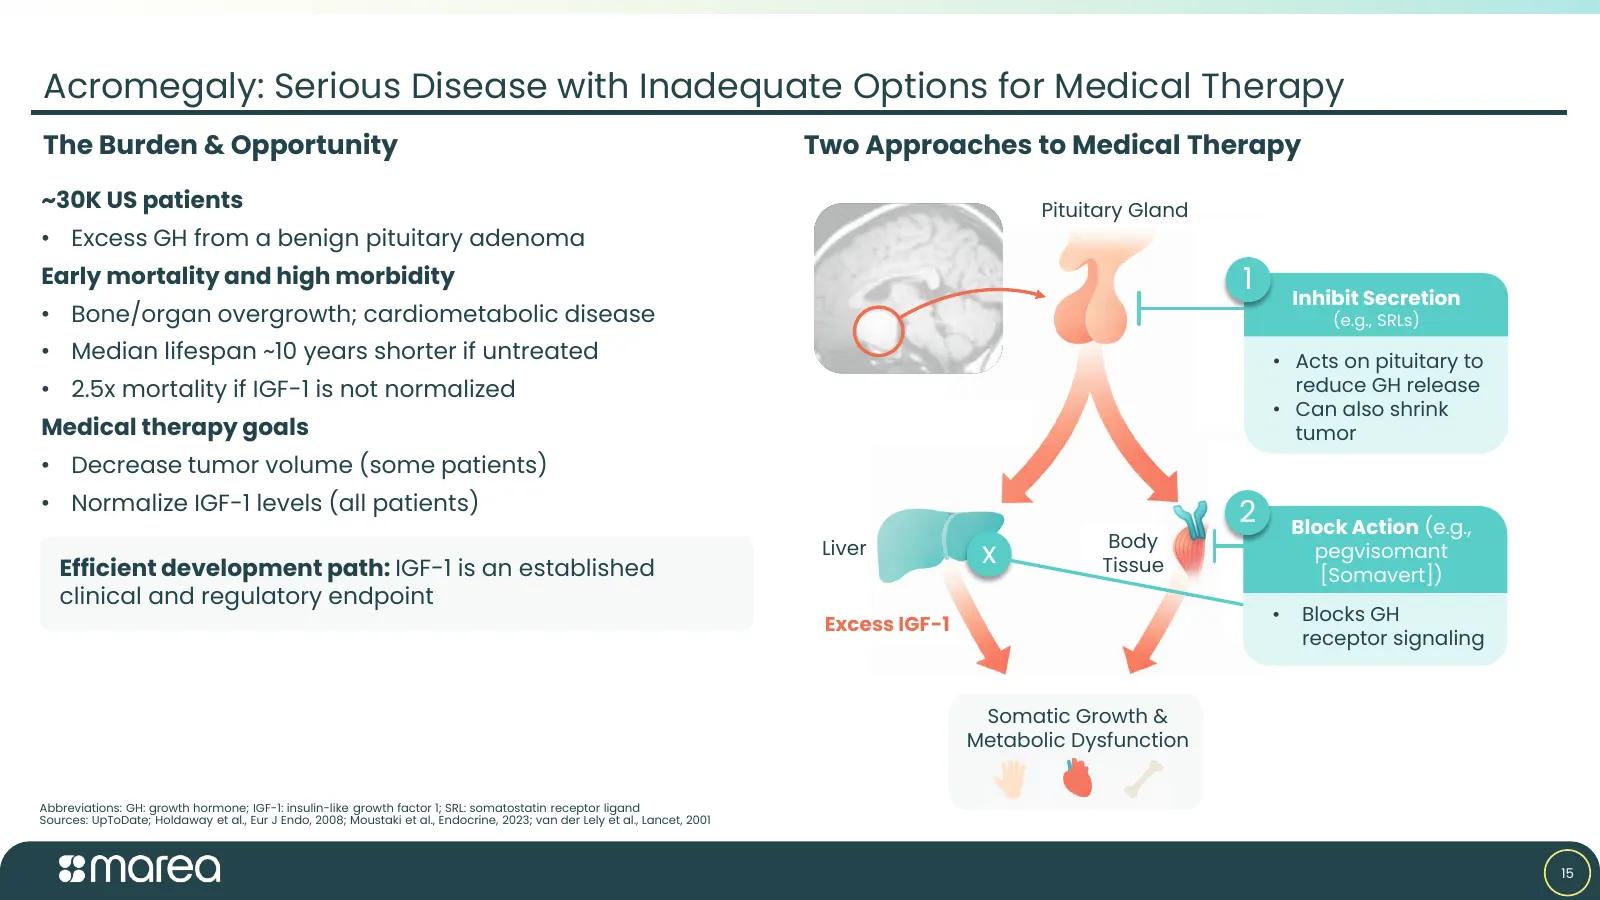
Slide 15: Acromegaly: Serious Disease with Inadequate Options for Medical Therapy
Acromegaly: Serious Disease with Inadequate Options for Medical Therapy The Burden & Opportunity Two Approaches to Medical Therapy ~30K US patients Pituitary Gland • Excess GH from a benign pituitary adenoma Early mortality and high morbidity 1 Inhibit Secretion • Bone/organ overgrowth; cardiometabo
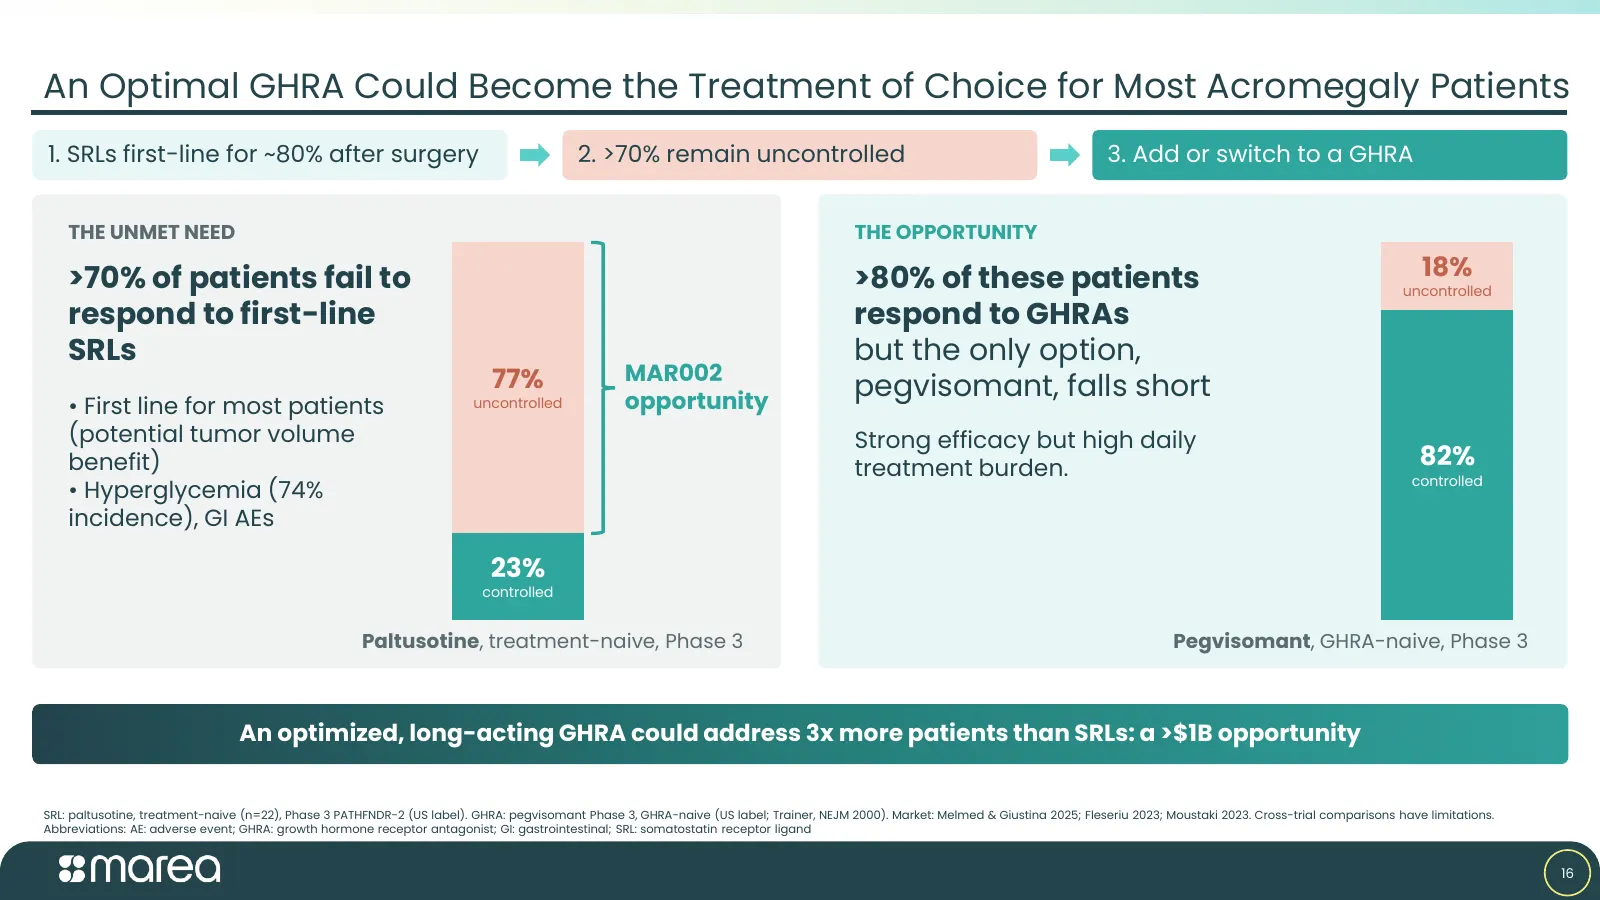
Slide 16: An Optimal GHRA Could Become the Treatment of Choice for Most Acromegaly Patients
An Optimal GHRA Could Become the Treatment of Choice for Most Acromegaly Patients 1. SRLs first-line for ~80% after surgery 2. >70% remain uncontrolled 3. Add or switch to a GHRA THE UNMET NEED THE OPPORTUNITY >70% of patients fail to >80% of these patients 18% uncontrolled respond to first-line res
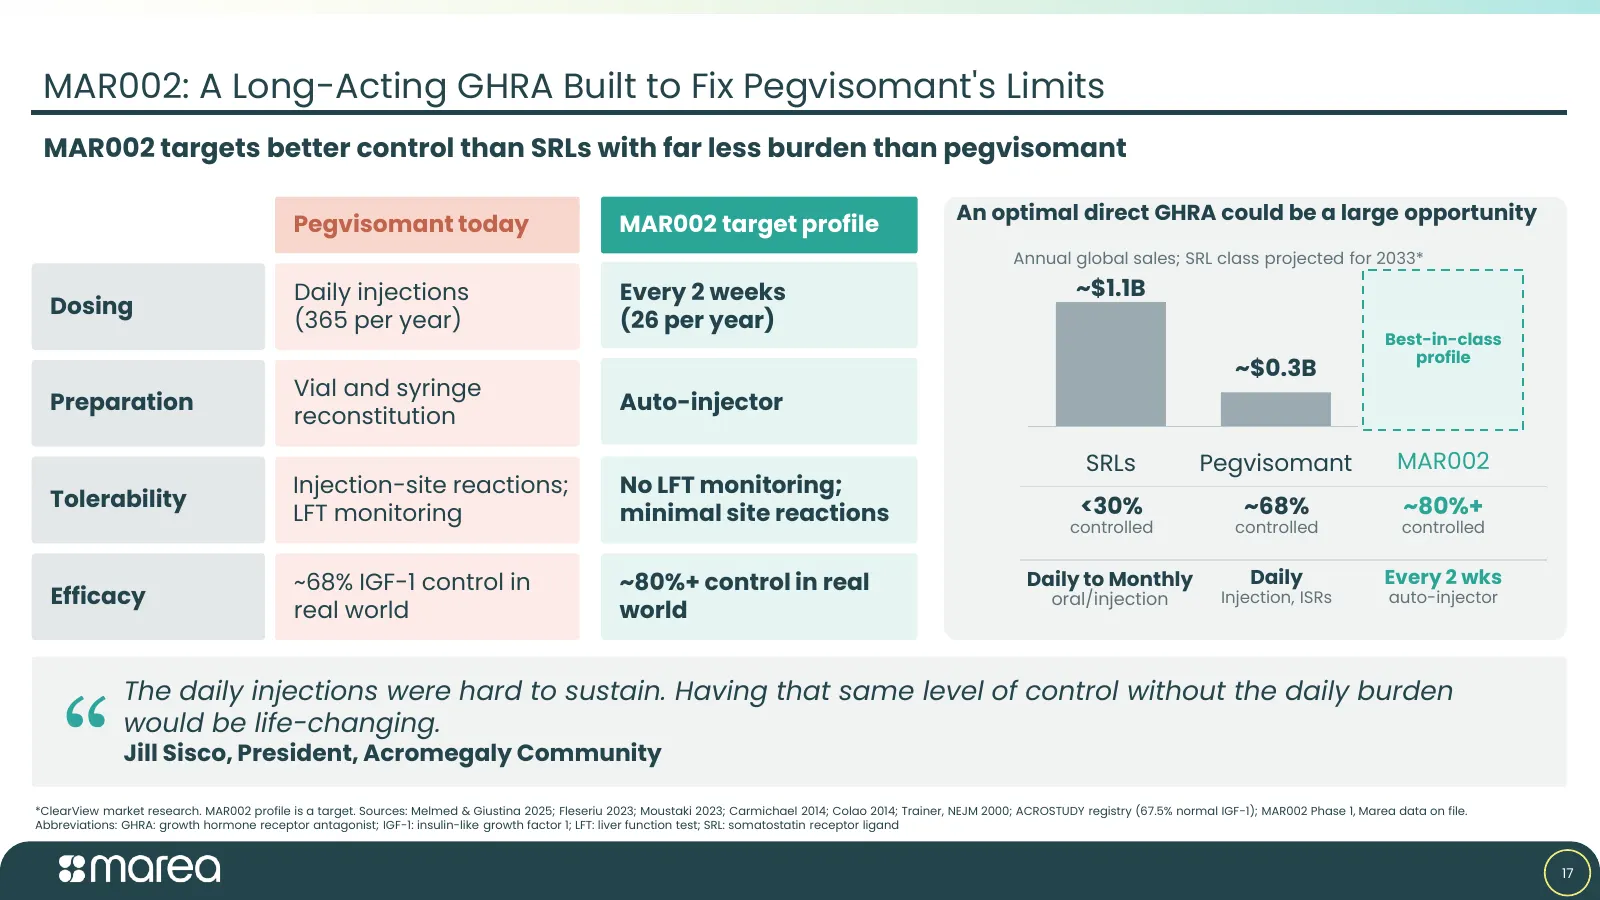
Slide 17: MAR002: A Long-Acting GHRA Built to Fix Pegvisomant's Limits
MAR002: A Long-Acting GHRA Built to Fix Pegvisomant's Limits MAR002 targets better control than SRLs with far less burden than pegvisomant An optimal direct GHRA could be a large opportunity Pegvisomant today MAR002 target profile Annual global sales; SRL class projected for 2033* Daily injections E
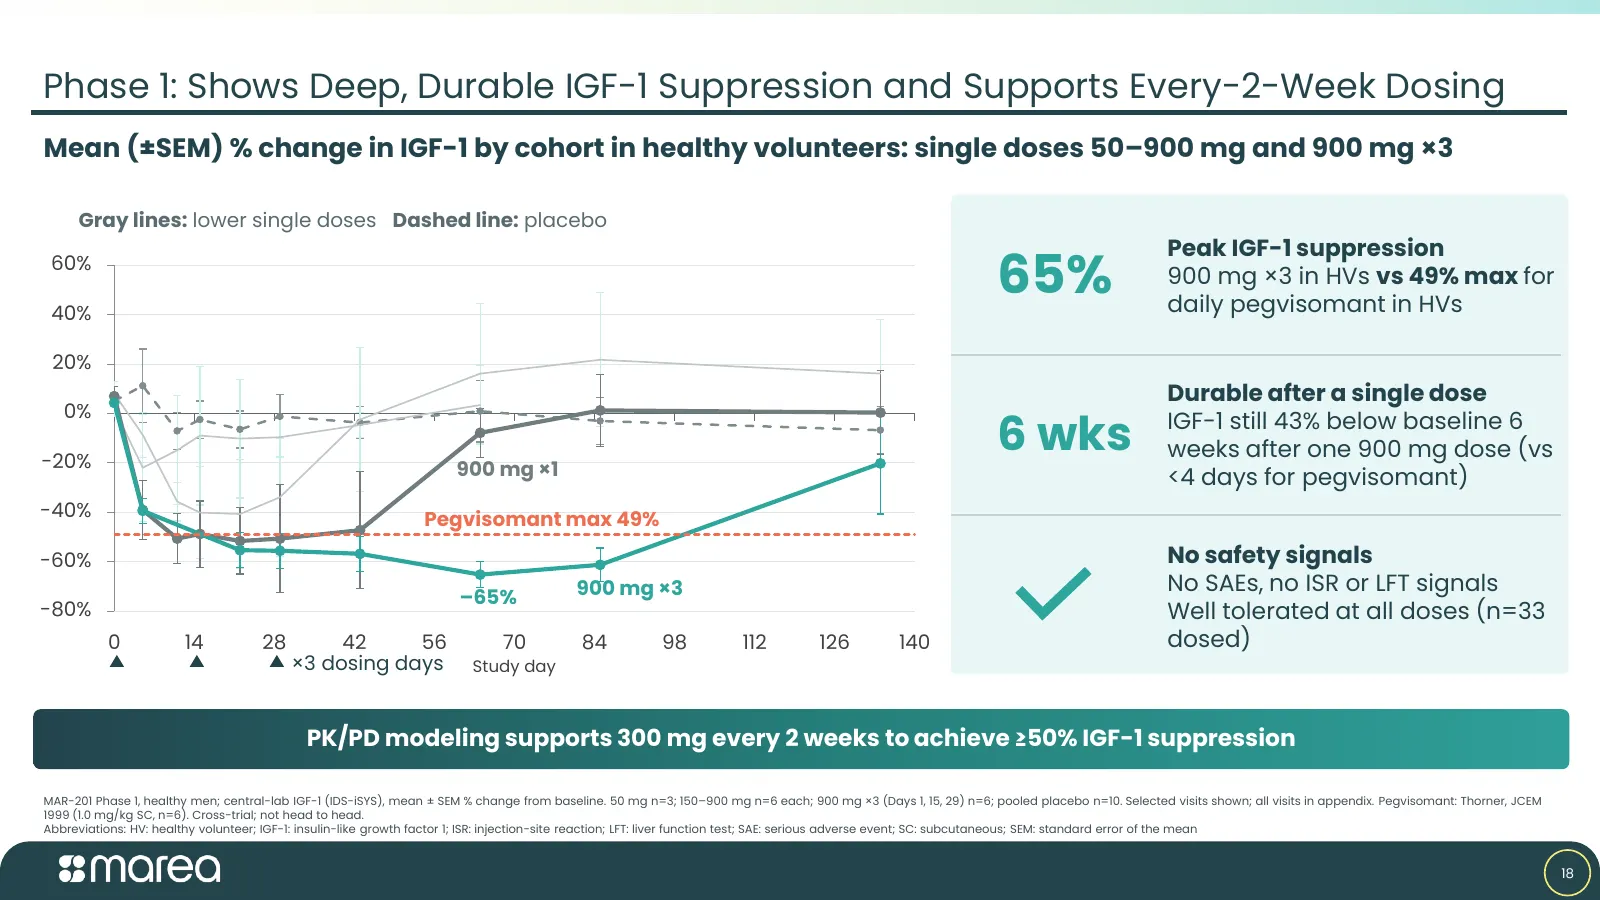
Slide 18: Phase 1: Shows Deep, Durable IGF-1 Suppression and Supports Every-2-Week Dosing
Phase 1: Shows Deep, Durable IGF-1 Suppression and Supports Every-2-Week Dosing Mean (±SEM) % change in IGF-1 by cohort in healthy volunteers: single doses 50–900 mg and 900 mg ×3 Gray lines: lower single doses Dashed line: placebo Peak IGF-1 suppression 60% 40% 65% 900 mg ×3 in HVs vs 49% max for d
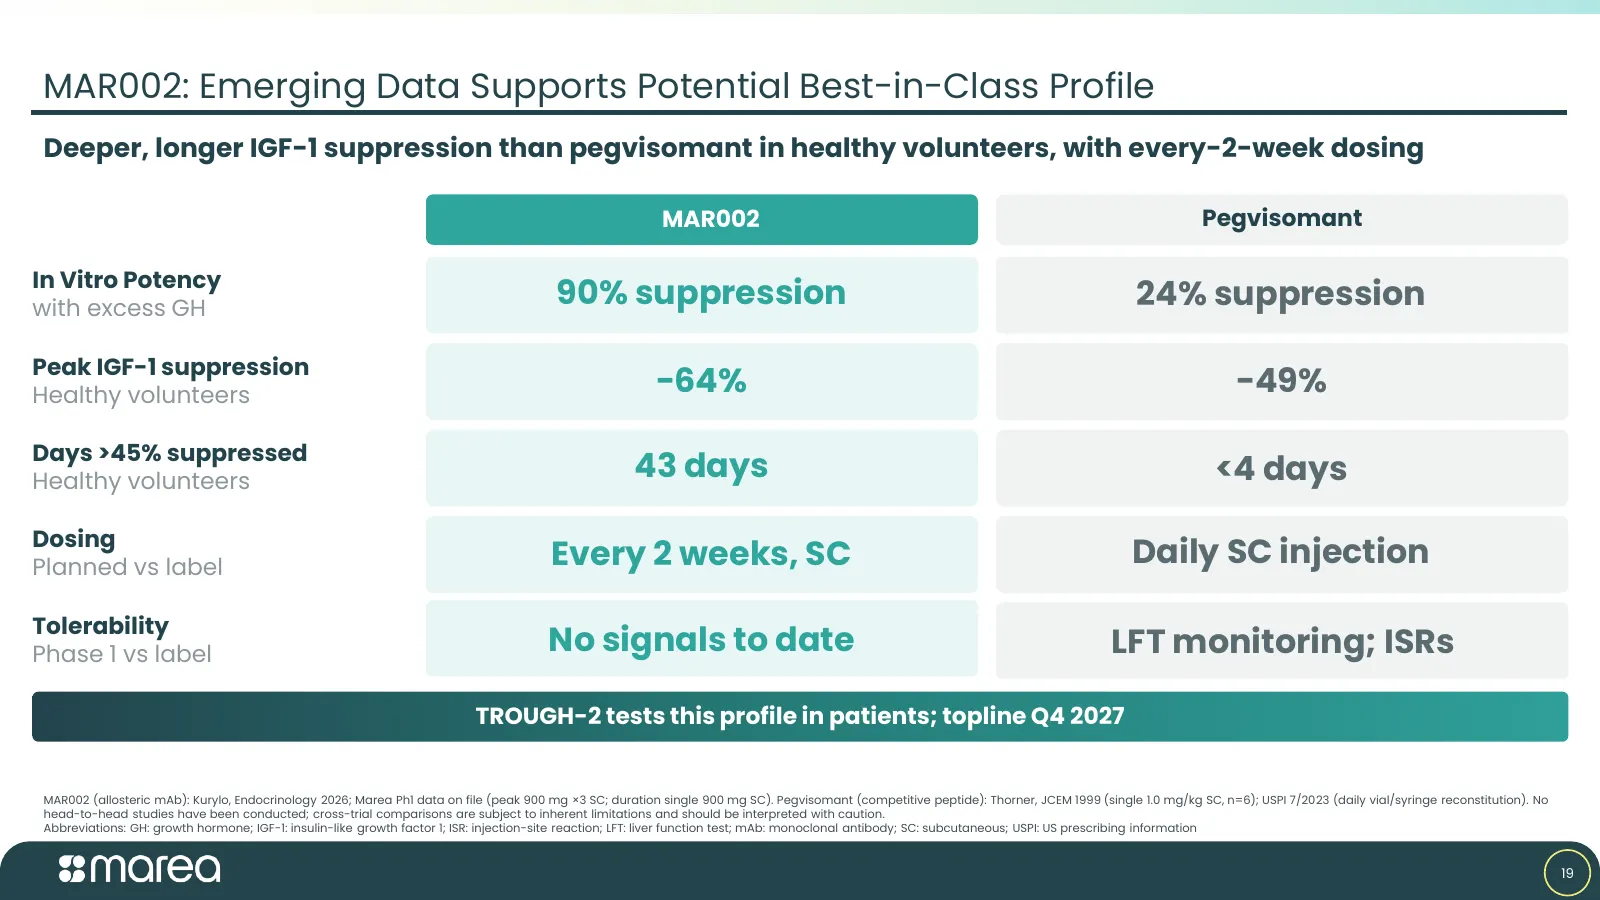
Slide 19: MAR002: Emerging Data Supports Potential Best-in-Class Profile
MAR002: Emerging Data Supports Potential Best-in-Class Profile Deeper, longer IGF-1 suppression than pegvisomant in healthy volunteers, with every-2-week dosing MAR002 Pegvisomant In Vitro Potency with excess GH 90% suppression 24% suppression Peak IGF-1 suppression Healthy volunteers −64% −49% Days

Slide 20: TROUGH-2 Phase 2 Will Set the Phase 3 Dose Across First- and Second-Line Patients
TROUGH-2 Phase 2 Will Set the Phase 3 Dose Across First- and Second-Line Patients Randomized, double-blind, placebo-controlled; every-2-week dosing; first patient dosed Sep 30, 2026 Study design Study Goals ~72 patients, active acromegaly IGF-1 ≥1.3× ULN Beat SRL IGF-1 reduction Day 1 Week 10 150 mg
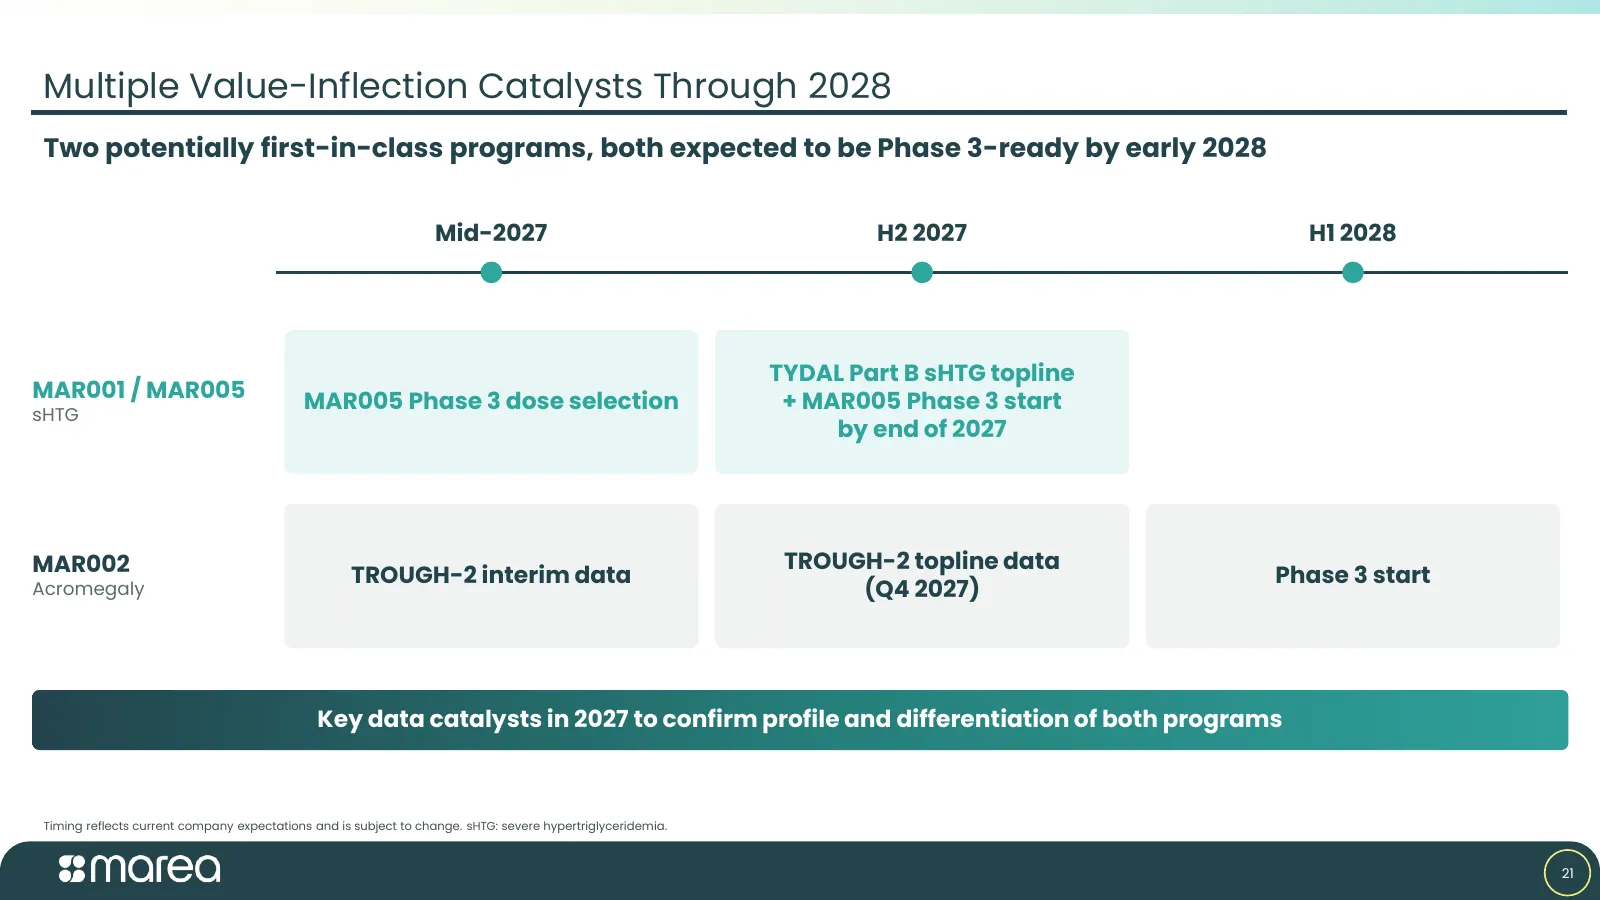
Slide 21: Multiple Value-Inflection Catalysts Through 2028
Multiple Value-Inflection Catalysts Through 2028 Two potentially first-in-class programs, both expected to be Phase 3-ready by early 2028 Mid-2027 H2 2027 H1 2028 TYDAL Part B sHTG topline MAR001 / MAR005 MAR005 Phase 3 dose selection + MAR005 Phase 3 start sHTG by end of 2027 MAR002 TROUGH-2 toplin

Slide 22: Thank You
Thank You ©2026 Marea Therapeutics, Inc. All rights reserved.
Source: company website
More decks from Lisata Therapeutics, Inc.
 Merger or Acquisition (September 2026)28 slides · Sep 17, 2026
 Marea Therapeutics — Investor Presentation (September 2026)25 slides · September 2026
 Investor Presentation (November 2025)78 slides · Nov 6, 2025
 Investor Presentation (October 2025)70 slides · Oct 14, 2025
 Q2 2025 Earnings Presentation71 slides · Aug 7, 2025
 Investor Presentation (June 2025)70 slides · Jun 26, 2025