Biomimetic Therapeutics — Investor Day (February 2011)
113 slides from Biomimetic Therapeutics's investor day presentation, Feb 23, 2011

Slide 1: 4th Annual BioMimetic Therapeutics Analyst & Investor Meeting
4th Annual BioMimetic Therapeutics Analyst & Investor Meeting February 17, 2011 www.biomimetics .com

Slide 2: Forward Looking Statements
Forward Looking Statements This presentation contains "forward -looking statements" within the meaning of the Private Securities Litigation Reform Act of 1995. These forward -looking statements are based on the current intent and expectations of the management of BioMimetic . These statements are no

Slide 3: Agenda
Introduction FDA Panel Meeting Preview Commercialization & Reimbursement Overview Other Milestone Updates Q&A Reception Agendag

Slide 4: FDA Panel Meeting Preview
FDA Panel Meeting Preview www.biomimetics .com

Slide 5: PMA Milestones
PMA Milestones Development of Product Concept through Successful Clinical Trial Submission of PMA PMA Filed 100-Day Meeting with FDA Deficiency Response Panel Meeting – May 12 Approval – Q3 Post-Approval Requirements
Slide 6: What is a Panel?
What is a Panel? A meeting called by the FDA to provide guidance to the Agency on high-profile products Devices has over 30 standing panels BMTI will go to the Orthopedic and Restorative Devices Panel

Slide 7: Who's on it?
Who’s on it? Special Government Employees (SGEs) ’ Standing Panel Members Include Orthopedic Surgeons , Statisticians , Industry and Consumer Representatives Many sat on OP-1 and Amplify Panels Consultants to the Panel Foot and Ankle Surgeons Oncologists (because of Amplify) Immunologists (because o

Slide 8: BMTI Tasks
BMTI Tasks Identify internal and external resources for presentations and Q & A Prepare presentation Anticipate questions from FDA and Panel Do Mock Panels Prepare Panel Packages Quickly respond to all FDA requests

Slide 9: Sheldon S. Lin, M.D.
Sheldon S. Lin, M.D. Dr. Lin completed his undergraduate studies at Pennsylvania State University and received his medical doctorate from Jefferson Medical College of Philadelphia . He completed his residency training in Orthopaedic Surgery at Thomas Jefferson University Hospital with further traini

Slide 10: Judy Baumhauer, M.D.
Judy Baumhauer, M.D. Dr. Baumhauer sees patients of all ages and lifestyles . Her treatment goals are to decrease pain and improve function through surgical and non-surgical options for her patients. Her clinical practice includes arthritis, painful flatfoot, foot reconstruction, diabetic foot and a

Slide 11: Preclinical Efficacy Studies
Preclinical Efficacy Studies Sheldon S. Lin, M.D. Associate Professor University of Medicine & Dentistry of New Jersey www.biomimetics .com
Slide 12: Preclinical Efficacy Studies
Preclinical Efficacy Studies I. Accelerated fracture healing in geriatric -osteoporotic rats using rhPDGF -BB J Orthop Res, 2008 II. rhPDGF -BB speeds fracture healing in diabetic rats J Orthop Res, 2009 III. rhPDGF -BB augmentation of bone formation in a rat model of distraction osteogenesis J Bone
Slide 13: I. rhPDGF-BB Speeds Fracture Healing
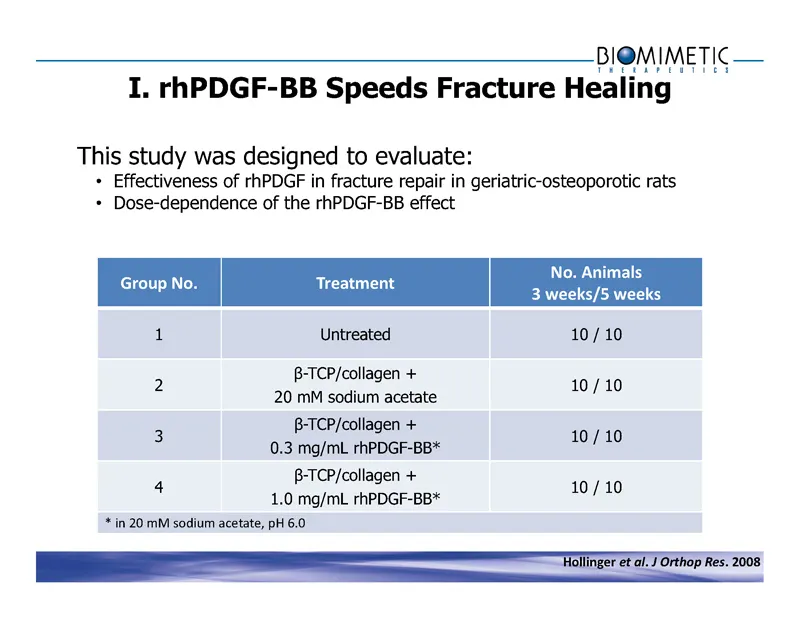
I. rhPDGF -BB Speeds Fracture Healing This study was designed to evaluate: No.3Animals Group3No . Treatment 33weeks/53weeks 1 Untreated 10 / 10 3-TCP/collagen + 2 10 / 10 20 mM sodium acetate 3-TCP/collagen + 3 10 / 10 0.3 mg/mL rhPDGF -BB* 3-TCP/collagen + 4 10 / 10 1.0 mg/mL rhPDGF -BB* *3in3203mM
Slide 14: rhPDGF-BB Accelerates Fracture Healing in Geriatric Osteoporotic Rats
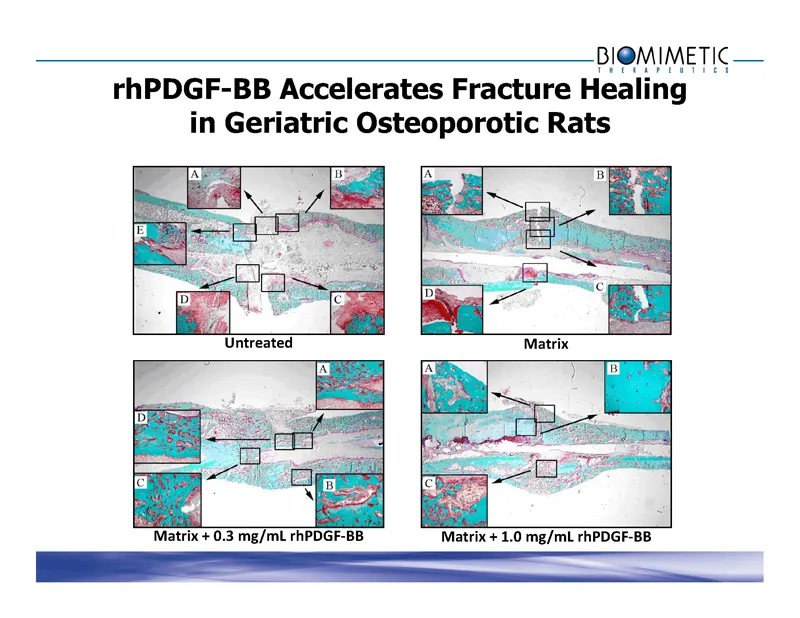
rhPDGF -BB Accelerates Fracture Healing in Geriatric Osteoporotic Rats Untreated Matrix Matrix3+30 .33mg/mL3rhPDGF3BB Matrix3+31 .03mg/mL3rhPDGF3BB
Slide 15: Mechanical Strength of Augment-treated Limbs Similar to Contralateral Limbs
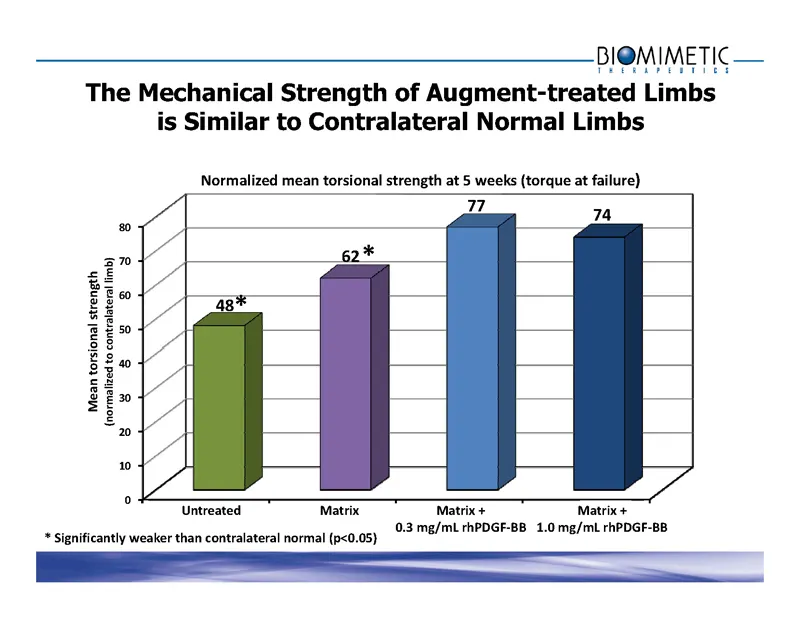
The Mechanical Strength of Augment -treated Limbs is Similar to Contralateral Normal Limbs Normalized3mean3torsional3strength3at353weeks3(torque3at3failure ) 77 74 80 70 62* b) 60 48* nal3strength3 ontralateral3lim 50 40 Mean3torsio (normalized3to3c 30 20 10 0 Untreated Matrix Matrix3+ Matrix3+ 0.33
Slide 16: Conclusions
Conclusions Augment ™ Accelerates Fracture Healing in Geriatric -Osteoporotic Rats Matrix plus rhPDGF -BB accelerated fracture healing At five weeks, the mechanical strength of Augment -treated tibias was not different from normal No evidence of either abnormal or ectopic bone formation
Slide 17: II. rhPDGF-BB Speeds Fracture Healing
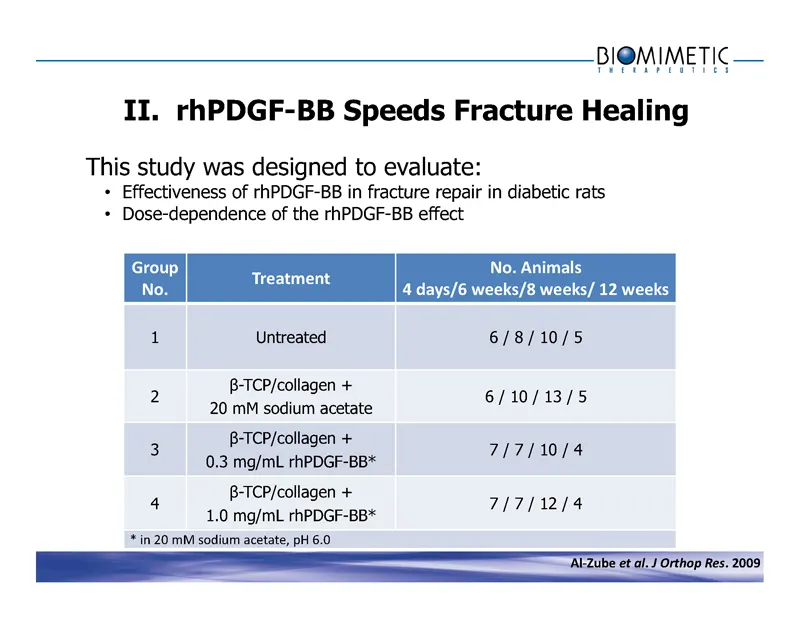
II. rhPDGF -BB Speeds Fracture Healing This study was designed to evaluate: Group3 No.3Animals Treatment No. 43days/63weeks/83weeks/3123weeks 1 Untreated 6 / 8 / 10 / 5 3-TCP/collagen + 2 6 / 10 / 13 / 5 20 mM sodium acetate 3-TCP/collagen + 3 7 / 7 / 10 / 4 0.3 mg/mL rhPDGF -BB* 3-TCP/collagen + 4
Slide 18: rhPDGF-BB Treatment Enhances Fracture Healing in Diabetic Rats
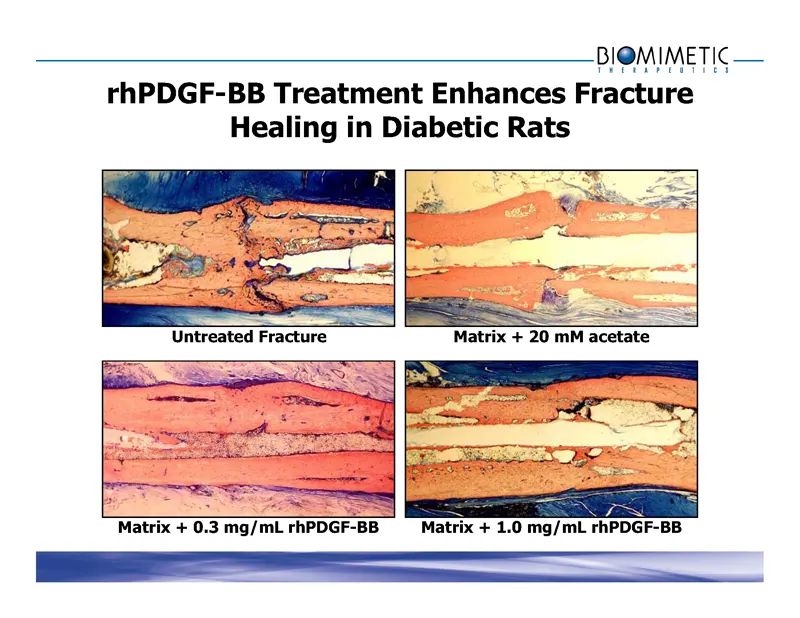
rhPDGF -BB Treatment Enhances Fracture Healing in Diabetic Rats Untreated Fracture Matrix + 20 mM acetate Matrix + 0.3 mg/mL rhPDGF -BB Matrix + 1.0 mg/mL rhPDGF -BB
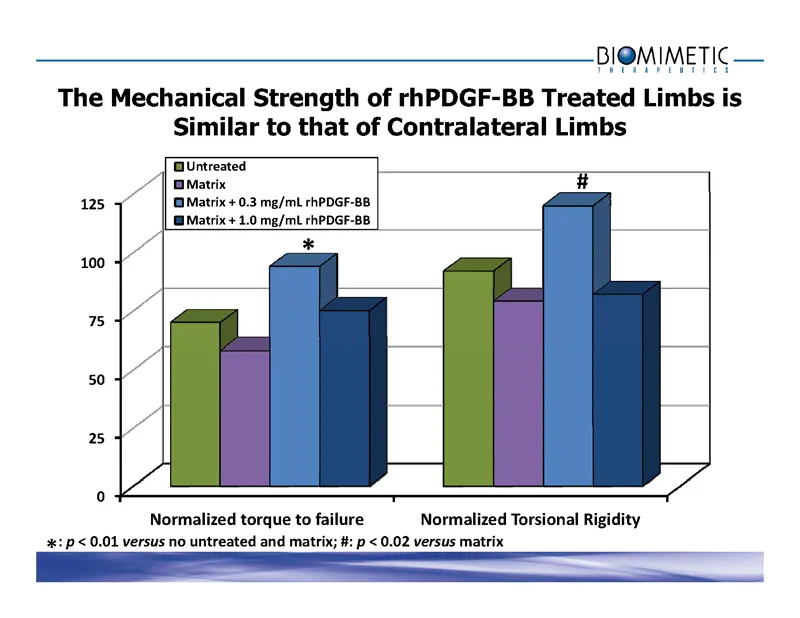
Slide 19: Mechanical Strength of rhPDGF-BB Treated Limbs
The Mechanical Strength of rhPDGF -BB Treated Limbs is Similar to that of Contralateral Limbs Untreated Matrix # 125 Matrix3+30.33mg/mL3rhPDGF3BB Matrix3+31.03mg/mL3rhPDGF3BB * 100 75 50 25 0 Normalized3torque3to3failure Normalized3Torsional3Rigidity *:3p <30.013versus no3untreated3and3matrix;3#:3 p
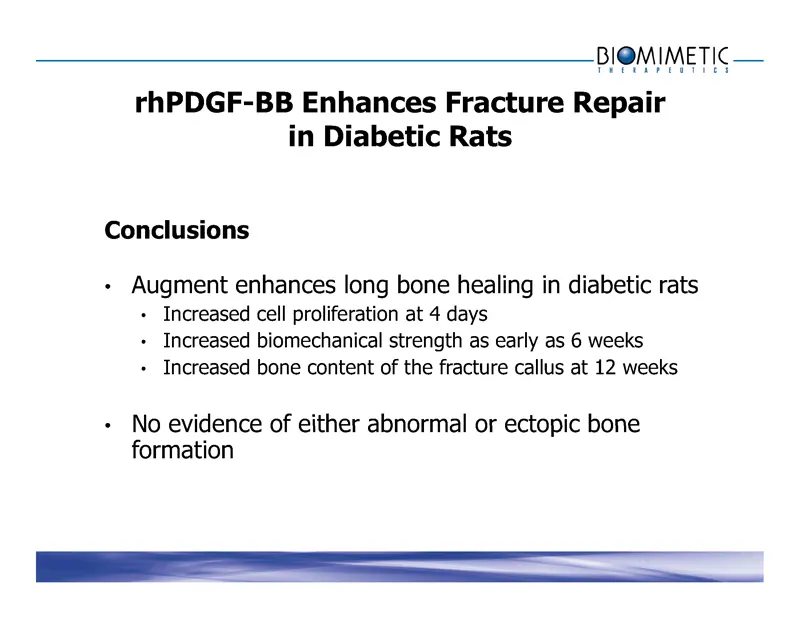
Slide 20: rhPDGF-BB Enhances Fracture Repair in Diabetic Rats
rhPDGF -BB Enhances Fracture Repair in Diabetic Rats Conclusions Augment enhances long bone healing in diabetic rats Increased cell proliferation at 4 days Increased biomechanical strength as early as 6 weeks Increased bone content of the fracture callus at 12 weeks No evidence of either abnormal or
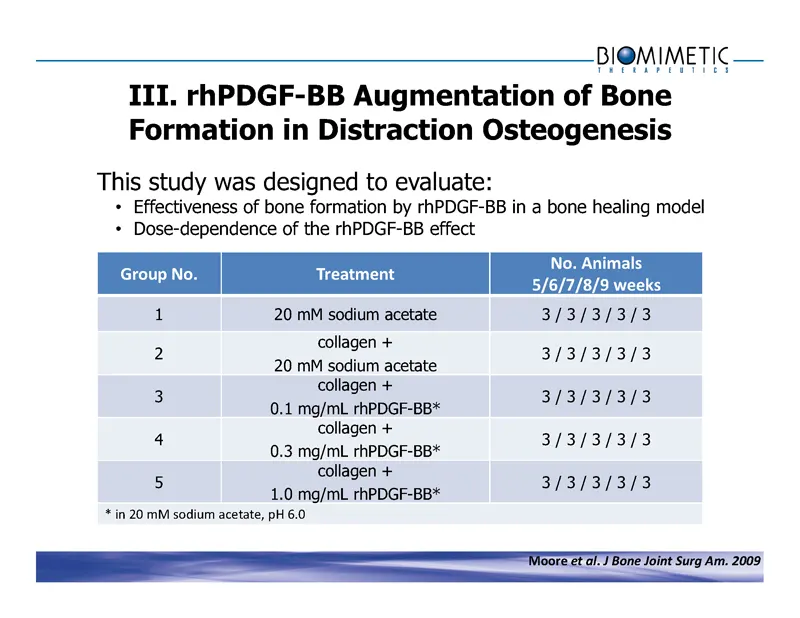
Slide 21: III. rhPDGF-BB Augmentation of Bone Formation in Distraction Osteogenesis
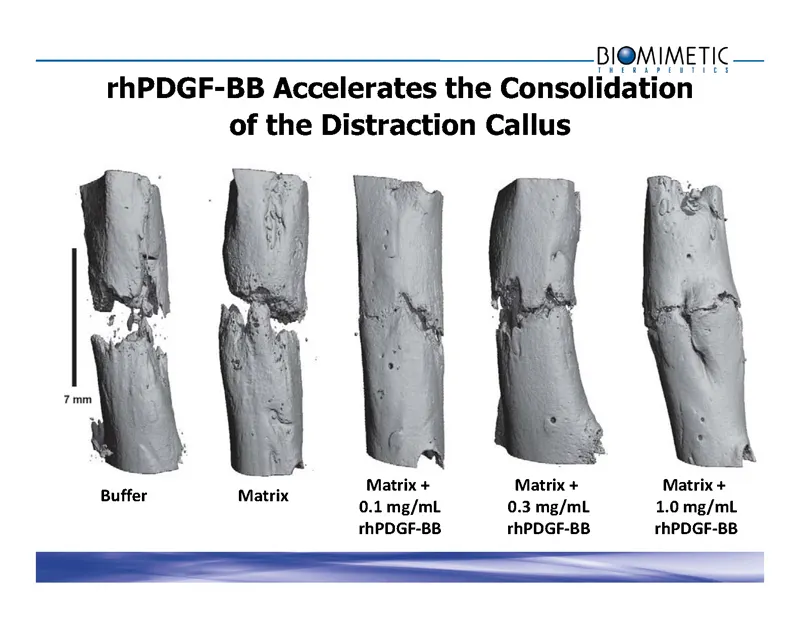
III. rhPDGF -BB Augmentation of Bone Formation in Distraction Osteogenesis This study was designed to evaluate: No.3Animals Group3No . Treatment 5/6/7/8/93weeks 1 20 mM sodium acetate 3 / 3 / 3 / 3 / 3 collagen + 2 3 / 3 / 3 / 3 / 3 20 mM sodium acetate collagen + 3 3 / 3 / 3 / 3 / 3 0.1 mg/mL rhPDG
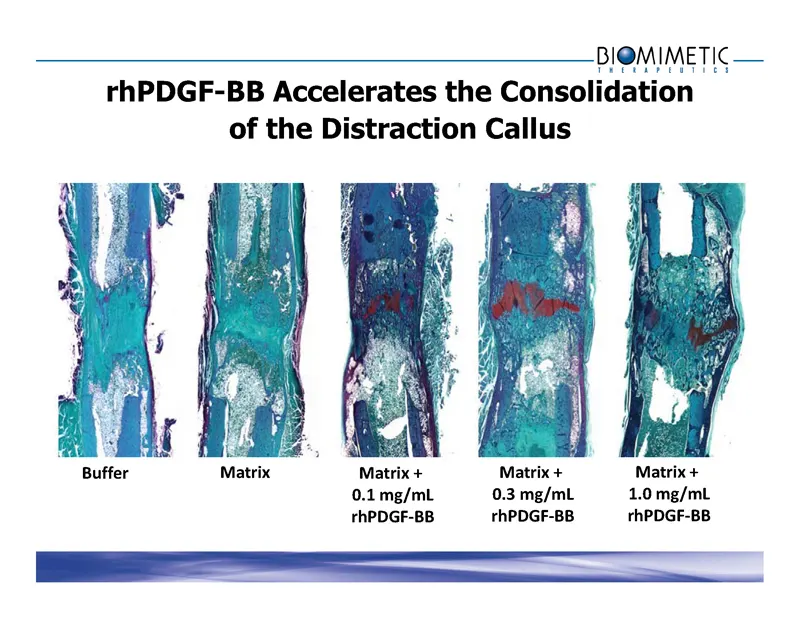
Slide 22: rhPDGF-BB Accelerates Consolidation of the Distraction Callus
rhPDGF -BB Accelerates the Consolidation of the Distraction Callus Buffer Matrix Matrix3+3 Matrix3+3 Matrix3+3 0.13mg/mL 0.33mg/mL 1.03mg/mL rhPDGF3BB rhPDGF3BB rhPDGF3BB
Slide 23: rhPDGF-BB Accelerates Consolidation of the Distraction Callus
rhPDGF -BB Accelerates the Consolidation of the Distraction Callus Matrix3+3 Matrix3+3 Matrix3+3 Buffer Matrix 0.13mg/mL 0.33mg/mL 1.03mg/mL rhPDGF3BB rhPDGF3BB rhPDGF3BB
Slide 24: rhPDGF-BB Accelerates Consolidation of the Distraction Callus
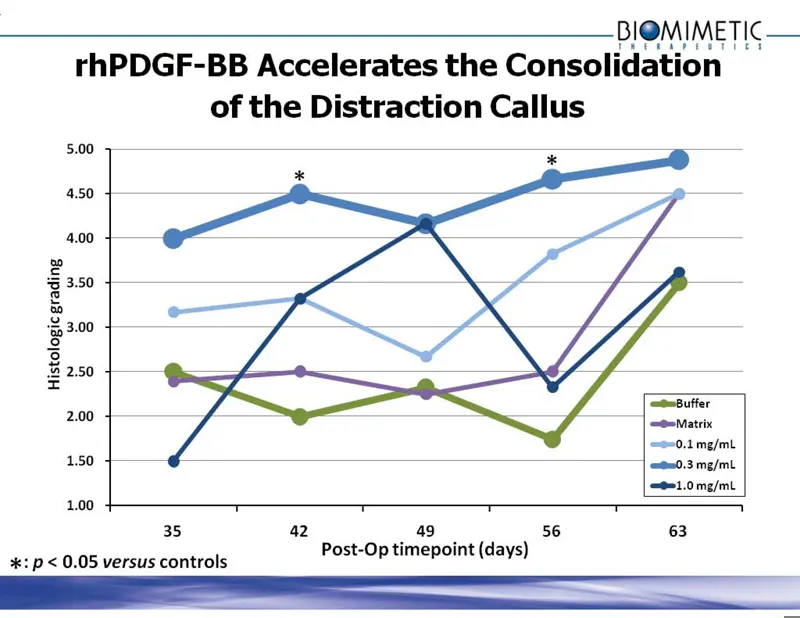
BIOMIMETIC — eta ee rthPDGF-BB Accelerates the Consolidation of the Distraction Callus * Histologic grading o 3 =eabutfer 200 —OMatrix <e0.1 mg/mL 1.50 é 200.3 mg/mL <21.0 mg/ml 1.00 T T T T 7 35 42 56 63 49 +: p < 0.05 versus controls PostOp timepoint (days)
Slide 25: rhPDGF-BB Accelerates Consolidation of the Distraction Callus
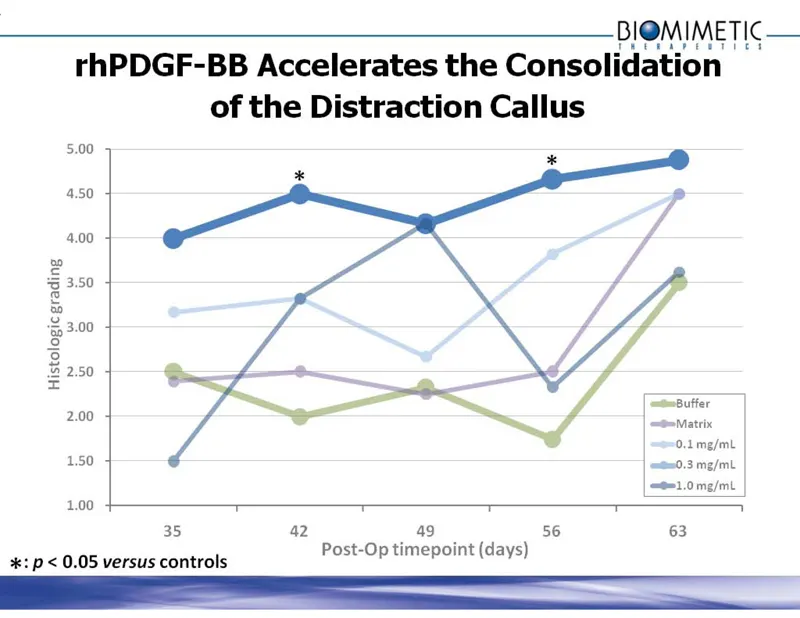
BI IMETIC— rhPDGF-BB Accelerates the Consolidation of the Distraction Callus 4.00 Histologic grading 2.00 +: p < 0.05 versus controls =eaButfer =—O=Matrix 0.1 mg/ml 2020.3 mg/mL 21.0 mg/mt 35 42 56 63 49 Post-Op timepoint (days)
Slide 26: rhPDGF-BB Accelerates Consolidation of the Distraction Callus
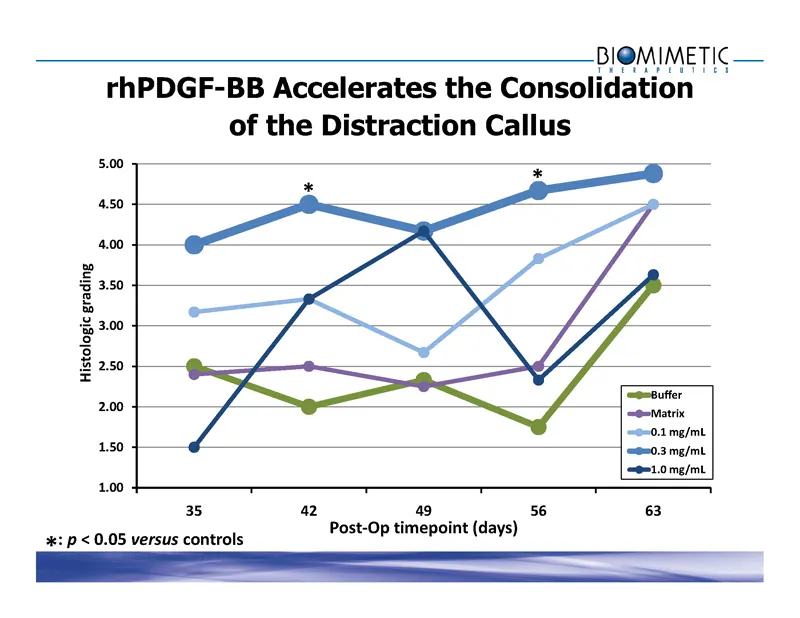
rhPDGF -BB Accelerates the Consolidation of the Distraction Callus 5.00 * * 4.50 4.00 3.50 logic3grading 3.00 Histo 2.50 Buffer 2.00 Matrix 0.13mg/mL 1.50 0.33mg/mL 1.03mg/mL 1.00 35 42 49 56 63 Post3Op3timepoint3(days) *:3p <30.053versus controls
Slide 27: rhPDGF-BB Increases Bone Formation in a Model of Bone Healing
rhPDGF -BB Increases Bone Formation in a Model of Bone Healing Conclusions rhPDGF -BB increased new bone formation rhPDGF -BB decreased non-union rates No adverse events were noted
Slide 28: IV. Augment Compares Favorably to Autograft in Ovine Spine Fusion
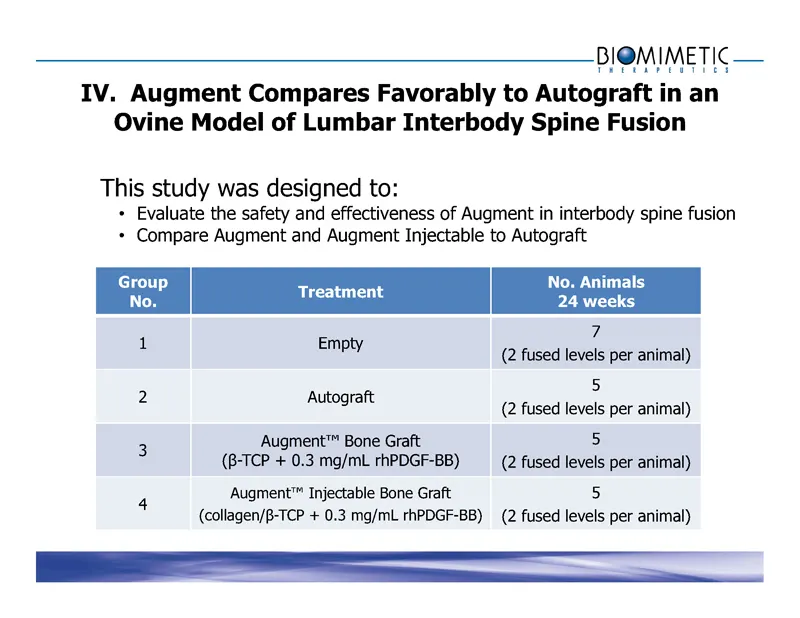
IV. Augment Compares Favorably to Autograft in an Ovine Model of Lumbar Interbody Spine Fusion This study was designed to: Group No. Animals Treatment No. 24 weeks 7 1 Empty (2 fused levels per animal) 5 2 Autograft (2 fused levels per animal) Augment™ Bone Graft 5 3 (3-TCP + 0.3 mg/mL rhPDGF -BB) (
Slide 29: Graft Materials Delivered in a PEEK Vertebral Spacer
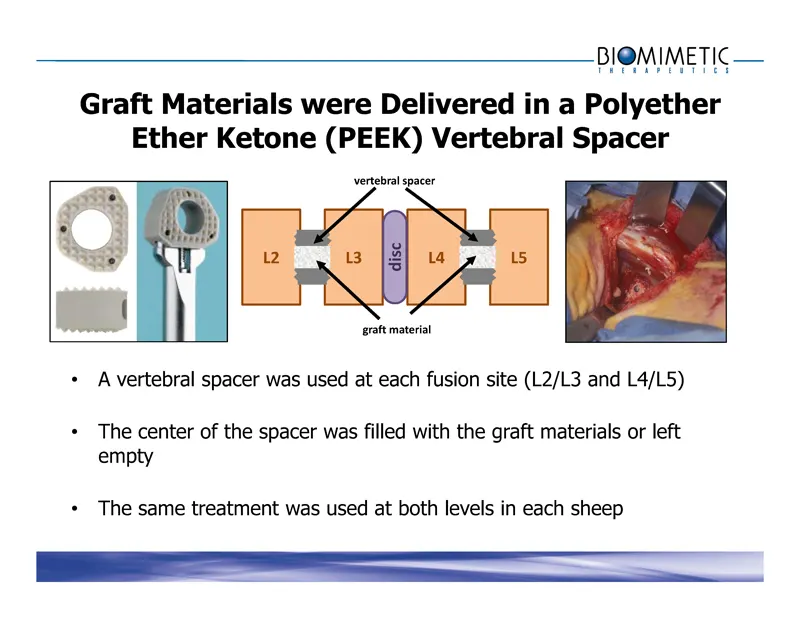
Graft Material s were Delivere d in a Polyether Ether Ketone (PEEK) Vertebral Spacer vertebral3spacer L2 L3 isc L4 L5 d graft3material A vertebral spacer was used at each fusion site (L2/L3 and L4/L5) The center of the spacer was filled with the graft materials or left empty The same treatment was u
Slide 30: 3D Reconstructions
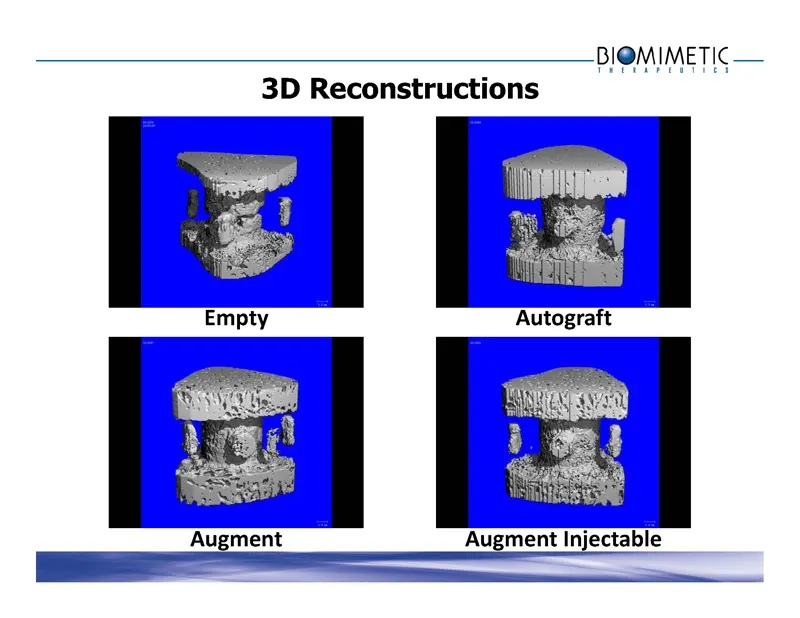
3D Reconstructions Empty Autograft Augment Augment3Injectable
Slide 31: Augment Promotes Interbody Fusion by MicroCT and Histology
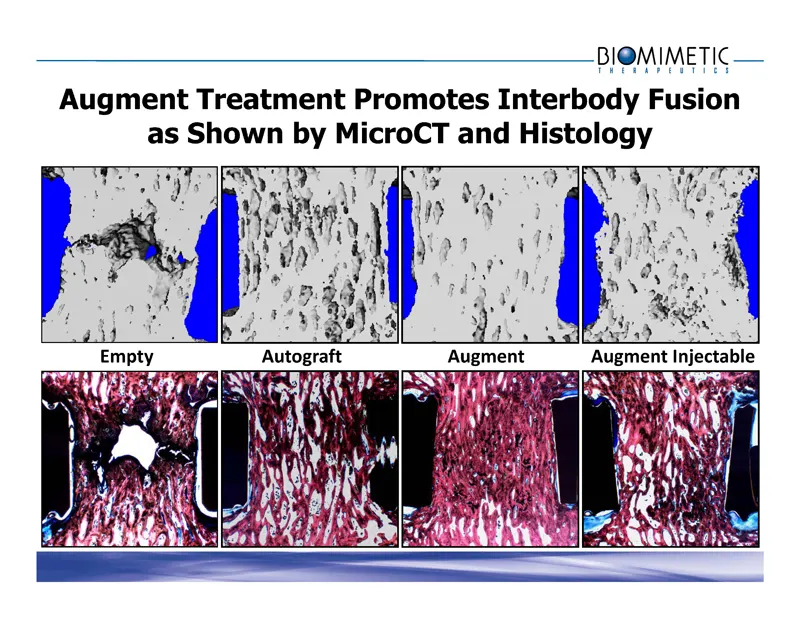
Augment Treatment Promotes Interbod y Fusion as Shown by MicroCT and Histology Empty Autograft Augment Augment3Injectable
Slide 32: Augment Increases Interbody Fusion
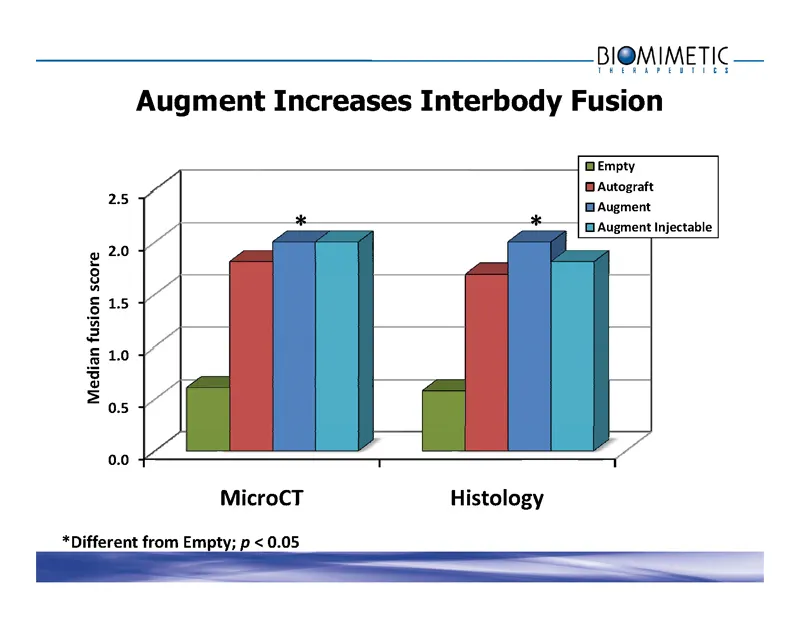
Augment Increases Interbod y Fusion Empty Autograft 2.5 Augment * * Augment3Injectable 2.0 re 3fusion3sco 1.5 Median 1.0 0.5 0.0 MicroCT Histology *Different3from3Empty;3 p <30.05

Slide 33: Augment Promotes Lumbar Interbody Spine Fusion in an Ovine Model
Augment Promotes Lumbar Interbody Spine Fusion in an Ovine Model Conclusions Augment -treated specimens had the highest fusion scores of all groups evaluated Augment significantly promoted interbody spine fusion compared to empty PEEK spacers Augment was equivalent to autograft
Slide 34: V. Augment Comparable to Autograft in Canine Carpus Arthrodesis
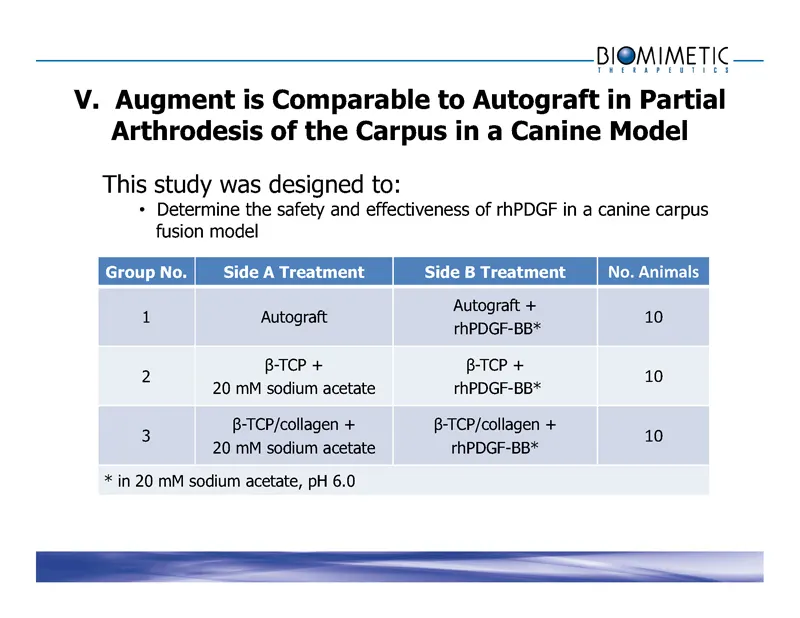
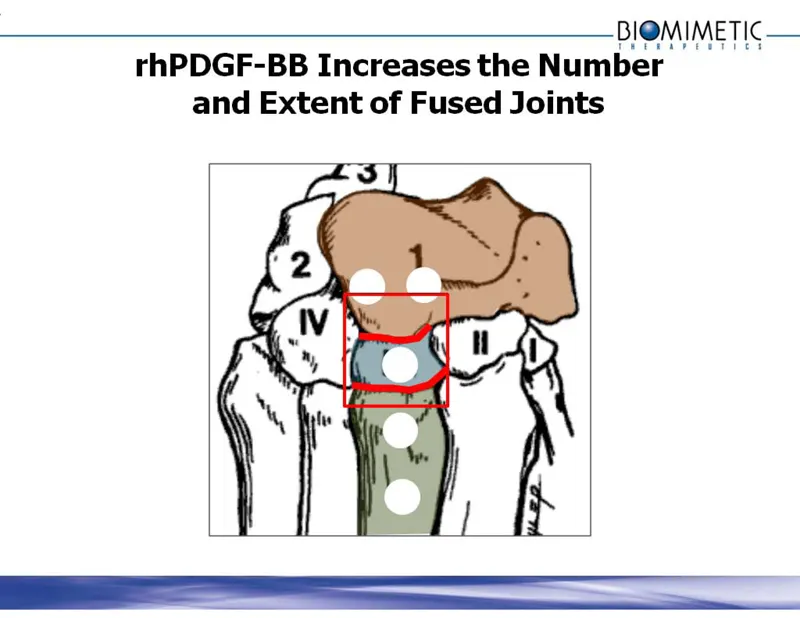
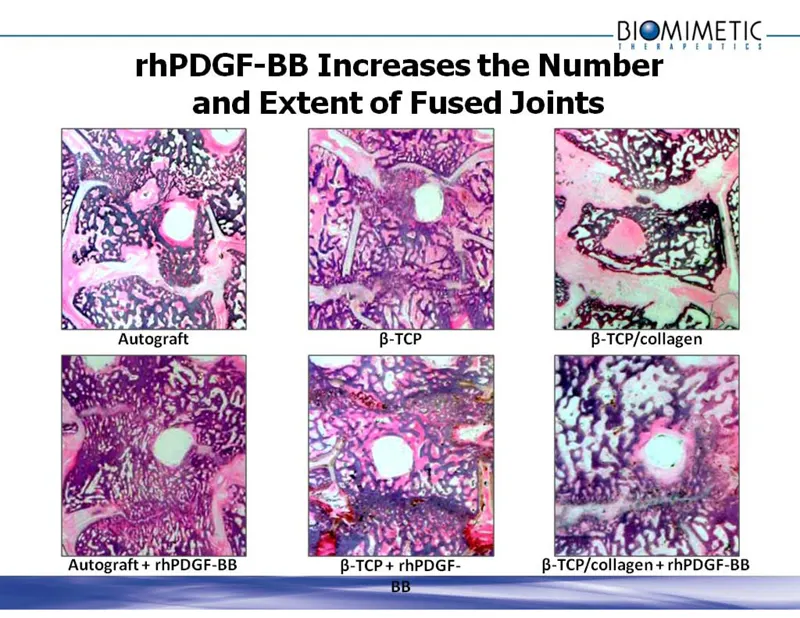
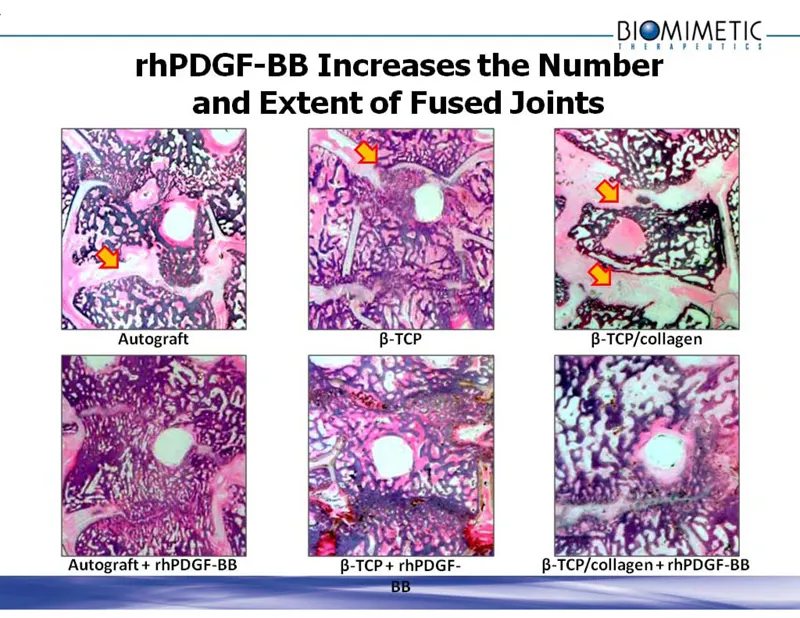
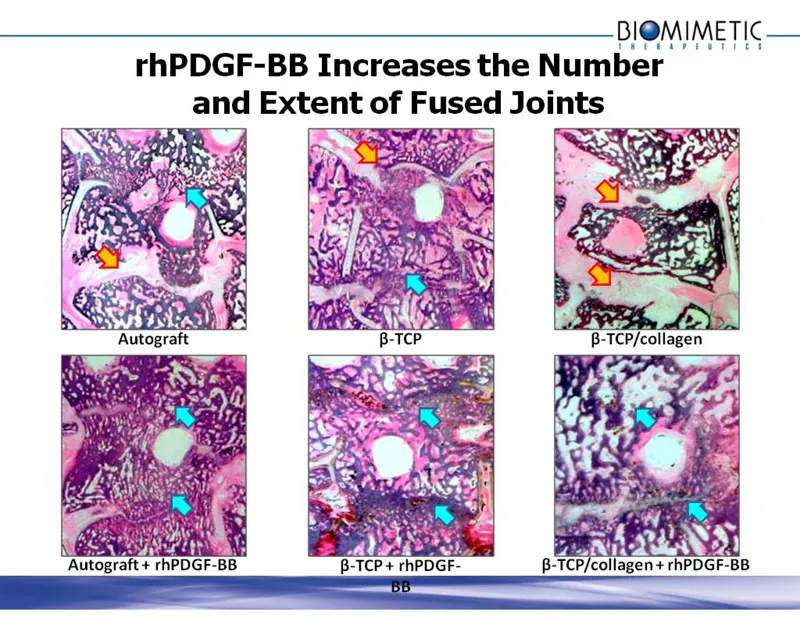
V. Augment is Comparable to Autograft in Partial Arthrodesis of the Carpus in a Canine Model This study was designed to: Group No. Side A Treatment Side B Treatment No.3Animals Autograft + 1 Autograft 10 rhPDGF -BB* 3-TCP + 3-TCP + 2 10 20 mM sodium acetate rhPDGF -BB* 3-TCP/collagen + 3-TCP/collage
Slide 35: rhPDGF-BB Increases the Number and Extent of Fused Joints
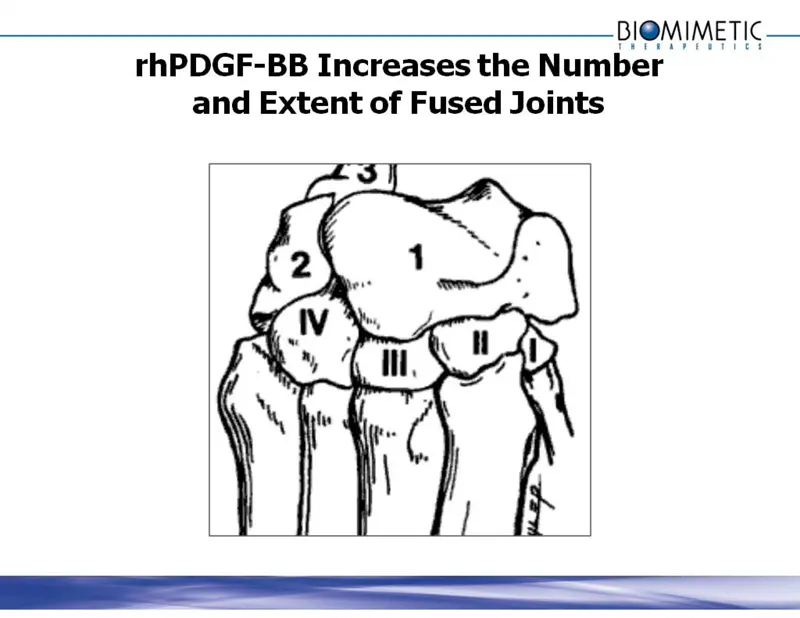
BI@MIMETIC — rhPDGF-BB Increases the Number and Extent of Fused Joints
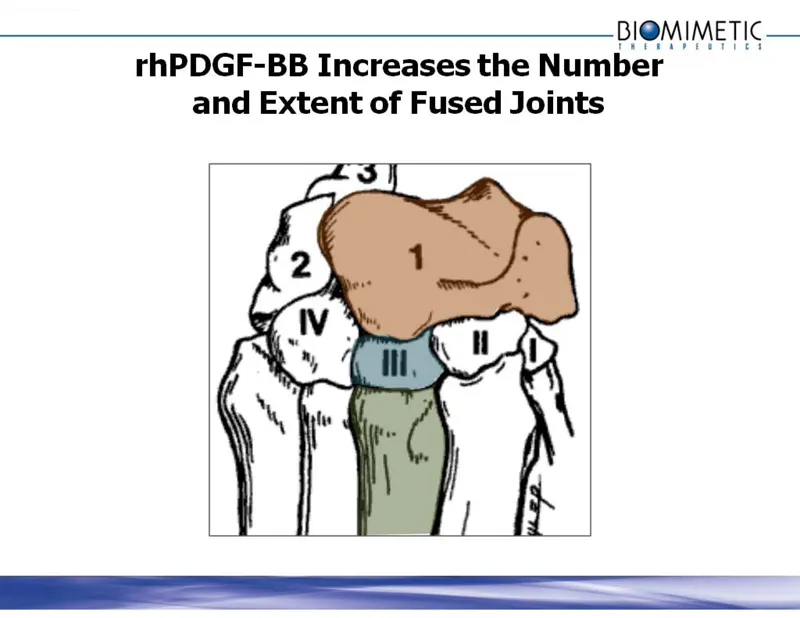
Slide 36: rhPDGF-BB Increases the Number and Extent of Fused Joints
BI@MIMETIC — reerireavicd rthPDGF-BB Increases the Number and Extent of Fused Joints
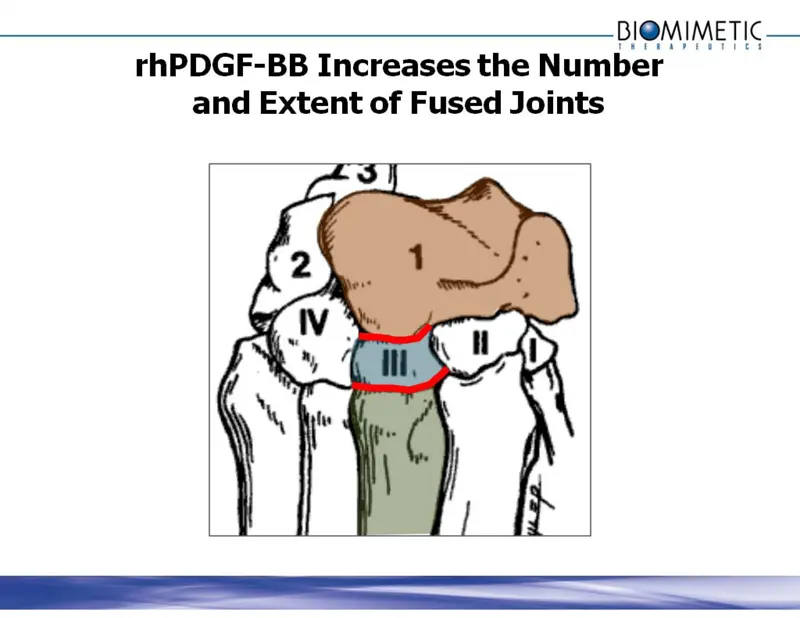
Slide 37: rhPDGF-BB Increases the Number and Extent of Fused Joints
BI@MIMETIC — reerireavicd rthPDGF-BB Increases the Number and Extent of Fused Joints
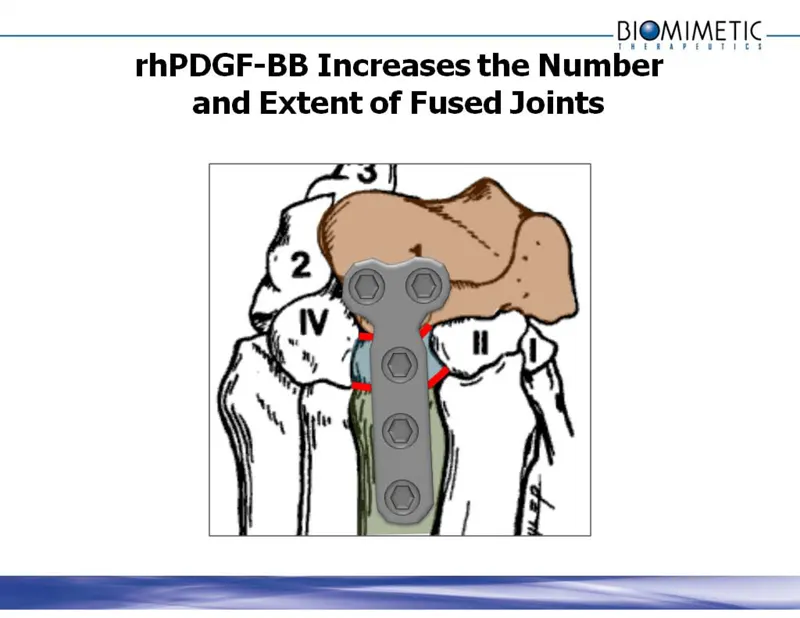
Slide 38: rhPDGF-BB Increases the Number and Extent of Fused Joints
BI@MIMETIC — reerireavicd rthPDGF-BB Increases the Number and Extent of Fused Joints
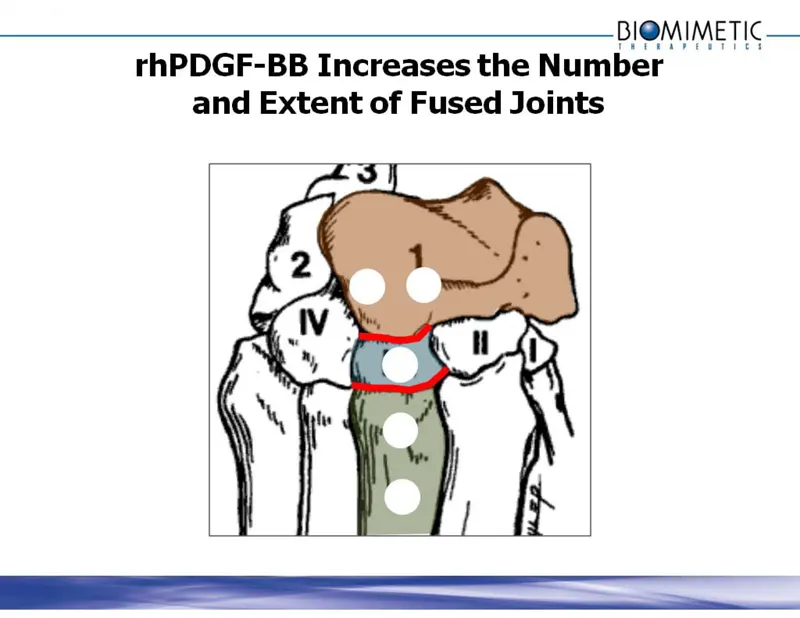
Slide 39: rhPDGF-BB Increases the Number and Extent of Fused Joints
BI@MIMETIC — reerireavicd rthPDGF-BB Increases the Number and Extent of Fused Joints
Slide 40: rhPDGF-BB Increases the Number and Extent of Fused Joints
BI@MIMETIC — reerireavicd rthPDGF-BB Increases the Number and Extent of Fused Joints
Slide 41: rhPDGF-BB Increases the Number and Extent of Fused Joints
receipenri rthPDGF-BB Increases the Number and Extent of Fused Joints BI@MIMETIC—
Slide 42: rhPDGF-BB Increases the Number and Extent of Fused Joints
receipenri rthPDGF-BB Increases the Number and aa of Fused Joints BI@MIMETIC—
Slide 43: rhPDGF-BB Increases the Number and Extent of Fused Joints
BI@MIMETIC— receipenri rthPDGF-BB Increases the Number and aa of Fused Joints
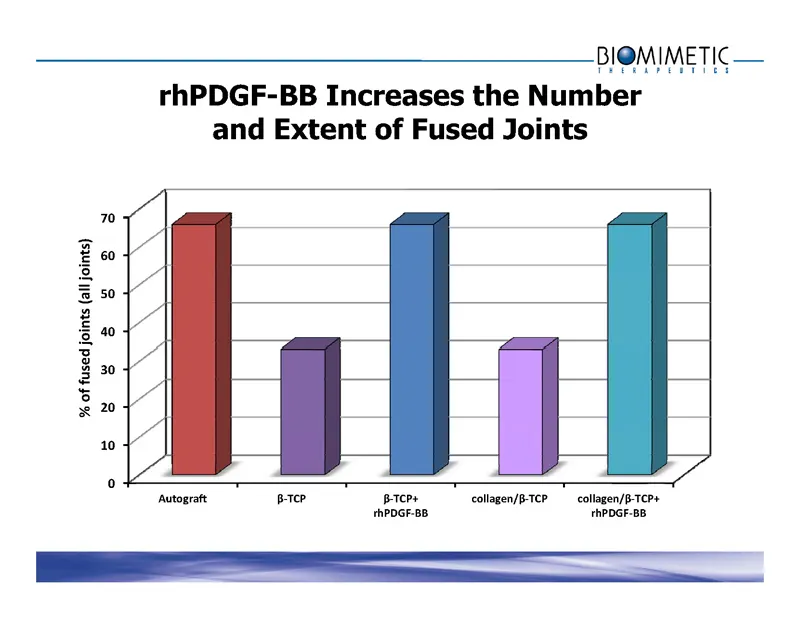
Slide 44: rhPDGF-BB Increases the Number and Extent of Fused Joints
rhPDGF -BB Increases the Number and Extent of Fused Joints 70 ints) 60 50 joints3(all3jo 40 30 %3of3fused3 20 10 0 Autograft 33TCP 33TCP+ collagen/33TCP collagen/33TCP+ rhPDGF3BB rhPDGF3BB
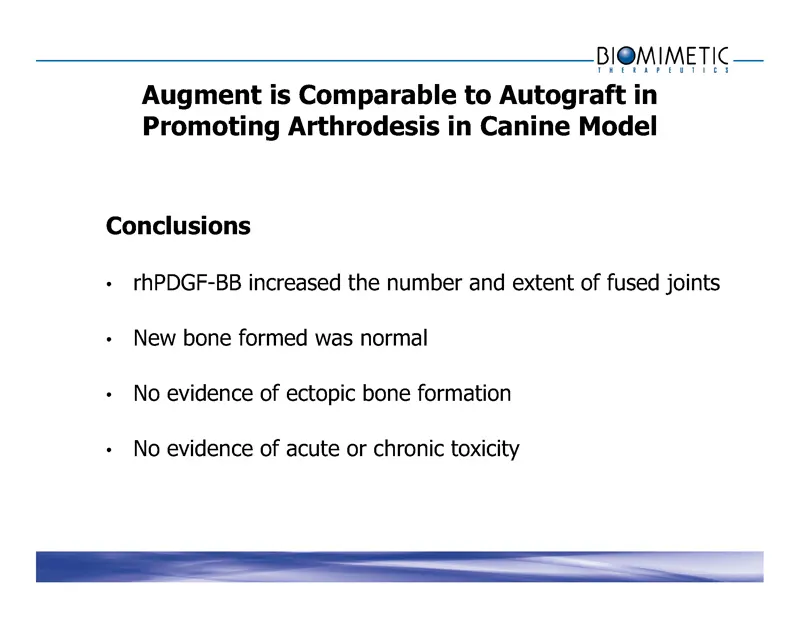
Slide 45: Augment Comparable to Autograft in Canine Arthrodesis: Conclusions
Augment is Comparable to Autograft in Promoting Arthrodesis in Canine Model Conclusions rhPDGF -BB increased the number and extent of fused joints New bone formed was normal No evidence of ectopic bone formation No evidence of acute or chronic toxicity

Slide 46: Augment Clinical Data
Augment Clinical Data Judith F. Baumhauer, MD Professor and Associate Chair of Academic Affairs Department of Orthopaedic Surgery Foot and Ankle Division Universit y of Rochester School of Medicine and Dentistr y www.biomimetics .com

Slide 47: Autograft Needs Alternatives
Autograft Needs Alternatives •Frequently used in conjunction with fusions Autograft is the gold standard, but . . . Graft site pain and morbidity Limited availability Increased operative time, blood loss, recovery time Alternatives to autograft are many and varied (e.g. allograft, demineralized bone
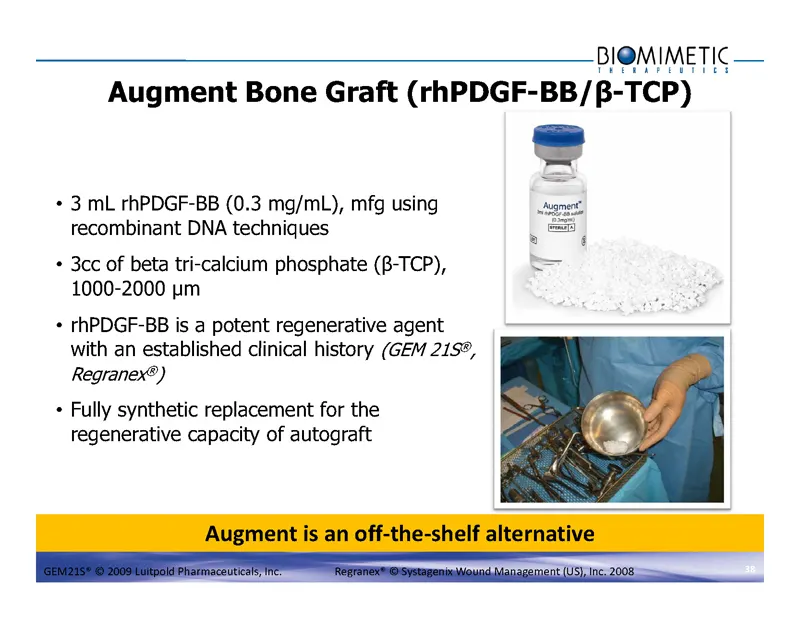
Slide 48: Augment Bone Graft (rhPDGF-BB/β-TCP)
Augment Bone Graft (rhPDGF -BB/3-TCP) Augment3is3an3off3the3shelf3alternative GEM21S®3©320093Luitpold3Pharmaceuticals,3Inc . Regranex®3©3Systagenix3Wound3Management3(US),3Inc .32008 3 mL rhPDGF -BB (0.3 mg/mL), mfg using recombinant DNA techniques 3cc of beta tri-calcium phosphate (3-TCP), 1000-2000
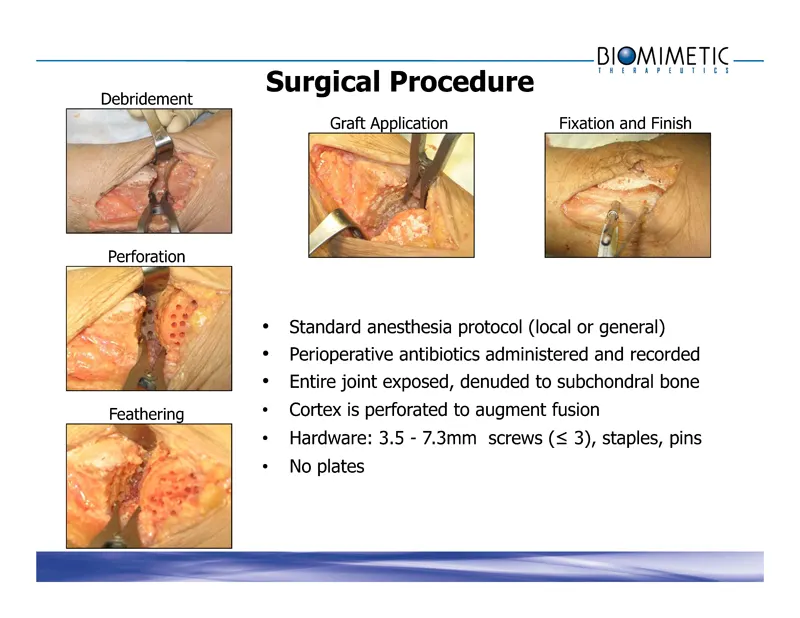
Slide 49: Surgical Procedure
Surgical Procedure Debridement Perforation Feathering Graft Application Fixation and Finish Standard anesthesia protocol (local or general) Perioperative antibiotics administered and recorded Entire joint exposed, denuded to subchondral bone Cortex is perforated to augment fusion Hardware: 3.5 - 7.3

Slide 50: Preparation and Implantation
BI@MIMETIC— reeriree Preparation and Implantation « Augmentis packaged in a single use kit

Slide 51: Preparation and Implantation
Preparation and Implantation Augment is packaged in a single use kit Hydrate TCP with rhPDGF-BB (1:1) using aseptic technique Let sit for 10 minutes
Slide 52: Preparation and Implantation
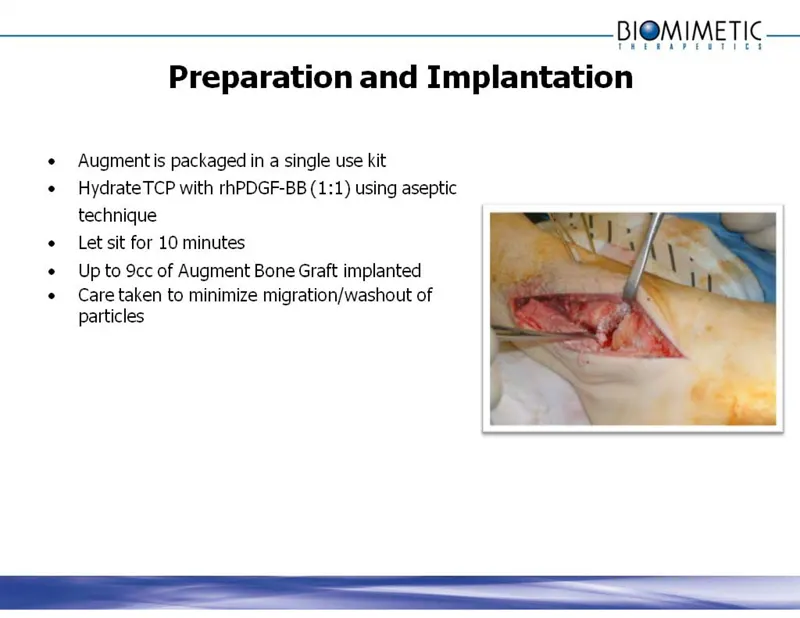
HOMIMETIG — Preparation and Implantation Augment is packaged in a single use kit Hydrate TCP with rhPDGF-BB (1:1) using aseptic technique Let sit for 10 minutes Up to 9cc of Augment Bone Graft implanted Care taken to minimize migration/washout of particles

Slide 53: Preparation and Implantation
Augment is packaged in a single use kit Hydrate TCP with rhPDGF-BB (1:1) using aseptic technique Let sit for 10 minutes Up to 9cc of Augment Bone Graft implanted Care taken to minimize migration/washout of particles Graft placed to maximize contact with osseous surfaces Remaining PDGF dispensed onto
Slide 54: Conclusions from Early Augment Trials
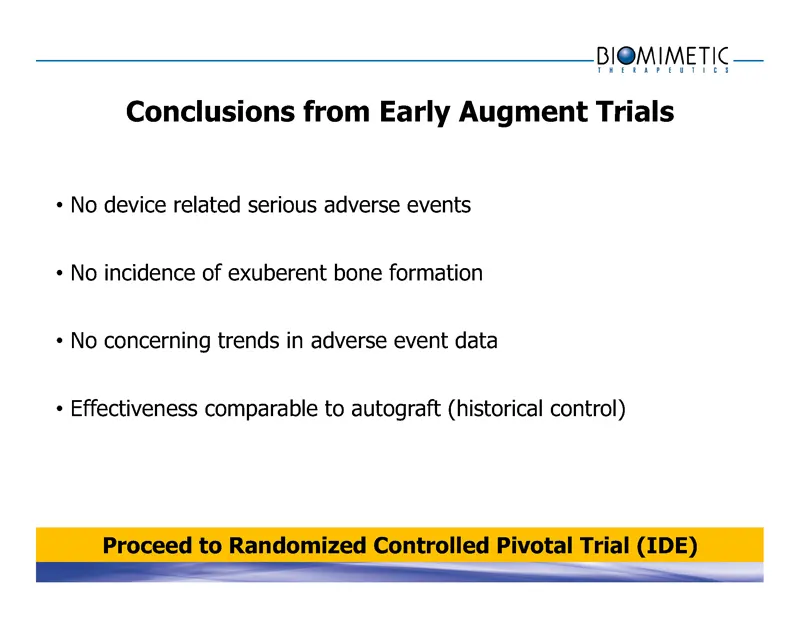
Conclusions from Early Augment Trials Proceed to Randomized Controlled Pivotal Trial (IDE) No device related serious adverse events No incidence of exuberent bone formation No concerning trends in adverse event data Effectiveness comparable to autograft (historical control)

Slide 55: Pivotal Trial Design
Pivotal Trial Design www.biomimetics .com
Slide 56: Augment Pivotal Clinical Trial
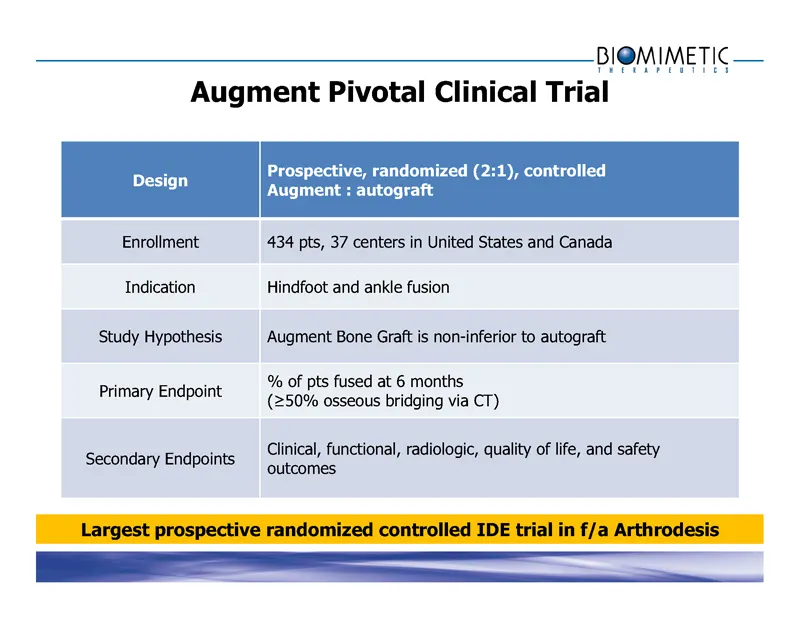
Augment Pivotal Clinical Trial Prospective, randomized (2:1), controlled Design Augment : autograft Enrollment 434 pts, 37 centers in United States and Canada Indication Hindfoot and ankle fusion Study Hypothesis Augment Bone Graft is non-inferior to autograft % of pts fused at 6 months Primary Endp
Slide 57: Patient Disposition and Evaluability
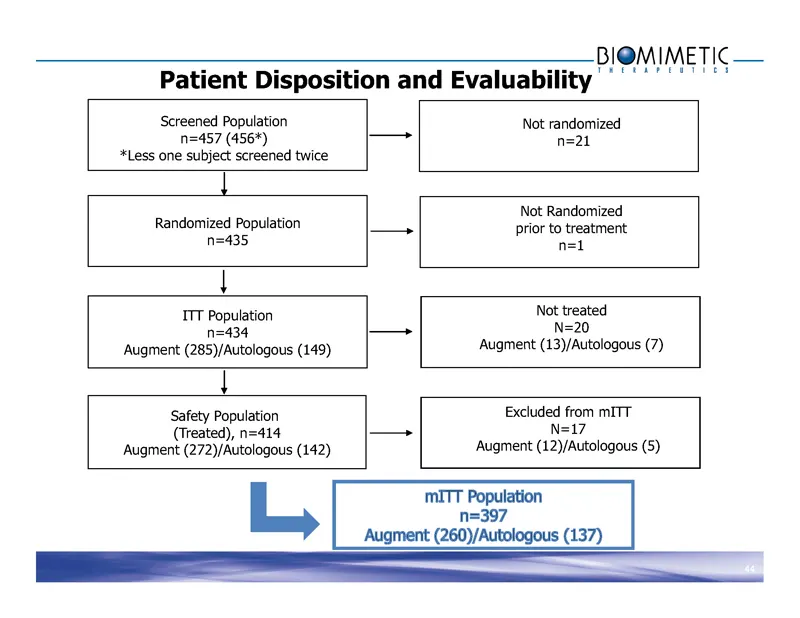
Patient Disposition and Evaluability Screened Population Not randomized n=457 (456*) n=21 *Less one subject screened twice Not Randomized Randomized Population prior to treatment n=435 n=1 ITT Population Not treated n=434 N=20 Augment (285)/Autologous (149) Augment (13)/Autologous (7) Safety Populat
Slide 58: Primary Endpoint
Primary Endpoint Fusion of the full complement of joints 3 50% osseous bridging as assessed by the independent radiologist at 24 weeks postoperatively
Slide 59: Augment Non-inferior to Autograft for Primary Endpoint
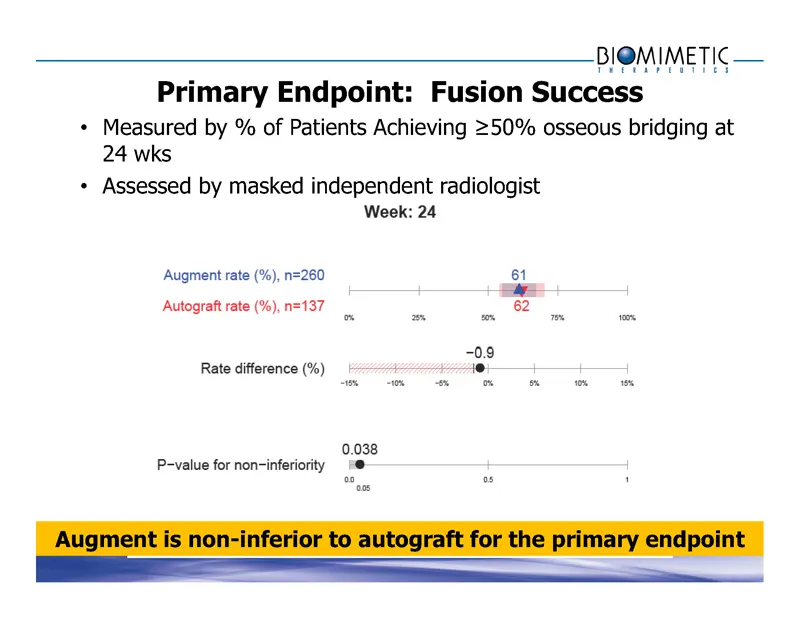
• Measured by % of Patients Achieving 350% osseous bridging at 24 wks • Assessed by masked independent radiologist Augment is non-inferior to autograft for the primary endpoint
Slide 60: BI@MIMETIC —
BI@MIMETIC — Peerireavicd
Slide 61: BI@MIMETIC—
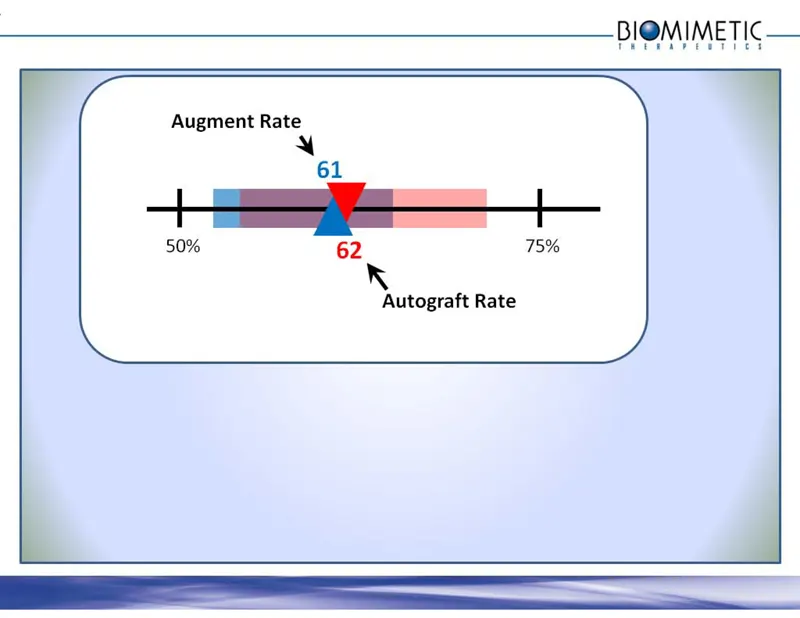
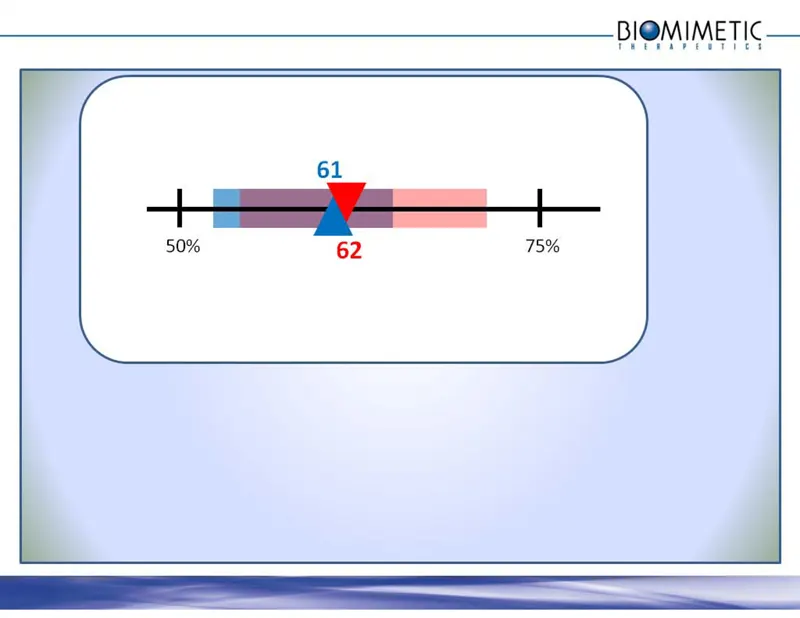
BI@MIMETIC— ; Augment Rate | N 61 50% 62 75% Autograft Rate
Slide 62: BI@MIMETIC —
BI@MIMETIC — Peerireavicd
Slide 63: Augment and Autograft 95% Confidence Intervals
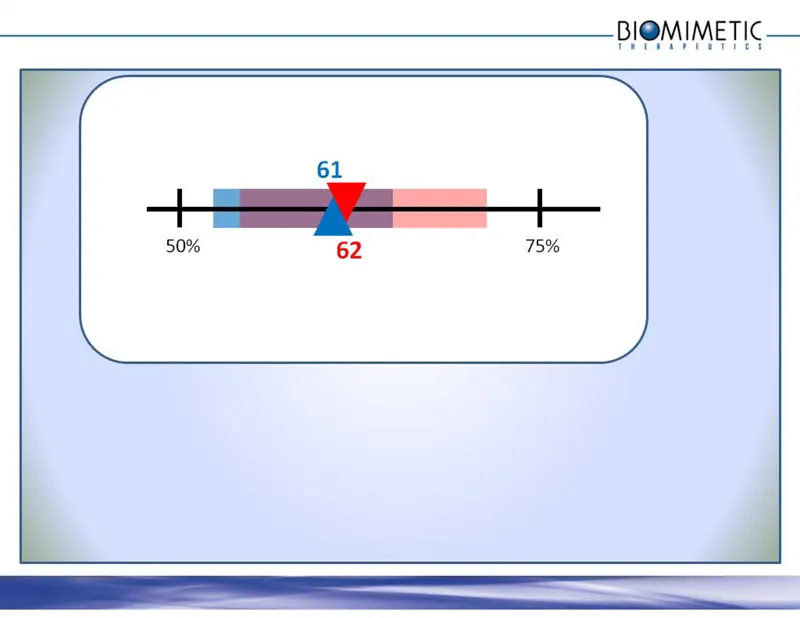
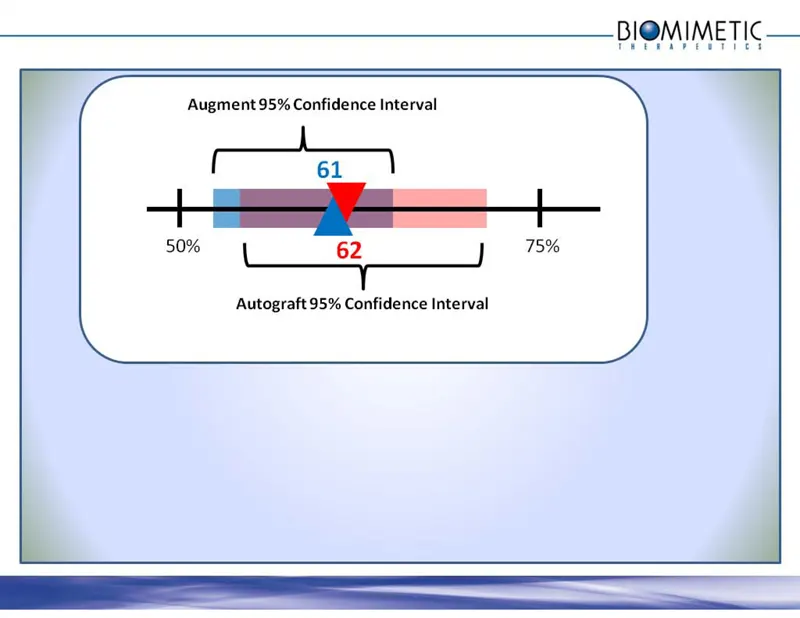
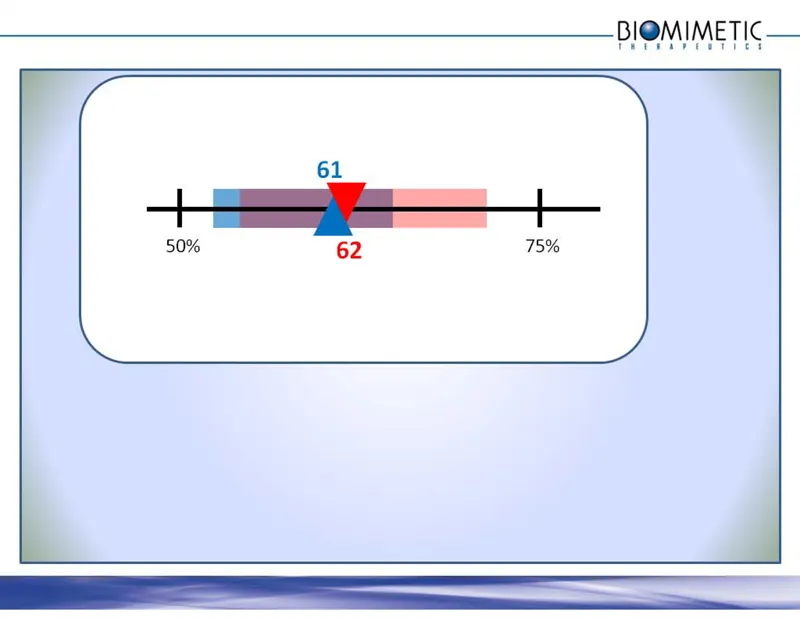
Pr Augment 95% Confidence Interval { 61 | 50% 62 75% aS a (_—s__j Autograft 95% Confidence Interval
Slide 64: BI@MIMETIC —
BI@MIMETIC — Peerireavicd
Slide 65: Favors Autograft / Favors Augment
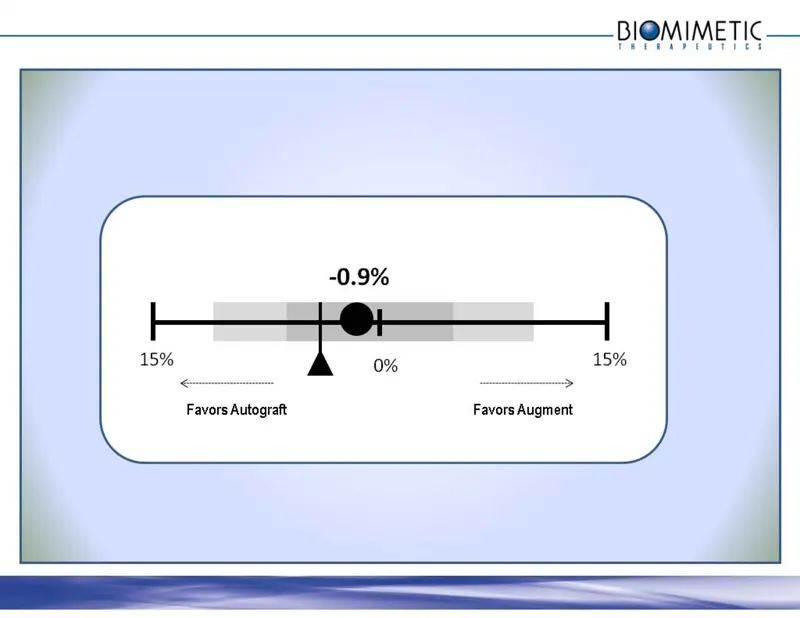
BI@MIMETIC— Favors Autograft Favors Augment
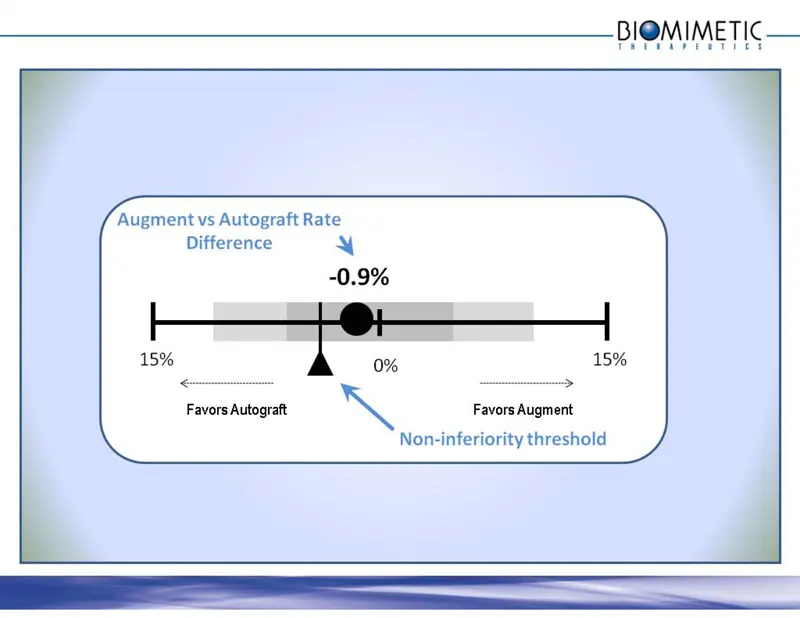
Slide 66: Augment vs Autograft Rate Difference
‘Augment vs Autograft Rate Difference Favors Autograft N -0.9% ee Favors Augment 15% Non-inferiority threshold
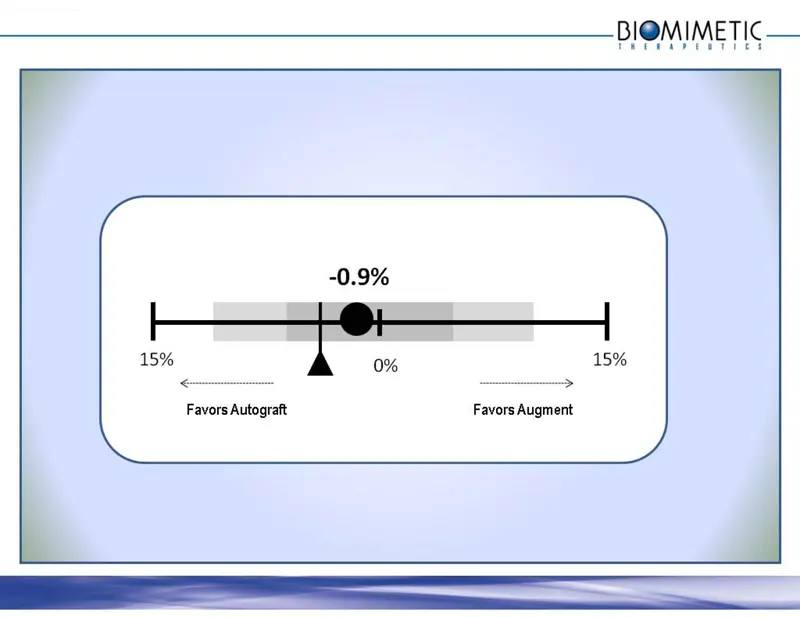
Slide 67: Favors Autograft / Favors Augment
BI@MIMETIC— Favors Autograft Favors Augment
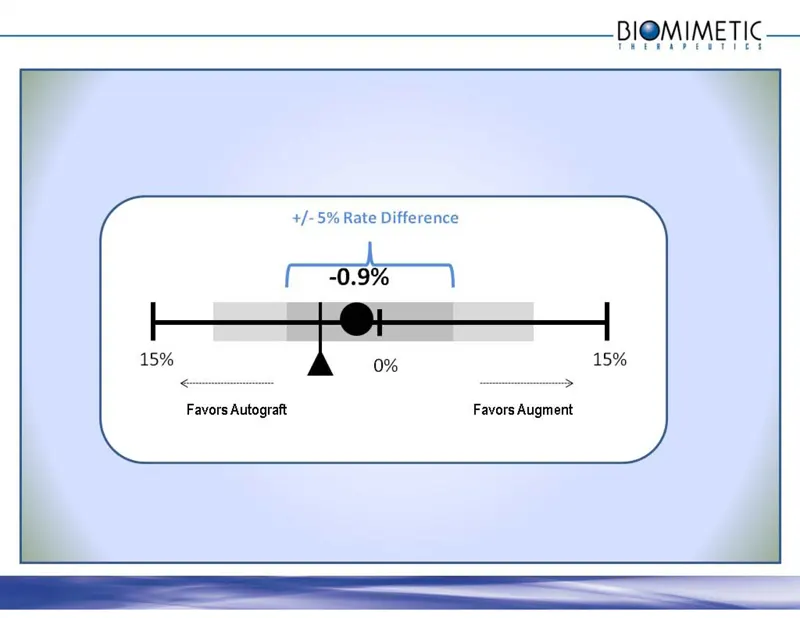
Slide 68: Rate Difference
Favors Autograft +/-5% Rate Difference Favors Augment

Slide 69: Peerireavicd
Peerireavicd
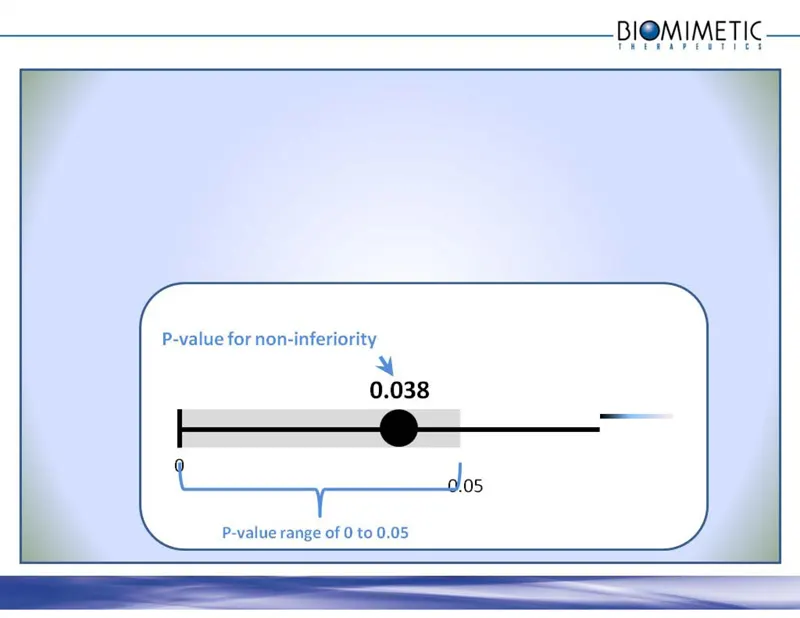
Slide 70: P-value for Non-inferiority
P-value for non-inferiority N 0.038 ; @ q a P-value range of 0 to 0.05 a eE———__——
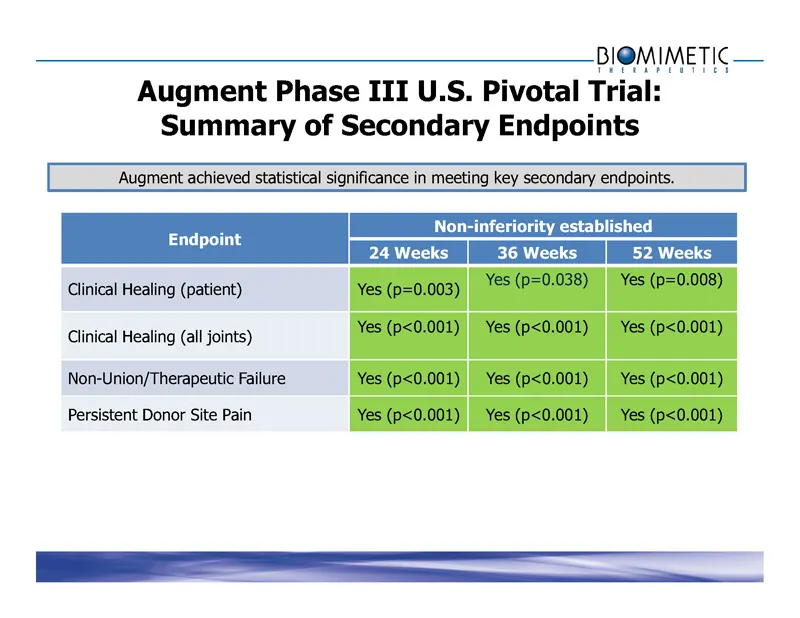
Slide 71: Summary of Secondary Endpoints
Augment Phase III U.S. Pivotal Trial: Summary of Secondary Endpoints Augment achieved statistical significance in meeting key secondary endpoints . Non-inferiority established Endpoint 24 Weeks 36 Weeks 52 Weeks Yes (p=0.038) Yes (p=0.008) Clinical Healing (patient) Yes (p=0.003) Yes (p<0.001) Yes (
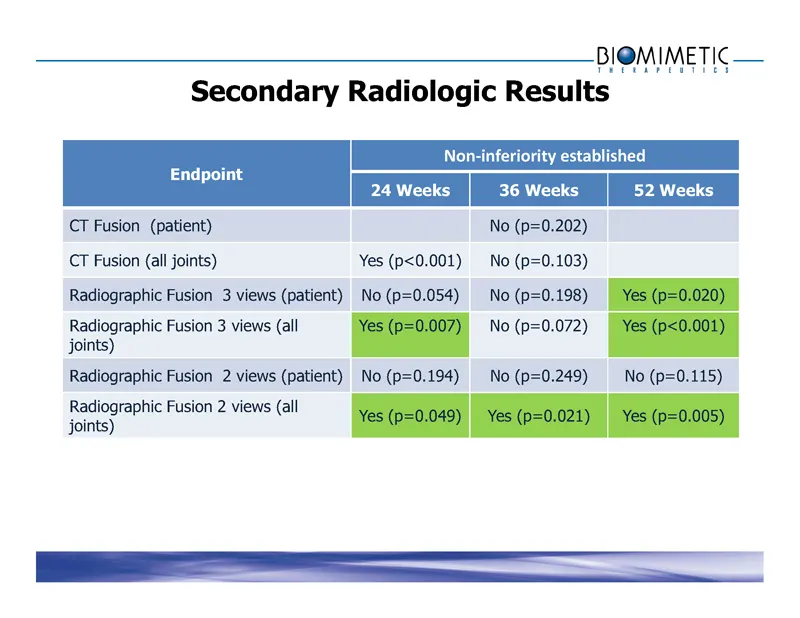
Slide 72: Secondary Radiologic Results
Secondary Radiologic Results Non3inferiority3established Endpoint 24 Weeks 36 Weeks 52 Weeks CT Fusion (patient) No (p=0.202) CT Fusion (all joints) Yes (p<0.001) No (p=0.103) Radiographic Fusion 3 views (patient) No (p=0.054) No (p=0.198) Yes (p=0.020) Radiographic Fusion 3 views (all Yes (p=0.007)
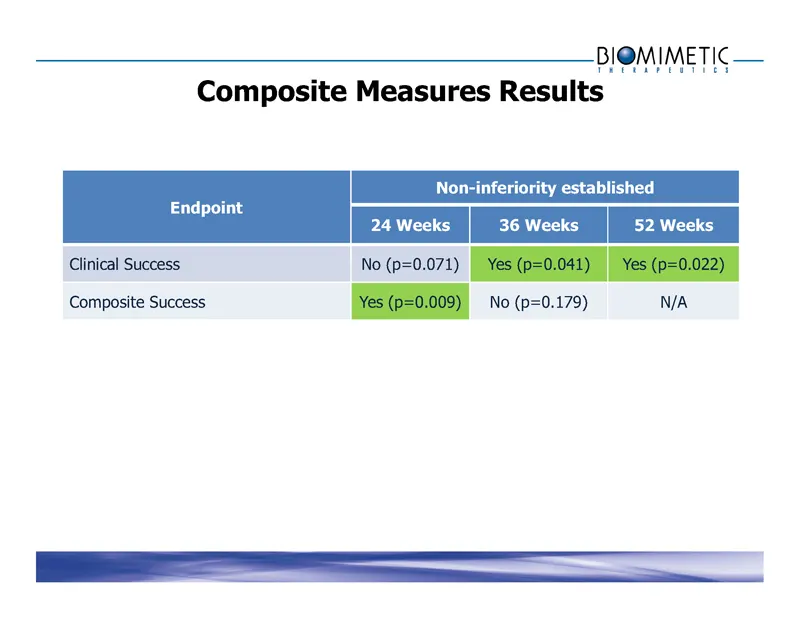
Slide 73: Composite Measures Results
Composite Measures Results Non-inferiority established Endpoint 24 Weeks 36 Weeks 52 Weeks Clinical Success No (p=0.071) Yes (p=0.041) Yes (p=0.022) Composite Success Yes (p=0.009) No (p=0.179) N/A
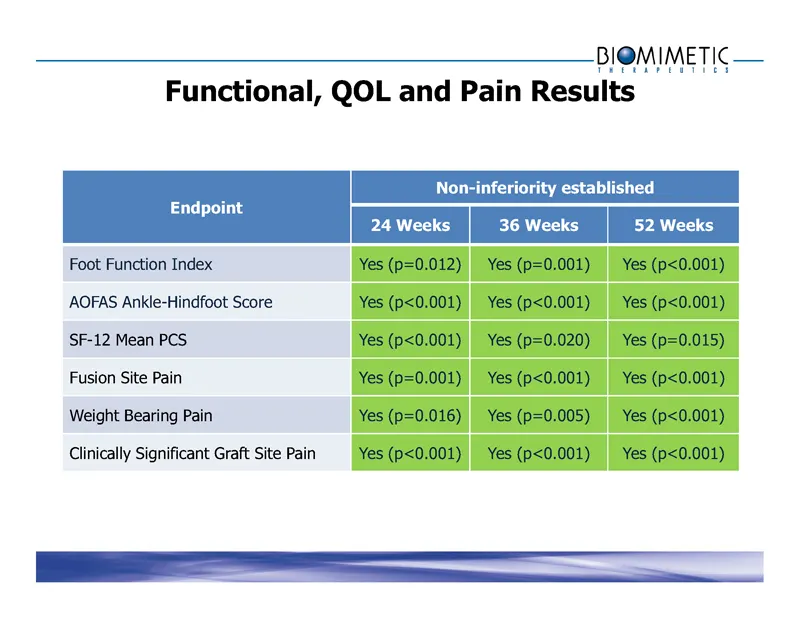
Slide 74: Functional, QOL and Pain Results
Functional, QOL and Pain Results Non-inferiority established Endpoint 24 Weeks 36 Weeks 52 Weeks Foot Function Index Yes (p=0.012) Yes (p=0.001) Yes (p<0.001) AOFAS Ankle-Hindfoot Score Yes (p<0.001) Yes (p<0.001) Yes (p<0.001) SF-12 Mean PCS Yes (p<0.001) Yes (p=0.020) Yes (p=0.015) Fusion Site Pai

Slide 75: Product Safety
Product Safety www.biomimetics .com
Slide 76: Safety Outcomes
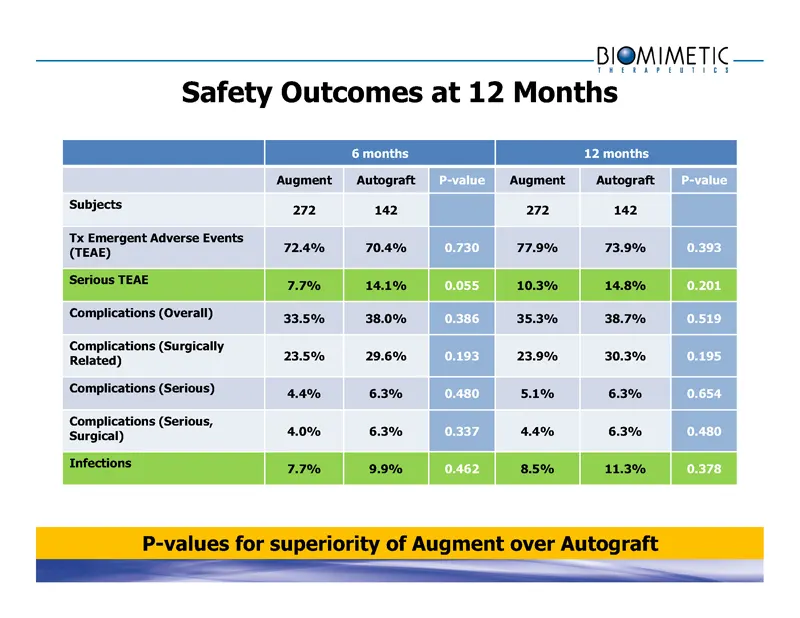
Safety Outcomes at 12 Months 6 months 12 months Augment Autograft P-value Augment Autograft P-value Subjects 272 142 272 142 Tx Emergent Adverse Events (TEAE) 72.4% 70.4% 0.730 77.9% 73.9% 0.393 Serious TEAE 7.7% 14.1% 0.055 10.3% 14.8% 0.201 Complications (Overall) 33.5% 38.0% 0.386 35.3% 38.7% 0.5

Slide 77: Summary of Serious Adverse Events
Summary of Serious Adverse Events No reported deaths due to existing cancers Overall frequency of SAEs was low in the study, given: Length of follow-up General level of poor health Number of healing risk factors (smoking, obesity, and diabetes) No SAEs related to the study device
Slide 78: No Trend in Incidence of Cancer
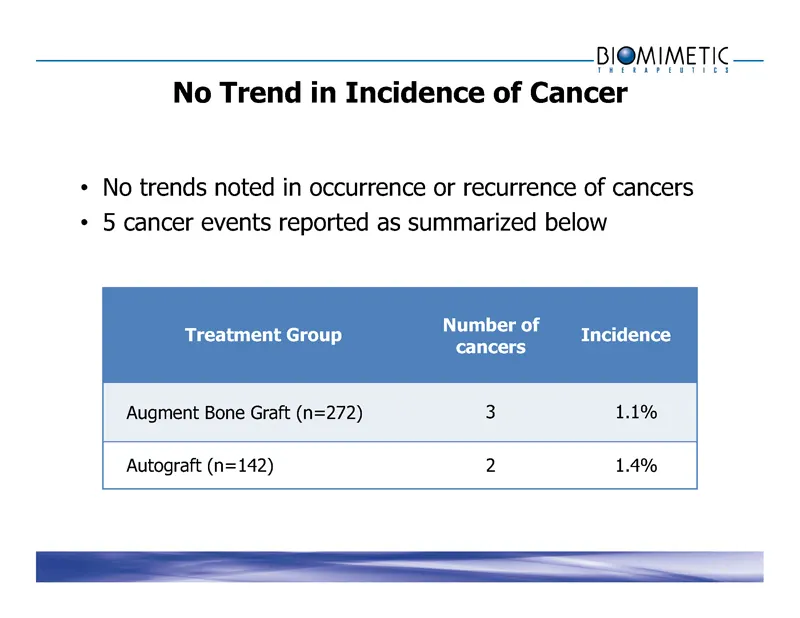
No Trend in Incidence of Cancer No trends noted in occurrence or recurrence of cancers 5 cancer events reported as summarized below Number of Treatment Group Incidence cancers Augment Bone Graft (n=272) 3 1.1% Autograft (n=142) 2 1.4%

Slide 79: Autograft Patients Experience Increased Risk Due to Second Procedure
Autograft Patients Experience Increased Risk Due to Second Invasive Procedure Bone graft harvest risks continue to present a dilemma for orthopedic surgeons Safety benefits also trended in favor of the Augment group Serious treatment emergent adverse events Overall surgical and complication rates Si
Slide 80: Safety Conclusions
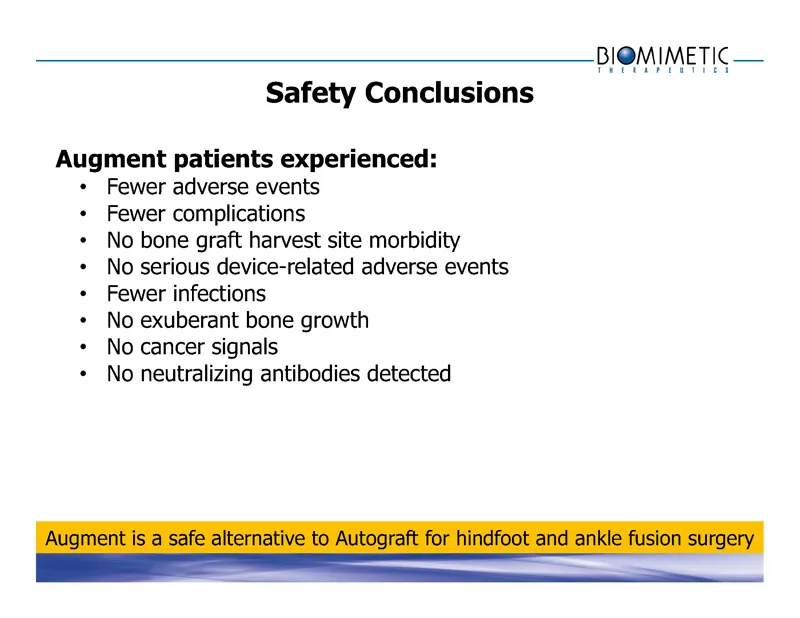
Safety Conclusions Augment patients experienced: Augment is a safe alternative to Autograft for hindfoot and ankle fusion surgery Fewer adverse events Fewer complications No bone graft harvest site morbidity No serious device-related adverse events Fewer infections No exuberant bone growth No cancer

Slide 81: Summary of Benefits
Summary of Benefits www.biomimetics .com
Slide 82: Effectiveness Summary
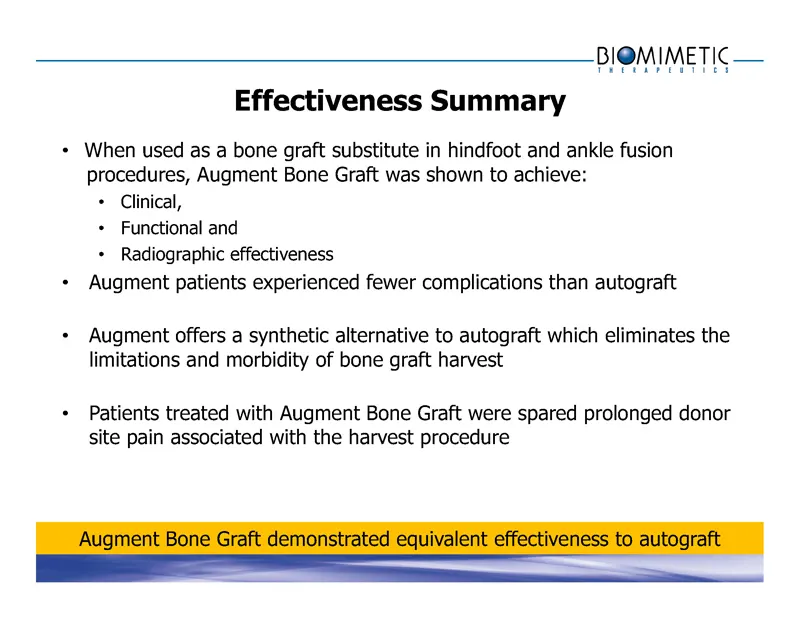
Effectiveness Summary When used as a bone graft substitute in hindfoot and ankle fusion procedures, Augment Bone Graft was shown to achieve: Clinical, Functional and Radiographic effectiveness Augment patients experienced fewer complications than autograft Augment offers a synthetic alternative to a
Slide 83: Safety Summary
Safety Summary Augment offers an alternative for hindfoot and ankle fusions by: Eliminating the limitations and morbidity associated with use of autogra ft Demonstrating lower complication rates than autograft Sparing patients prolonged donor site pain associated with the autograft harvest procedure
Slide 84: Summary
Summary Augment has been shown to be a safe and effective alternative to autograft Multiple trials, includin g pivotal RCT (Level I evidence ) The benefits of Augment outweigh the potential risks Augment eliminates morbidity associated with autograft Augmen t demonstrated equivalent effectiveness, s

Slide 85: Commercialization and Reimbursement
Commercialization and Reimbursement Hans Kestler Vice President, Orthopedics & Sports Medicine www.biomimetics .com
Slide 86: Augment Stakeholders
Augment Stakeholders Patients Buyers Payers Surgeons

Slide 87: Augment Commercialization Topics
Augment Commercialization Topics Augment Bone Graft Value Proposition Augment Bone Graft Market Opportunity Branding and Positioning Augment Bone Graft The Sales Channel for U.S. Commercialization Sales Training , Tools and Territories Reimbursement
Slide 88: Augment Bone Graft Value Proposition
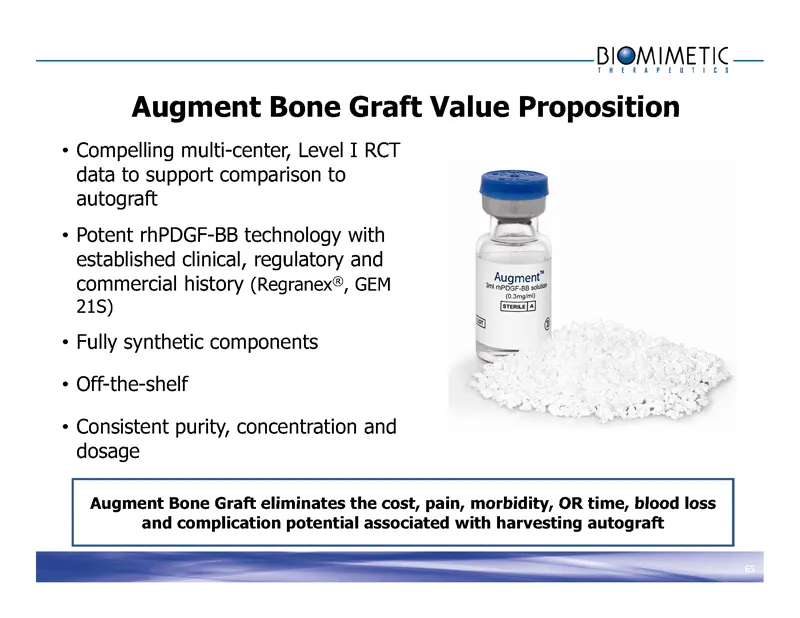
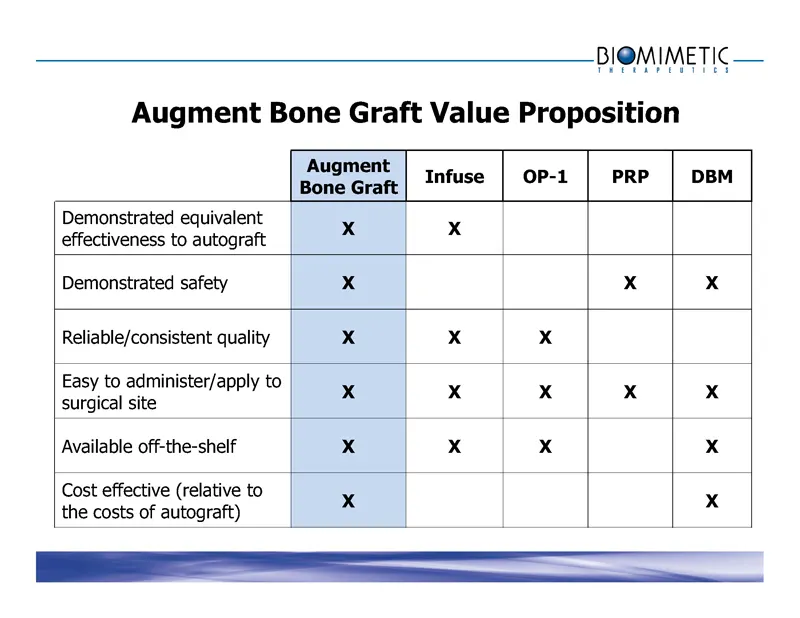
Augment Bone Graft Value Proposition Augment Bone Graft eliminates the cost, pain, morbidity, OR time, blood loss and complication potential associated with harvesting autograft Compelling multi-center, Level I RCT data to support comparison to autograft Potent rhPDGF -BB technology with established
Slide 89: Augment Bone Graft Value Proposition
Augment Bone Graft Value Proposition Augment Infuse OP-1 PRP DBM Bone Graft Demonstrated equivalent X X effectiveness to autograft Demonstrated safety X X X Reliable/consistent quality X X X Easy to administer/apply to X X X X X surgical site Available off-the-shelf X X X X Cost effective (relative
Slide 90: Market Opportunity: BG Procedures (2010)
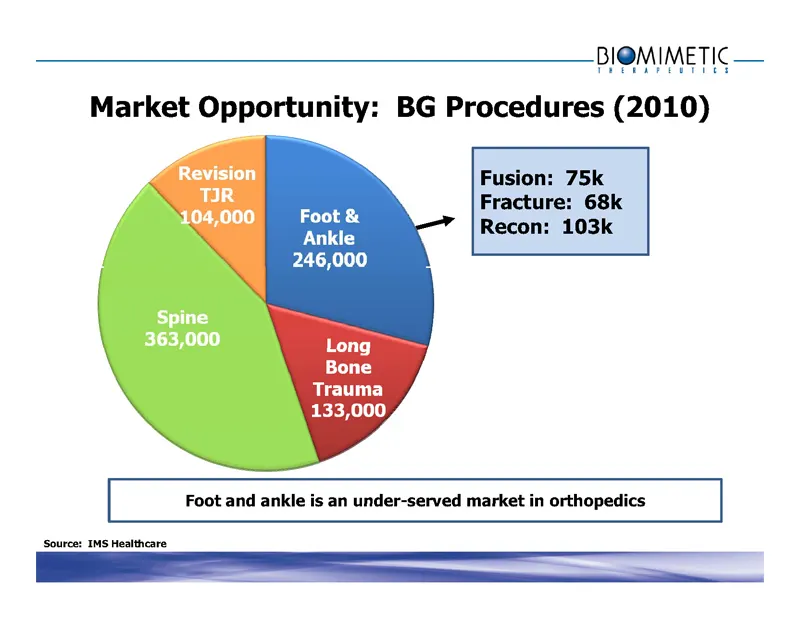
Market Opportunity: BG Procedures (2010) Fusion: 75k Fracture: 68k Recon: 103k Foot and ankle is an under-served market in orthopedics Source: IMS Healthcare

Slide 91: Branding and Positioning
Augment Commercialization Branding and Positioning Contracted with a leading branding agency to develop brandin g and positionin g for Augment platform Will craft a brand charter and creative brief in preparation of Augment launch Results will elucidate the “switching triggers” for the stakeholders
Slide 92: Concentrated Foot & Ankle Procedure Volume Enables Effective Sales Coverage
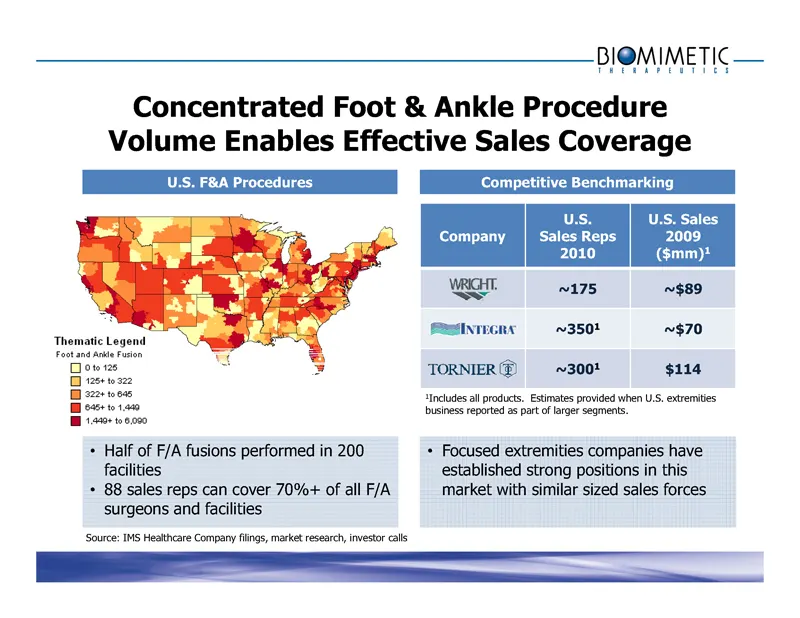
Concentrated Foot & Ankle Procedure Volume Enables Effective Sales Coverage U.S. F&A Procedures Half of F/A fusions performed in 200 facilities 88 sales reps can cover 70%+ of all F/A surgeons and facilities Competitive Benchmarking U.S. U.S. Sales Company Sales Reps 2009 2010 ($mm)1 ~175 ~$89 ~3501
Slide 93: F/A Fusion Volume Distribution
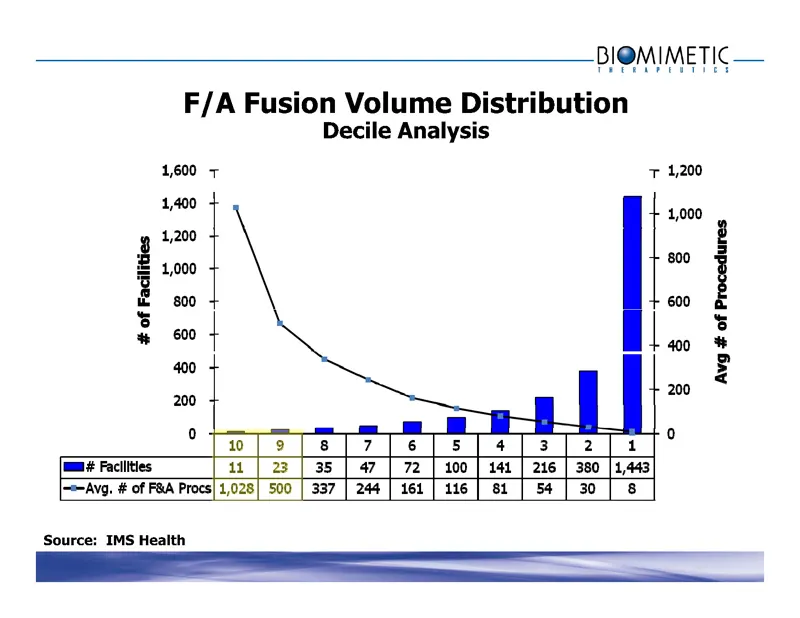
F/A Fusion Volume Distribution Decile Analysis Source: IMS Health
Slide 94: Foot & Ankle Fusion Volume Distribution
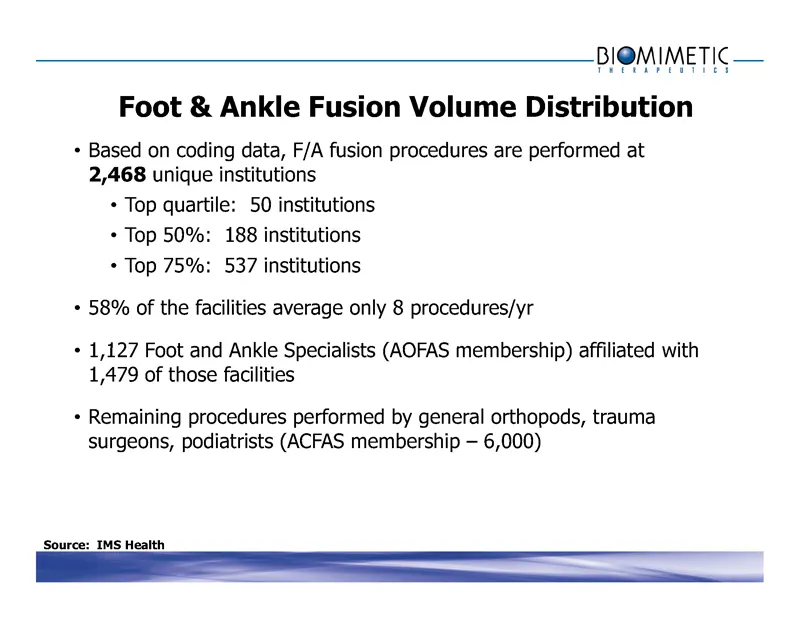
Source: IMS Health Foot & Ankle Fusion Volume Distribution Based on coding data, F/A fusion procedures are performed at 2,468 unique institutions Top quartile: 50 institutions Top 50%: 188 institutions Top 75%: 537 institutions 58% of the facilities average only 8 procedures/yr 1,127 Foot and Ankle
Slide 95: Foot & Ankle Fusion – Top Facilities
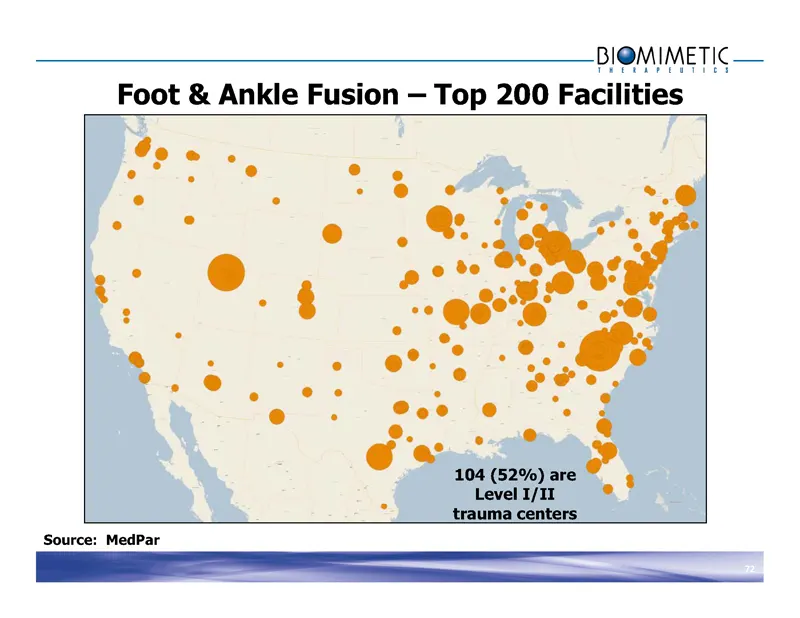
Foot & Ankle Fusion – Top 200 Facilities 104 (52%) are Level I/II trauma centers Source: MedPar
Slide 96: U.S. Sales Channel
Augment Commercialization U.S. Sales Channel Hybrid Model – Mix of Independent Agencies and Direct BMTI Assets At launch: 15-20 BMTI direct assets to include sales, technical and reimbursement support and sales management backstopped by BMTI R&D “experts ” Year 1: Independent sales force of 80-100 l
Slide 97: U.S. Sales Profiles
Augment Commercialization U.S. Sales Profiles Independent Agents Lower extremity trauma/foot and ankle/surgical podiatry focus and relationships Demonstrated track record of sales success Experience with orthobiologics/bone graft substitute products preferred Non competitive product mix Direct Asset

Slide 98: Sales Training and Tools
Augment Commercialization Sales Training and Tools Rigorous sales training in advance of product launch Classroom and systems training, hands-on labs, retention testing, interactions with KOLs Sales kits Published scientific journals , technology brochures , sales and data sheets, competitive intell
Slide 99: Sales Territories
Augment Commercialization Sales Territories Direct – defined as a discrete geography not incorporated into agency area Distributor – contracted geography with overla y support from BMTI Geography is deemed critical to overall Augment positionin g DMA analysis – the cutters! Existing BMTI relationshi
Slide 100: U.S. Reimbursement
Augment Commercialization U.S. Reimbursement Within the context of a series of well-defined hospital inpatient & outpatient procedure codes for hindfoot and ankle fusion, Augment Bone Graft will be incorporated into the overall cost of the procedure, in a similar way that existing bone graft substit
Slide 101: Augment Reimbursement Strategy
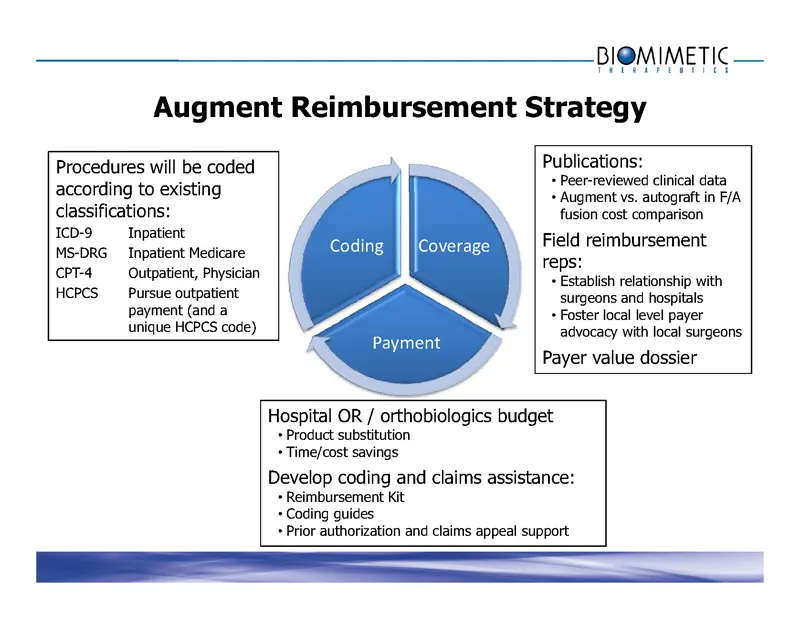
Augment Reimbursement Strategy Procedures will be coded according to existing classifications: ICD-9 Inpatient MS-DRG Inpatient Medicare CPT-4 Outpatient , Physician HCPCS Pursue outpatient payment (and a unique HCPCS code) Coding Coverage Payment Publications: Peer-reviewed clinical data Augmen t v
Slide 102: Foot and Ankle Fusion Inpatient Hospital Procedure Coding
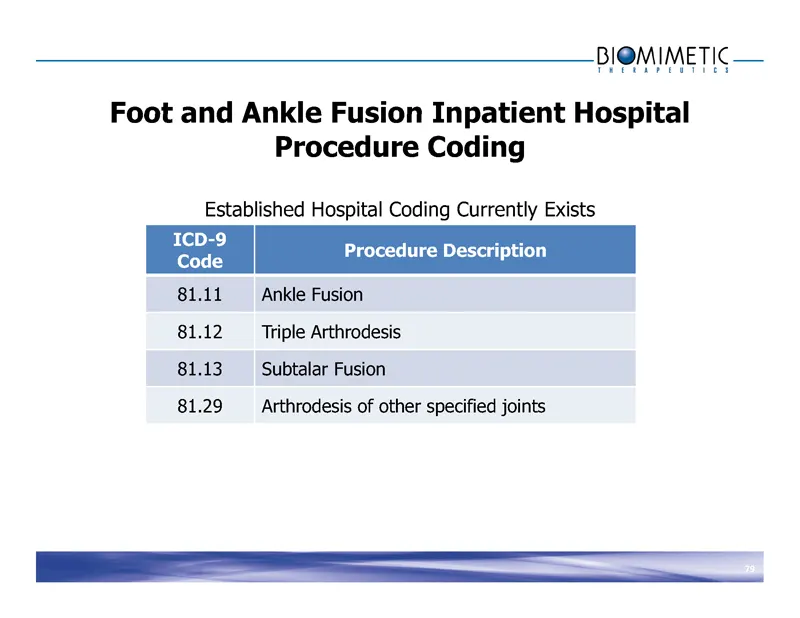
Foot and Ankle Fusion Inpatient Hospital Procedure Coding Established Hospital Coding Currently Exists ICD-9 Procedure Description Code 81.11 Ankle Fusion 81.12 Triple Arthrodesis 81.13 Subtalar Fusion 81.29 Arthrodesis of other specified joints
Slide 103: Typical Medicare Inpatient MS-DRG Assignment
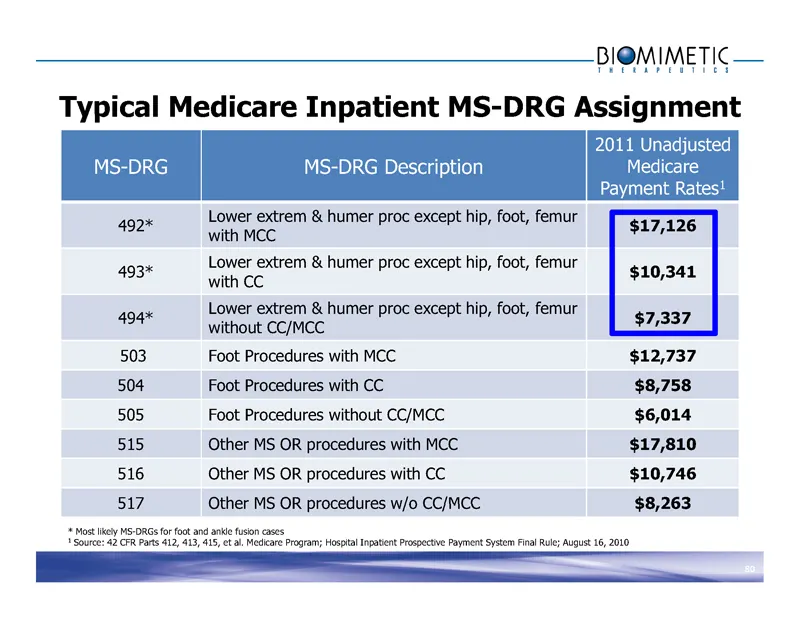
Typical Medicare Inpatient MS-DRG Assignment 2011 Unadjusted MS-DRG MS-DRG Description Medicare Payment Rates1 Lower extrem & humer proc except hip, foot, femur 492* $17,126 with MCC Lower extrem & humer proc except hip, foot, femur 493* $10,341 with CC Lower extrem & humer proc except hip, foot, fe
Slide 104: Medicare CY 2011 Outpatient Hospital and ASC Payment Rates
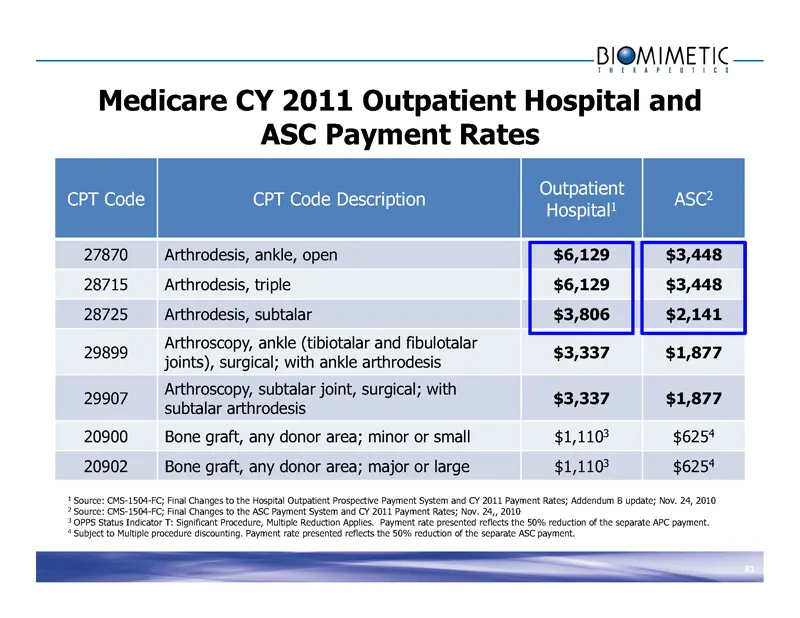
Medicare CY 2011 Outpatient Hospital and ASC Payment Rates Outpatient CPT Code CPT Code Description 1 ASC2 Hospital 27870 Arthrodesis, ankle, open $6,129 $3,448 28715 Arthrodesis, triple $6,129 $3,448 28725 Arthrodesis, subtalar $3,806 $2,141 Arthroscopy, ankle (tibiotalar and fibulotalar 29899 $3,3
Slide 105: Medicare CY 2010 Physician Payment Rates
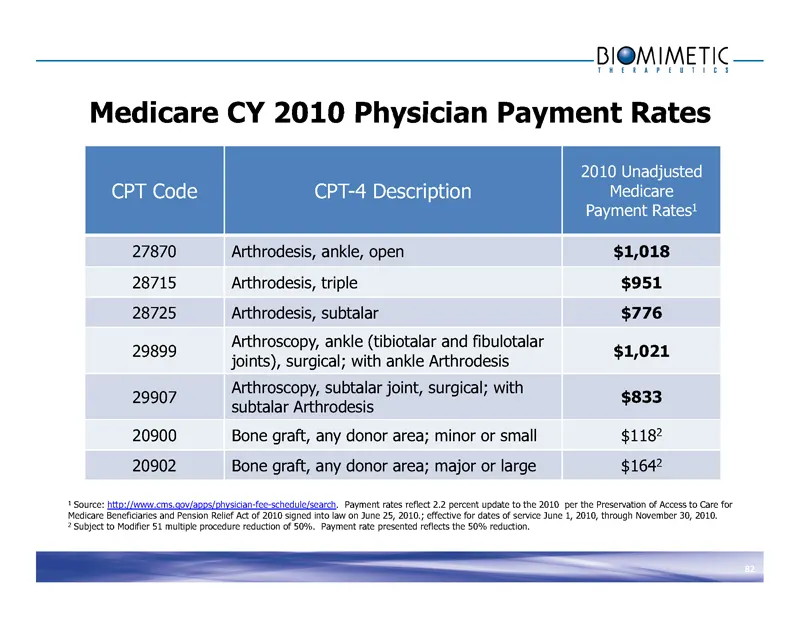
Medicare CY 2010 Physician Payment Rates 2010 Unadjusted CPT Code CPT-4 Description Medicare Payment Rates1 27870 Arthrodesis, ankle, open $1,018 28715 Arthrodesis, triple $951 28725 Arthrodesis, subtalar $776 Arthrosco py, ankle (tibiotalar and fibulotalar 29899 $1,021 joints), surgical; with ankle

Slide 106: Reimbursement Strategy Pre-Approval
Reimbursement Strategy Pre-Approval Develop dossier of evidence to support coverage, paymen t for Augment by Medicare regional administrators and 3rd party payers Establish reimbursement team within BMTI to develop action plans and payer targeted materials (Director of Reimbursement, Erik Harris, on

Slide 107: Reimbursement Strategy Post Approval
Reimbursement Strategy Post Approval KOL-assisted presentations to targeted buying groups Field reimbursement rep call plan with targeted payers Provide assistance to customers for proper coding of procedures with Augmen t, including coding guides and reimbursemen t kits Apply for Medicare inpatient
Slide 108: Reimbursement Tactics
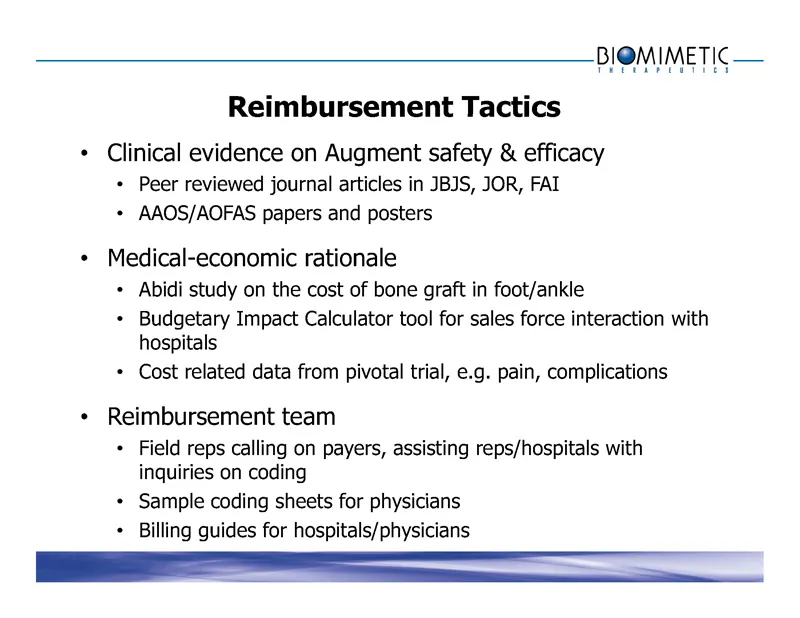
Reimbursement Tactics Clinical evidence on Augment safety & efficacy Peer reviewed journal articles in JBJS, JOR, FAI AAOS/AOFAS papers and posters Medical -economic rationale Abidi study on the cost of bone graft in foot/ankle Budgetary Impact Calculator tool for sales force interaction with hospit

Slide 109: International Commercialization Strategy
International Commercialization Strategy International Sales and Marketing Canada Canadian distribution agreement with Joint Solutions Alliance (JSA) has been changed to logistics agreement – JSA ONLY responsible for shipping and handling National Sales Manager Canada has developed distributor netwo

Slide 110: Milestone Update and Q&A
Milestone Update and Q&A Dr. Sam Lynch President and CEO www.biomimetics .com
Slide 111: Augment Injectable U.S. Pivotal Trial
FDA Approval Granted to Initiate Patient Enrollmen t Enrollment to commence in 1Q Enrollment expected to be complete by YE ‘11 Study Design 201 patients at 25 institutions Randomized 2:1 Augment Injectable to autograft Follow up: six months for effectiveness, 12 months for safety PMA filing with 12

Slide 112: Additional Product Development Activities
Additional Product Development Activities Augment ™ Rotator Cuff Graft Pilot Trial 13 patients treated Enrollment of 30 patients complete by end of 3Q ’11 Interim data release in 1H ’12 EU Regulatory Status Three letters received re-classifying GEM 21S®, Augment and Augment Injectable as devices Aug

Slide 113: Q&A
Q&A
Source: SEC EDGAR · 8-K filed Feb 23, 2011
More decks from Biomimetic Therapeutics Inc
 31st Annual J.P. Morgan Healthcare Conference 201341 slides · Jan 8, 2013
 Technical Presentation (June 2012)26 slides · Jun 21, 2012
 Jefferies Global Healthcare Conference 201136 slides · Jun 10, 2011
 2010 AOFAS Annual Summer Meeting19 slides · Jul 7, 2010
 Technical Presentation (July 2010)19 slides · Jul 7, 2010
 Technical Presentation (March 2010)25 slides · Mar 12, 2010