Repros Therapeutics — Investor Presentation (February 2014)
37 slides from Repros Therapeutics's investor presentation, Feb 10, 2014

Slide 1: Developing clinical stage small molecule therapeutics for hormonal and reproductive disorders
Developing clinical stage small molecule therapeutics to treat hormonal and reproductive system disorders

Slide 2: Repros Disclaimer
Repros Disclaimer Any statements made by the Company that are not historical facts contained in these slides (or in any oral accompanying discussion) are forward - looking statements within the meaning of the Private Securities Litigation Reform Act of 1995 and are subject to various risks, uncertai

Slide 3: Investment Highlights for 2014
Investment Highlights for 2014 Significant Value Creating Events for Androxal , An Oral Treatment for Low T Androxal Restores the Body’s ability to Produce Its Own Testosterone • Androxal ® 2014 Milestones – Complete all clinical studies – Complete head - to - head studies of Androxal versus Androge

Slide 4: Testosterone Market and Androxal Overview
Testosterone Market and Androxal Overview • US market for low testosterone exceeds $1.5 billion • Only approved non invasive therapies are hormone replacements • Repros believes 85% of hypogonadal men experience low T due to an endocrine disorder – These men have functional but un - stimulated teste
Slide 5: Who are the men using testosterone?
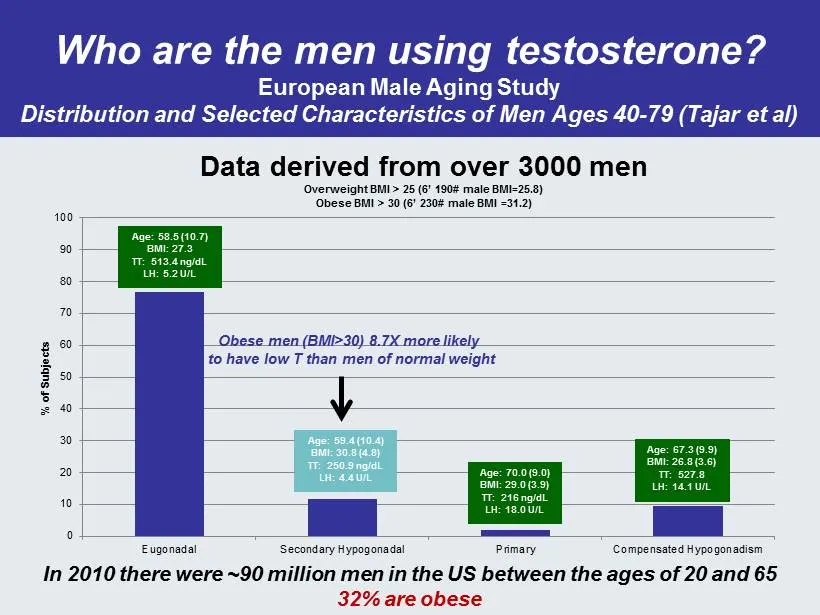
Who are the men using testosterone? European Male Aging Study Distribution and Selected Characteristics of Men Ages 40 - 79 ( Tajar et al) 0 10 20 30 40 50 60 70 80 90 100 Eugonadal Secondary Hypogonadal Primary Compensated Hypogonadism % of Subjects Age: 58.5 (10.7) BMI: 27.3 TT: 513.4 ng / dL LH:

Slide 6: 2014 Androxal Regulatory Events
2014 Androxal Regulatory Events • Feb. 5, 2014: Face to Face meeting to discuss completed efficacy studies and new head to head trials • Q2 ’14: Pre - NDA Meeting • Q4 ‘14: Submit NDA

Slide 7: February 5, 2014 FDA Meeting
February 5, 2014 FDA Meeting • Efficacy Discussion – FDA notes efficacy of Androxal must support risk benefit assessment • Repros believes head to head studies only way to show clinical need • FDA asked for justification of WHO lower bound of 15 million sperm/mL as comparison threshold • Safety and

Slide 8: Head to Head Studies Comparing Androxal to Androgel 1.62
Head to Head Studies Comparing Androxal to Androgel 1.62 • ZA - 304 & ZA - 305: Two identical studies not under SPA – 3 arm parallel design with 40 subjects per arm – 23 US clinical sites – Primary endpoint comparison of Androxal and Androgel with respect to normalizing both T and sperm counts in se

Slide 9: ZA-304 & ZA-305 Powering Assumptions
ZA - 304 & ZA - 305 Powering Assumptions • Superiority to Androgel in Normalizing T (300 - 1040 ng/ dL ) While Preserving Sperm Concentration (>15x10 6 ) (confirming sperm endpoint with FDA) – 70% Androxal responders • Yields p<0.001 @ Androgel 30% response • Yields p<0.01 @ Androgel 40% response –
Slide 10: Head to Head Comparison of Androxal to Testim and Placebo, Study ZA-203
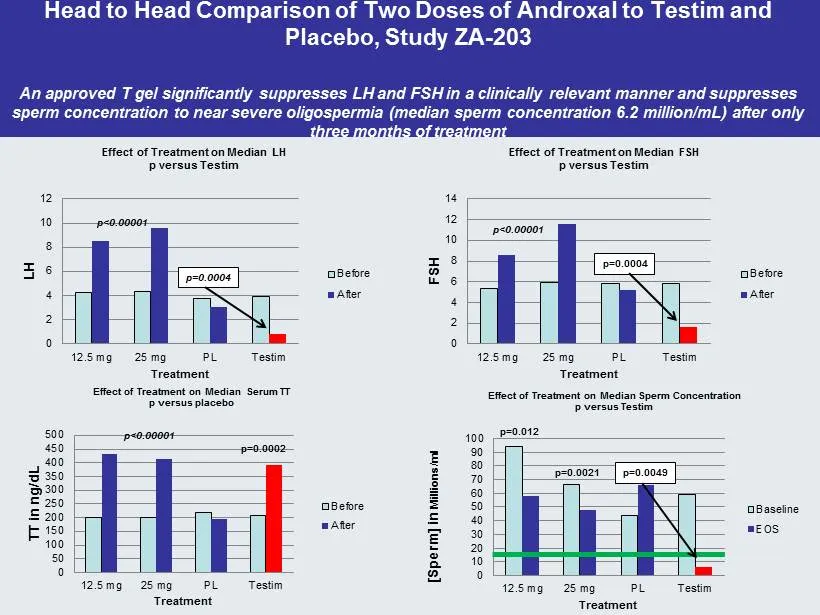
Head to Head Comparison of Two Doses of Androxal to Testim and Placebo, Study ZA - 203 An approved T gel significantly suppresses LH and FSH in a clinically relevant manner and suppresses sperm concentration to near severe oligospermia (median sperm concentration 6.2 million/mL) after only three mon
Slide 11: Androxal Safety
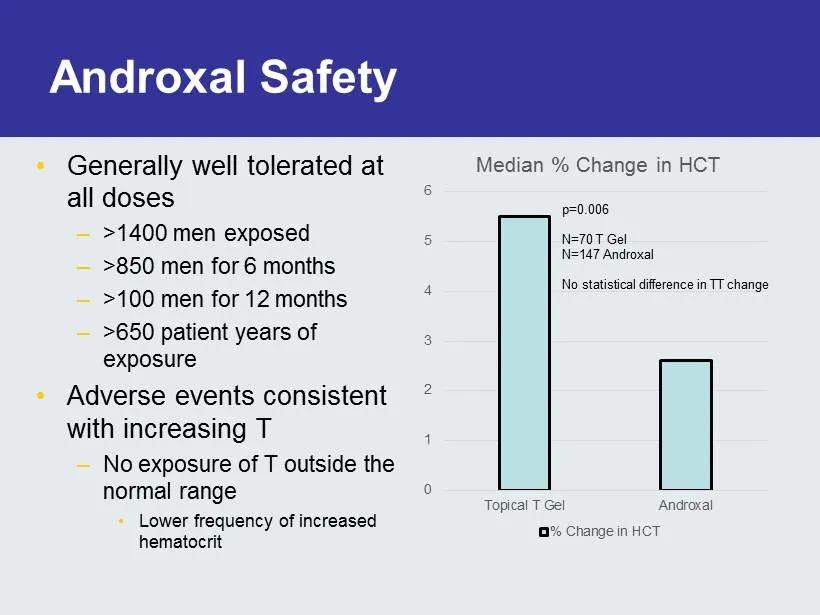
Androxal Safety • Generally well tolerated at all doses – >1400 men exposed – >850 men for 6 months – >100 men for 12 months – >650 patient years of exposure • Adverse events consistent with increasing T – No exposure of T outside the normal range • Lower frequency of increased hematocrit 0 1 2 3 4

Slide 12: Excursions Above the Normal Range for T Lead to Increasing Hematocrit
Excursions Above the Normal Range for T Leads to Increasing Hematocrit with T Replacement “Exogenous testosterone (TT) is associated with physiologic changes that predispose to clotting and thrombotic disorders including increased blood pressure [18], polycythemia [19], reductions in HDL cholesterol
Slide 13: 24-Hour Assessment Androgel 1%
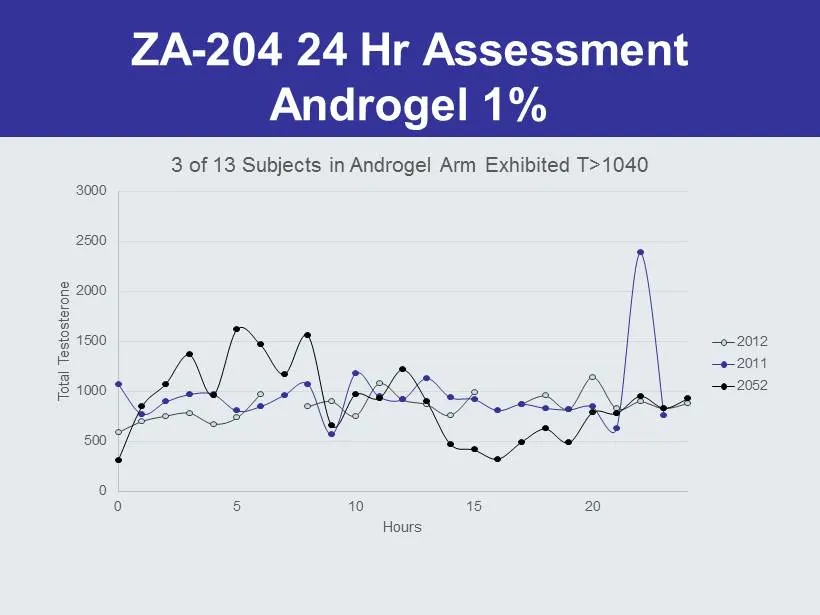
ZA - 204 24 Hr Assessment Androgel 1% 0 500 1000 1500 2000 2500 3000 0 5 10 15 20 Total Testosterone Hours 3 of 13 Subjects in Androgel Arm Exhibited T>1040 2012 2011 2052
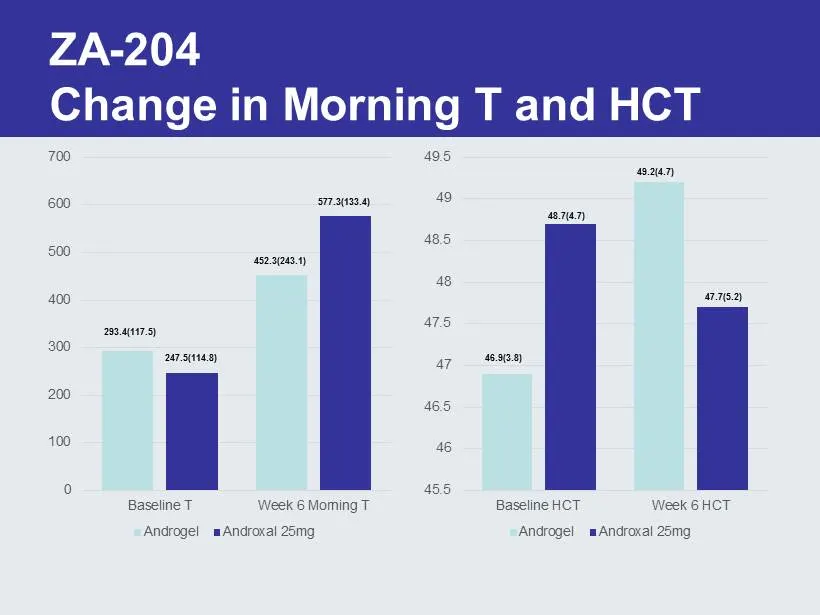
Slide 14: Change in Morning T and HCT
ZA - 204 Change in Morning T and HCT 0 100 200 300 400 500 600 700 Baseline T Week 6 Morning T Androgel Androxal 25mg 45.5 46 46.5 47 47.5 48 48.5 49 49.5 Baseline HCT Week 6 HCT Androgel Androxal 25mg 293.4(117.5) 247.5(114.8) 452.3(243.1) 577.3(133.4) 46.9(3.8) 48.7(4.7) 49.2(4.7) 47.7(5.2)

Slide 15: Study Design and Subjects
ZA - 300 Study • 499 Subjects randomized – Baseline Morning T < 300 – 23.5% Type II Diabetes – 30.6% taking c holesterol medication – 33.3% previous T exposure • 6 months of treatment • 2 months of follow - up post treatment • 393 Subjects (78.8%) completed study – 23 (4.6%) Withdrew due to an Adver
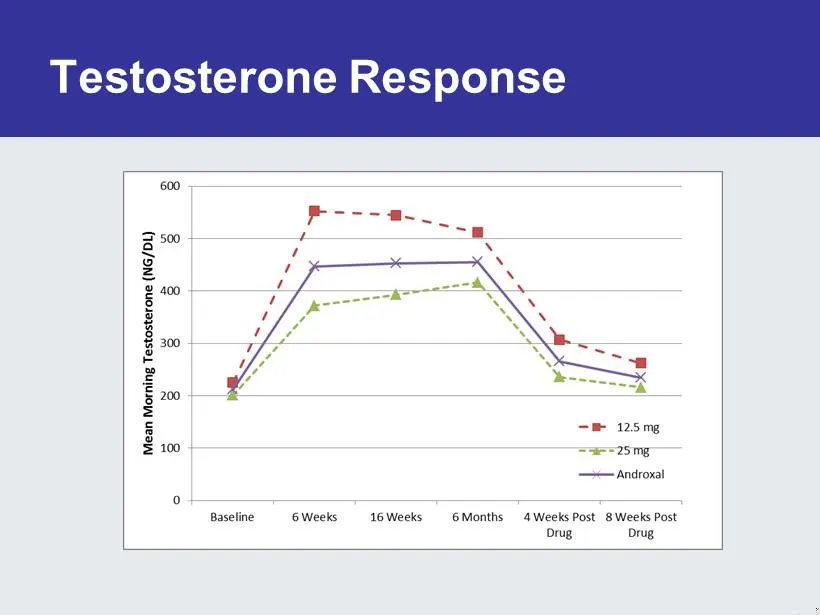
Slide 16: Testosterone Response
Testosterone Response g Mean Morning Testosterone (NG/DL) 3 8 Baseline Weeks. 16Weeks~—- G Months 4 Weeks Post. 8 Weeks Post Drug Drug
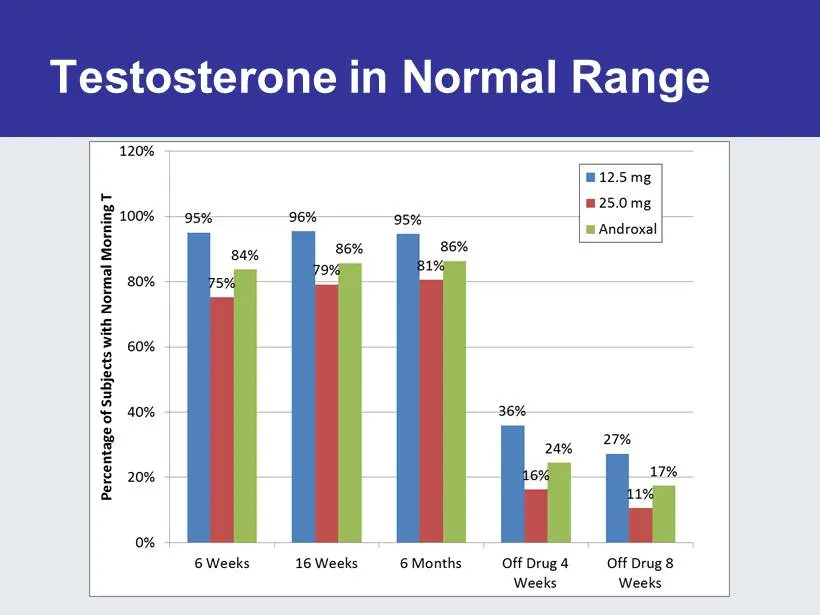
Slide 17: Testosterone in Normal Range
Testosterone in Normal Range

Slide 18: Additional Findings after Months of Treatment
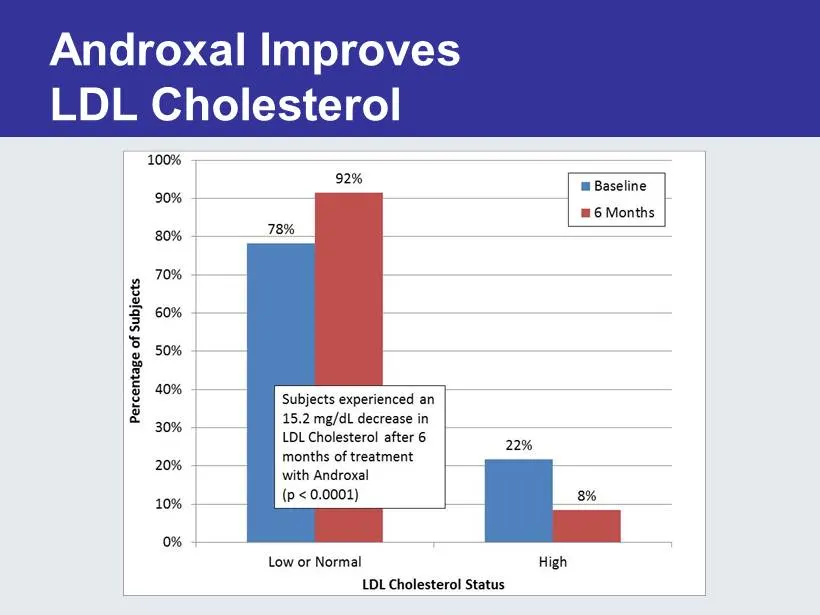
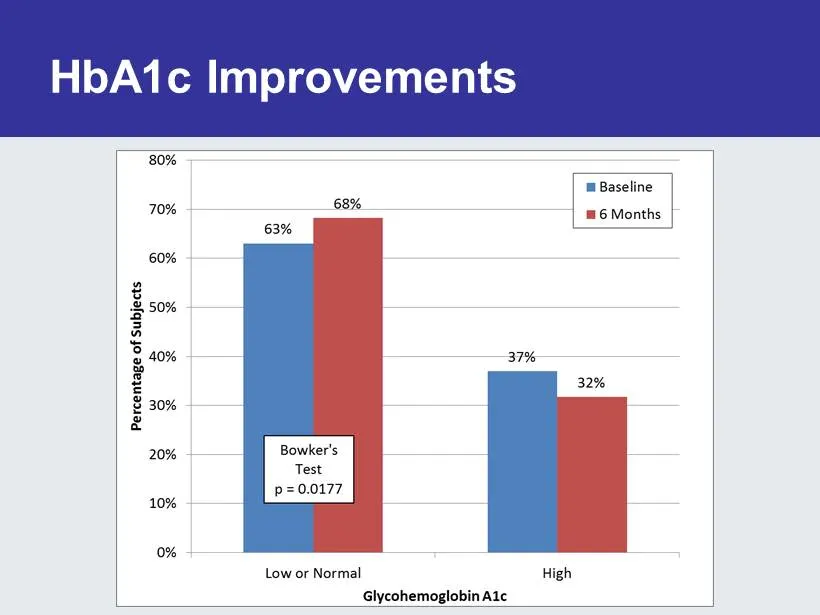
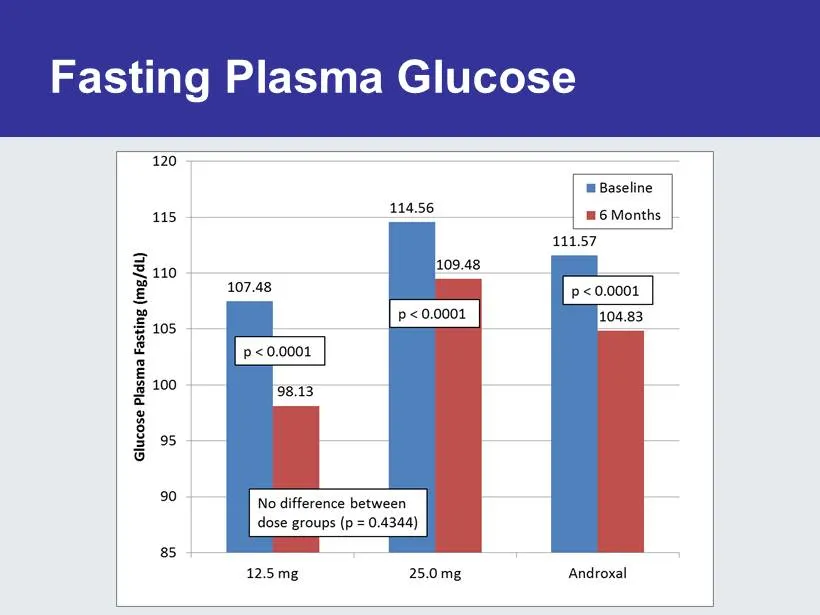
ZA - 300 Additional Findings after 6 months of treatment • Androxal improves symptoms of metabolic syndrome – Androxal reduces total cholesterol and improves HDL/LDL ratio – Androxal reduces fasting plasma glucose levels – Androxal shifts A1c into normal range in a statistically significant manner •
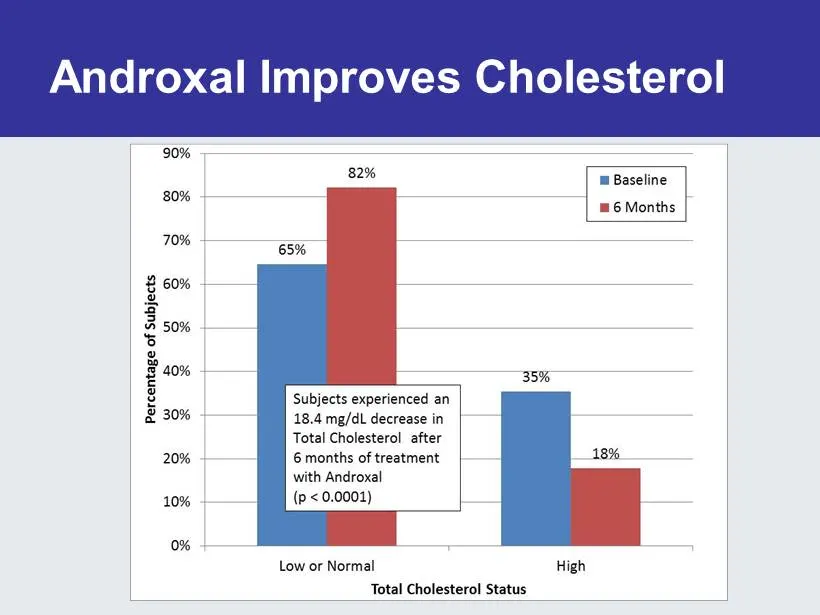
Slide 19: Androxal Improves Cholesterol
Androxal Improves Cholesterol
Slide 20: Androxal Improves LDL Cholesterol
Androxal Improves LDL Cholesterol
Slide 21: A1c Improvements
c Improvements 80% 70% 60% 50% Percentage of Subjects 8 8 R zz 68% 63% Bowker's Test p=0.0177 Low or Normal Baseline 6 Months 32% High Glycohemoglobin A1c
Slide 22: Fasting Plasma Glucose
Fasting Plasma Glucose 120 Bas ine 114.56 115 6 Months 111.57 110 p< 0.0001 104.83 p< 0.0001 105 p< 0.0001 100 Glucose Plasma Fasting (mg/dL) 95 80 No difference between dose groups (p = 0.4344) 85 12.5mg 25.0mg Androxal
Slide 23: Influence of Prior Testosterone
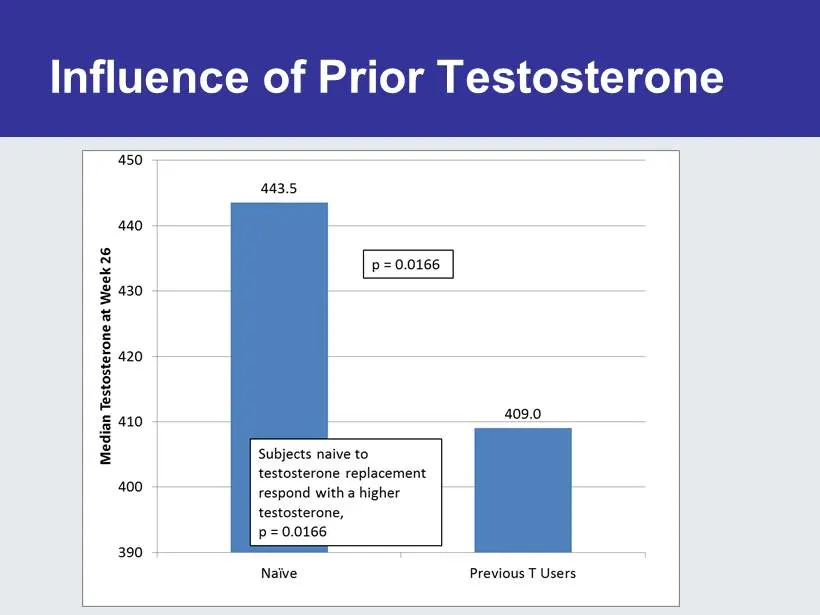
Influence of Prior Testosterone

Slide 24: ZA-300: Safety
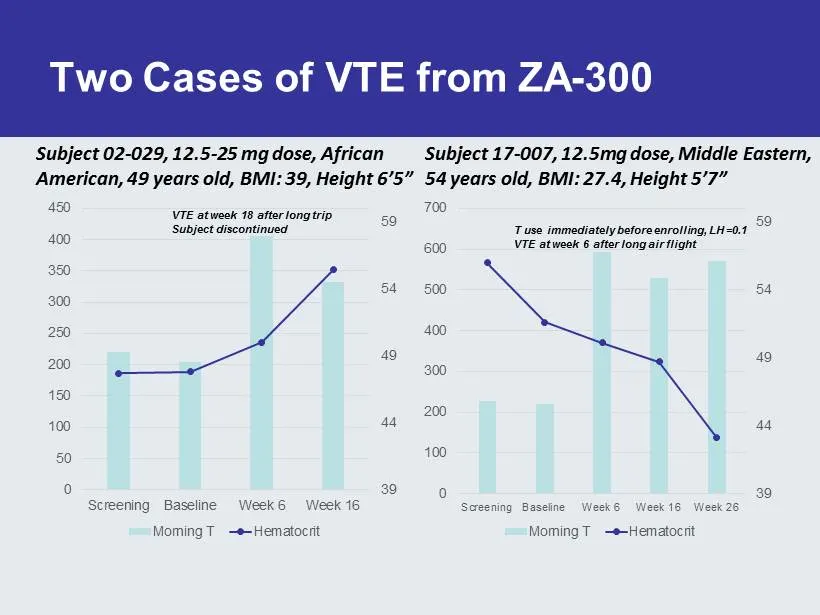
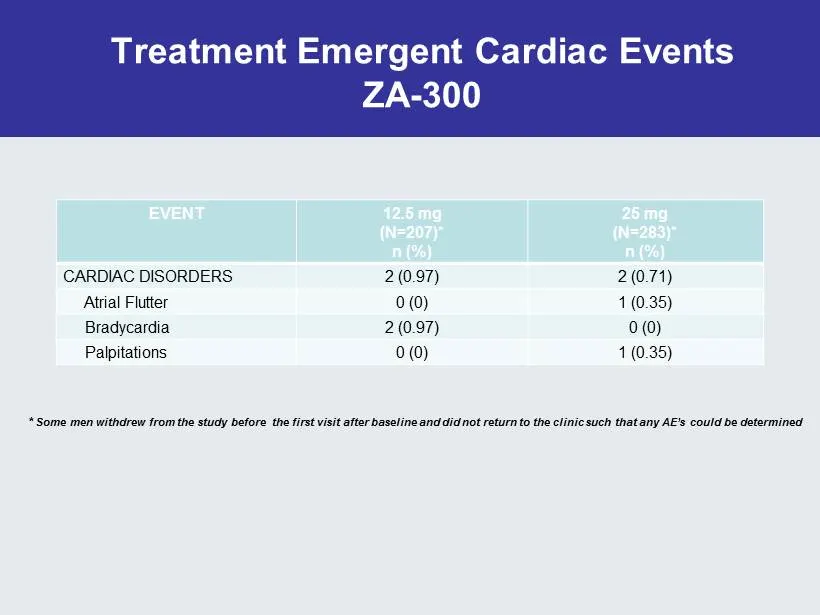
ZA - 300: Safety • 499 subjects treated with Androxal – For up to 26 weeks • No new safety issues identified – No deaths – No significant cardiovascular findings – No significant eye findings • Venous Thromboembolism – One case with deep vein thrombosis (DVT) and pulmonary emboli (PE), multiple risk
Slide 25: Two Cases of VTE
Two Cases of VTE from ZA - 300 39 44 49 54 59 0 50 100 150 200 250 300 350 400 450 Screening Baseline Week 6 Week 16 Morning T Hematocrit 39 44 49 54 59 0 100 200 300 400 500 600 700 Screening Baseline Week 6 Week 16 Week 26 Morning T Hematocrit Subject 02 - 029, 12.5 - 25 mg dose, African American,
Slide 26: Treatment Emergent Cardiac Events
Treatment Emergent Cardiac Events ZA - 300 EVENT 12.5 mg (N=207)* n (%) 25 mg (N=283)* n (%) CARDIAC DISORDERS 2 (0.97) 2 (0.71) Atrial Flutter 0 (0) 1 (0.35) Bradycardia 2 (0.97) 0 (0) Palpitations 0 (0) 1 (0.35) * Some men withdrew from the study before the first visit after baseline and did not r
Slide 27: Diastolic Blood Pressure
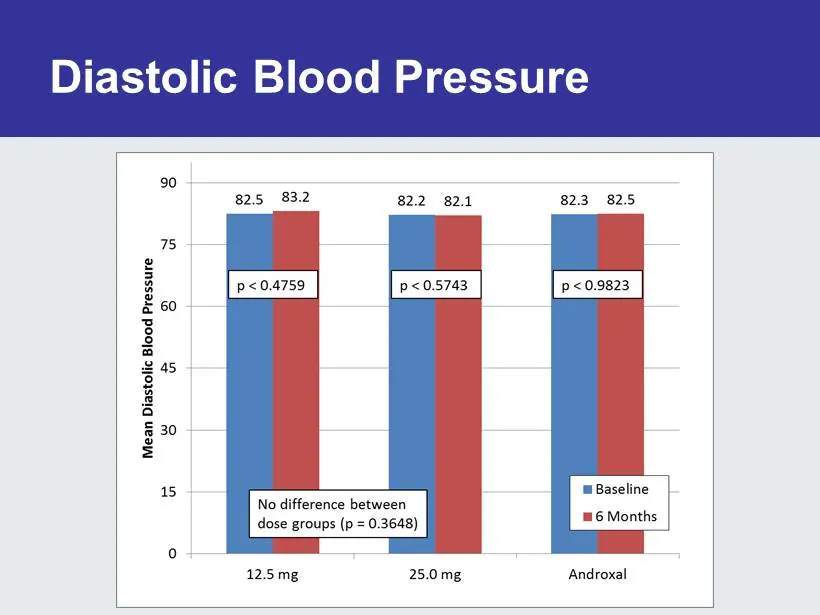
Diastolic Blood Pressure 90 82.5 83.2 82.2 82.1 82.3 82.5 75 2 5 FA p< 0.4759 p<0.9823 £60 3 Hy 8 a mBaseline | 6 Months 15 No difference between dose groups (p 12.5 mg 25.0mg Androxal

Slide 28: Androxal Exhibits Unique Profile vs Approved Hormone Replacement
Androxal Exhibits Unique Profile with Numerous Advantages vs Approved Hormone Replacement • The Androxal Advantages – Oral – Not controlled substance, cannot be abused – Less CV risk than T’s??? • No supernormal levels of T achieved – No transference risk – Restores normal function (no loss of testi

Slide 29: Commercial Goals for Androxal
Commercial Goals for Androxal • Low T market already at primary care, 75% of written scripts • Specialists readily reached by Repros initiative – Quintiles assessment full year 1 sales = $120 million using small sales force (n=41) – Cash - flow positive during the first year of launch – Androxal is

Slide 30: Proellex for Uterine Fibroids and Endometriosis
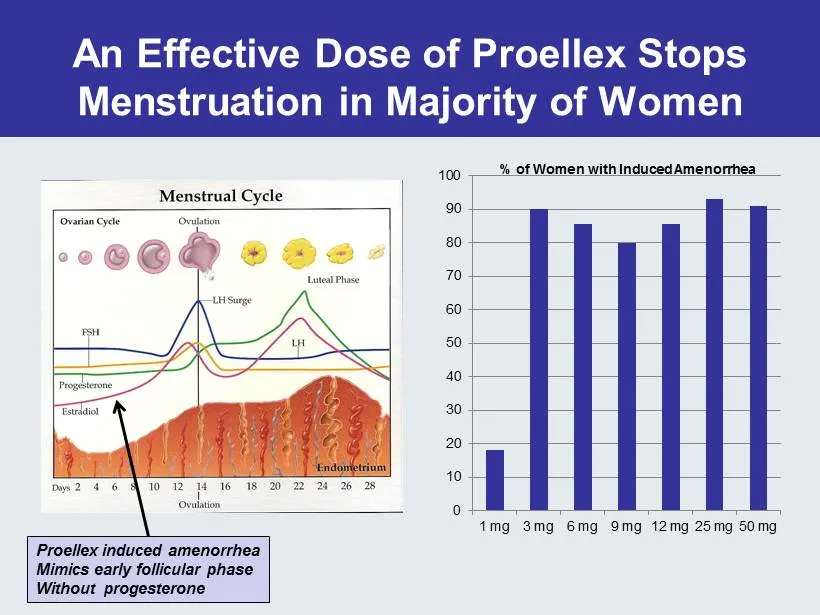
Proellex for the Treatment of Uterine Fibroids and Endometriosis • Over 30 million women of reproductive age in the US afflicted with symptomatic uterine fibroids or endometriosis • Over 300,000 hysterectomies performed every year in the US to treat these two disorders • No acceptable chronic therap
Slide 31: An Effective Dose of Proellex Stops Menstruation in Majority of Women
An Effective Dose of Proellex Stops Menstruation in Majority of Women 0 10 20 30 40 50 60 70 80 90 100 1 mg 3 mg 6 mg 9 mg 12 mg 25 mg 50 mg % of Women with Induced Amenorrhea Proellex induced amenorrhea Mimics early follicular phase Without progesterone
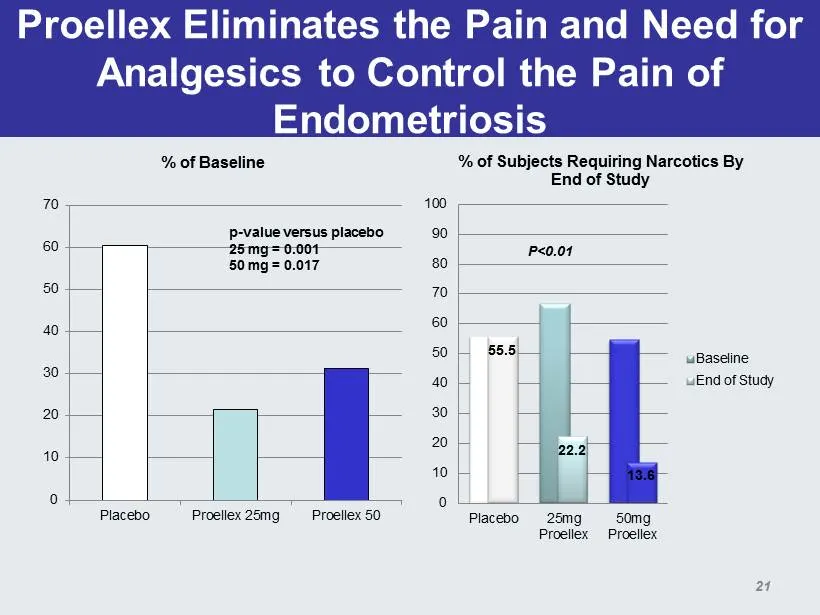
Slide 32: Proellex Eliminates Endometriosis Pain and Need for Analgesics
Proellex Eliminates the Pain and Need for Analgesics to Control the Pain of Endometriosis 0 10 20 30 40 50 60 70 Placebo Proellex 25mg Proellex 50 % of Baseline p - value versus placebo 25 mg = 0.001 50 mg = 0.017 55.5 22.2 13.6 0 10 20 30 40 50 60 70 80 90 100 Placebo 25mg Proellex 50mg Proellex %
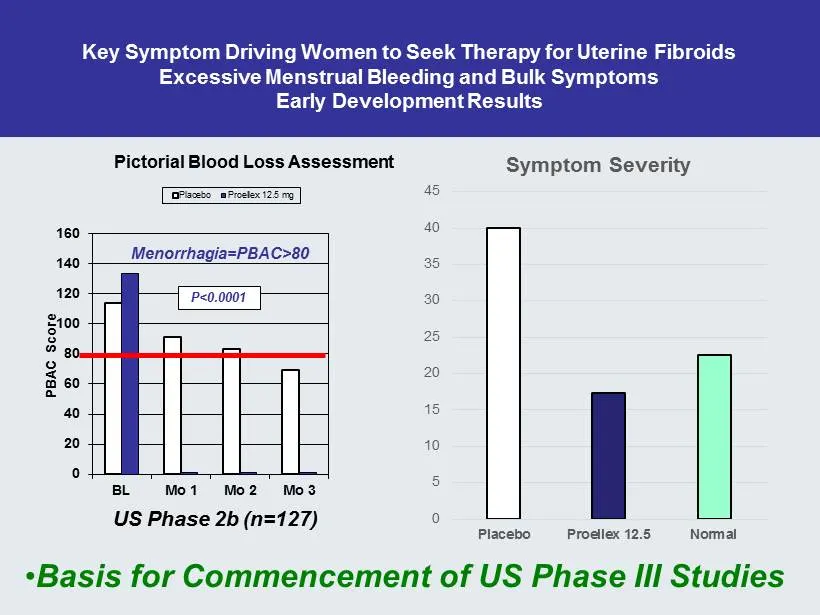
Slide 33: Key Symptom Driving Women to Seek Therapy for Uterine Fibroids
Key Symptom Driving Women to Seek Therapy for Uterine Fibroids Excessive Menstrual Bleeding and Bulk Symptoms Early Development Results 0 20 40 60 80 100 120 140 160 BL Mo 1 Mo 2 Mo 3 PBAC Score Pictorial Blood Loss Assessment Placebo Proellex 12.5 mg P<0.0001 0 5 10 15 20 25 30 35 40 45 Placebo Pro
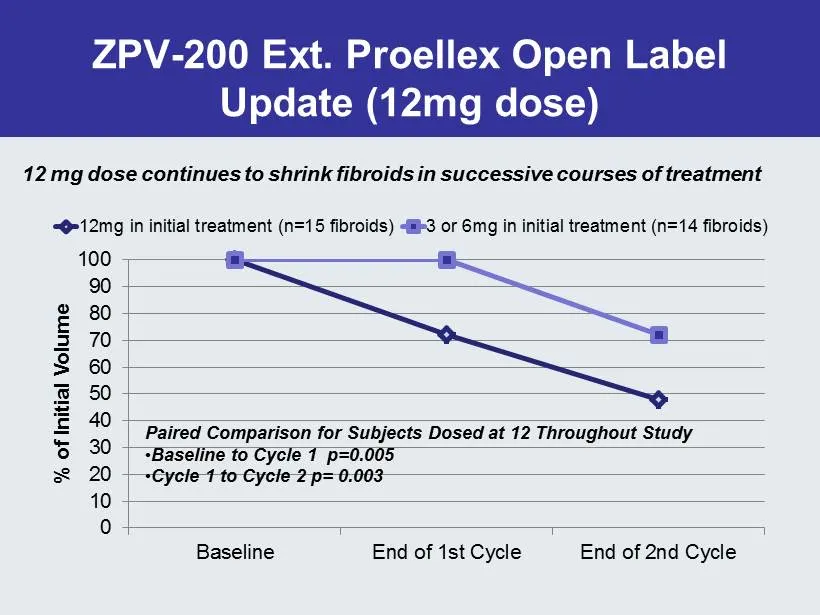
Slide 34: Proellex Open Label Update (12mg dose)
ZPV - 200 Ext. Proellex Open Label Update (12mg dose) 0 10 20 30 40 50 60 70 80 90 100 Baseline End of 1st Cycle End of 2nd Cycle % of Initial Volume 12mg in initial treatment (n=15 fibroids) 3 or 6mg in initial treatment (n=14 fibroids) Paired Comparison for Subjects Dosed at 12 Throughout Study •

Slide 35: Proellex Program Status
Proellex Program Status • All Pre - clinical Studies Complete • 60 Subject Phase 2 Low Dose Oral Endometriosis Study Enrolling – Adding foreign sites – Expect full enrollment in the second half of 2014 • 90 Subject Phase 2 Low Dose Oral Fibroid Study to be Submitted to FDA Q - 1, 2014 – Requires lif

Slide 36: Proellex Clinical Goals
Proellex Clinical Goals • Enter Phase 3 • Uterine Fibroids: 2015 • Endometriosis: Late 2015

Slide 37: Financial Summary
Financial Summary • Cash and equivalents (as of 1/1/14, unaudited) $75.8 M • Cash runway: Through 2016* – Anticipate Androxal approved and launched • Current shares outstanding: 23.0 M shares – Warrants Outstanding – Series A – 877,137 (purchased in unit deal @ $2.45); Series B – 810,109 @ $2.49 exe
Source: SEC EDGAR · 8-K filed Feb 10, 2014
More decks from Repros Therapeutics
 Investor Presentation (September 2017)16 slides · Sep 11, 2017
 Investor Presentation (May 2017)16 slides · May 17, 2017
 Investor Presentation (May 2017)16 slides · May 2, 2017
 Investor Presentation (November 2016)37 slides · Nov 15, 2016
 Investor Presentation (September 2016)26 slides · Sep 12, 2016
 Investor Presentation (August 2016)34 slides · Aug 18, 2016