Blueprint Medicines — Investor Day (November 2019)
127 slides from Blueprint Medicines's investor day presentation, Nov 5, 2019

Slide 1: Blueprint Medicines
M © 2019 Blueprint Medicines Corporation

Slide 2: Welcome - Jeff Albers, Chief Executive Officer
w e l c o m e JEFF ALBERS Chief Executive Officer

Slide 3: Forward-looking statements
F69>(9+-366205. :;(;,4,5;: #/0: 79,:,5;(;065 *65;(05: -69>(9+-366205. :;(;,4,5;: (: +,-05,+ 05 ;/, P90=(;, ",*<90;0,: L0;0.(;065 !,-694 A*; 6-1995, (: (4,5+,+. #/, >69+: B4(@,C B>033,C B*6<3+,C B>6<3+,C B:/6<3+,C B,?7,*;,C B73(5,C B(5;0*07(;,,C B05;,5+,C B),30,=,,C B,:;04(;,,C B79,+0*;,C B7961,*;,C
Slide 4: Our core mission and foundational principles
Our core mission and foundational principles Blueprint Medicines aims to deliver on the promise of precision medicine to improve and extend the lives of patients with cancer and rare diseases. HIGHLY SELECTIVE INHIBITORS PATIENT SELECTION ADAPTIVE ABILITY 4
Slide 5: Our core mission and foundational principles
Our core mission and foundational principles Blueprint Medicines aims to deliver on the promise of precision medicine to improve and extend the lives of patients with cancer and rare diseases. TRANSFORMATIVE BENEFIT Life-changing outcomes for patients URGENCY EFFICIENCY Expedited development and reg
Slide 6: Expedited development of avapritinib and pralsetinib
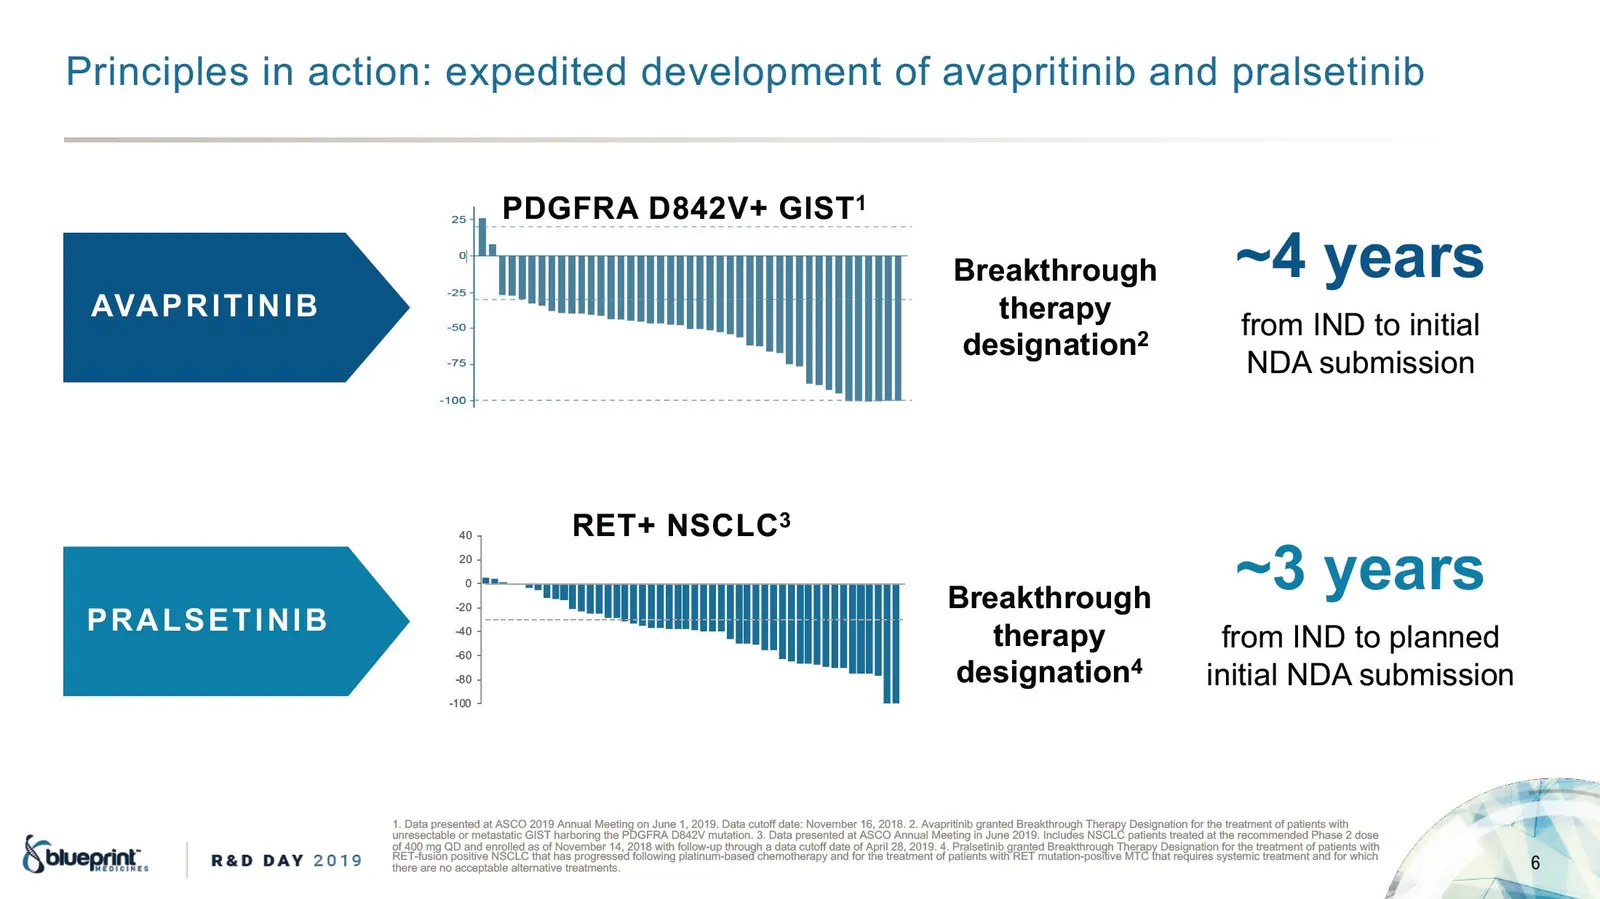
P1)-#)/+%2 )-!#3).-: %7/%$)3%$ $%5%+./,%-3 .& !5!/1)3)-)" !-$ /1!+2%3)-)" PDGFRA D842V+ GIST1 &4 %ea!" &1., IND 3. )-)3)!+ NDA 24",)22).-B!eak#h!o$gh AVAPRITINIB #he!a % de"igna#ion2 RET+ NSCLC3 40 &3 %ea!" &1., IND 3. /+!--%$ )-)3)!+ NDA 24",)22).-20 0 B!eak#h!o$gh -20 PRALSETINIB #he!a % -40 -60 d
Slide 7: The rapid evolution of Blueprint Medicines
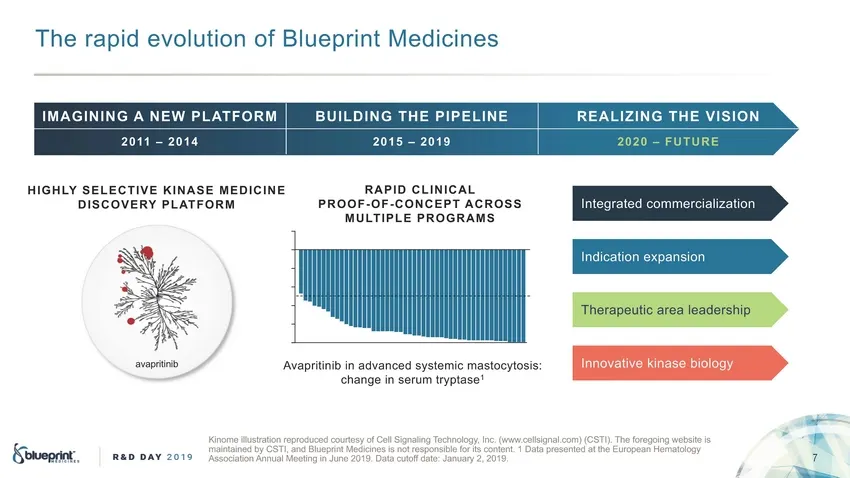
The &a%id e*$!)(i$# $f B!)e%&i#( Medici#e' IMAGINING A NEW PL ATFORM BUILD ING THE PIPELINE R EALIZING THE VISI ON 2011 2014 2015 2019 2020 F UTURE RAPI D C LI NI CAL PRO O F -O F-CO NCEPT ACRO SS MU LT IPLE PR OGR A M S HIGH LY SELECTIVE KI NASE MEDI CI NE DISCOVERY PL ATFORM I#(eg&a(ed c$""e&cia!i
Slide 8: Our focus today: three key themes
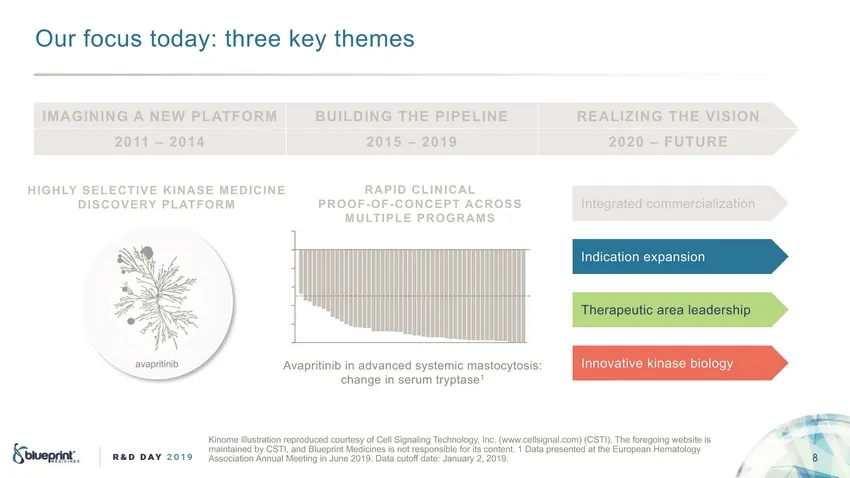
O*' f%c*( )%da.: )h'ee !e. )he#e( RAPI D C LI NI CAL PRO O F -O F-CO NCEPT ACRO SS MU LT IPLE PR OGR A M S HIGH LY SELECTIVE KI NASE MEDI CI NE DISCOVERY PL ATFORM I$)eg'a)ed c%##e'c a" /a) %$ I$d ca) %$ e-&a$( %$ The'a&e*) c a'ea "eade'(h & I$$%+a) +e ! $a(e b %"%g. a+a&' ) $ b A+a&' ) $ b $ ad+a$c
Slide 9: Transform precision therapies and expand to additional patient populations
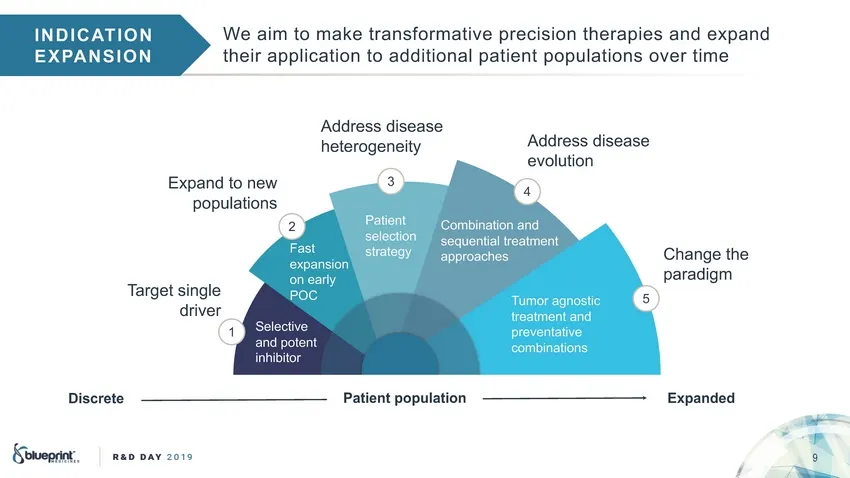
We aim "o make " an!fo ma"i$e p eci!ion "he apie! and e&pand "hei applica"ion "o addi"ional pa"ien" pop#la"ion! o$e "ime INDIC ATION EX PANSION Add e!! di!ea!e Add e!! di!ea!e e$ol#"ion 4 he"e ogenei"' E&pand "o ne% pop#la"ion! 3 Pa"ien" !elec"ion Combina"ion and !eq#en"ial " ea"men" 2 Fa!" e&pan!io
Slide 10: Indication expansion: next-generation KIT inhibitor for mast cell disorders
We aim to make transformative precision therapies and expand their application to additional patient populations over time INDIC ATION EX PANSION A next-generation KIT inhibitor for mast cell disorders 10
Slide 11: Cornerstone precision therapy enables reinvestment of insights
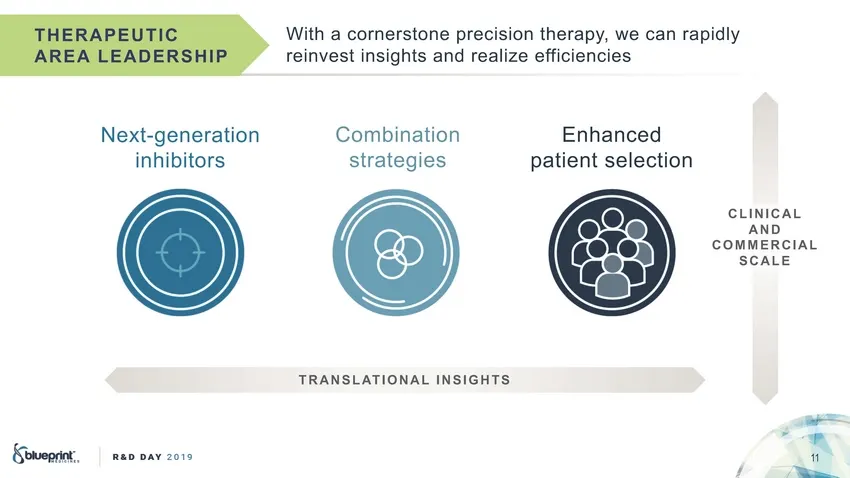
With a cornerstone precision therapy we can rapidly reinvest insights and realize efficiencies THERAPEUTIC AREA LEADERSHIP Next-generation inhibitors Combination strategies Enhanced patient selection CLINICAL AND COMMERCIAL SCALE TRANSL ATIONAL INSIGHTS 11

Slide 12: Therapeutic area leadership in treatment-resistant NSCLC
With a cornerstone precision therapy we can rapidly reinvest insights and realize efficiencies THERAPEUTIC AREA LEADERSHIP for treatment-resistant non-small cell lung cancer 12
Slide 13: Scientific platform enables exploring new kinase biology
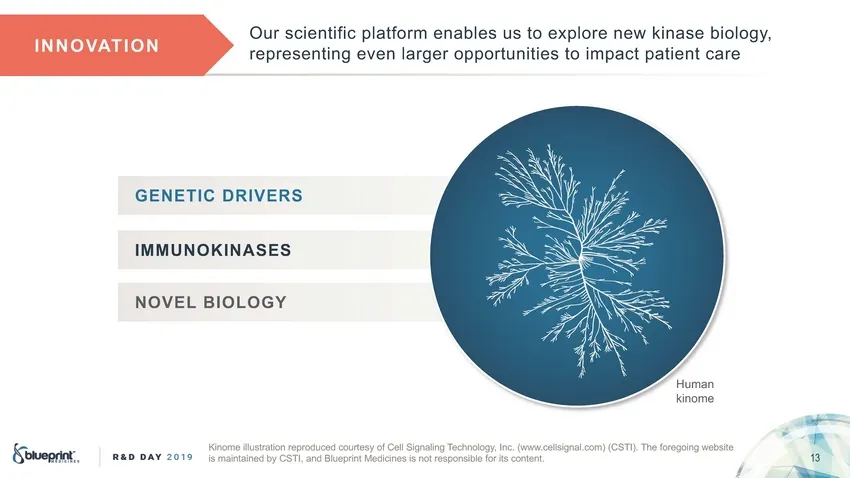
O!r scien ific pla form enables !s o e$plore ne# kinase biolog%, INNO VATION represen ing e"en larger oppor !ni ies o impac pa ien care GENETIC DRIVERS IMMUNOKINASES NOVEL BIOLOGY H!man kinome Kinome ill!s ra ion reprod!ced co!r es% of Cell Signaling Technolog%, Inc. (###.cellsignal.com) (CSTI). The

Slide 14: Platform explores new kinase biology: immunokinase inhibitor
Our scientific platform enables us to e!plore ne kinase biolog", iNNO VATiON representing even larger opportunities to impact patient care immunokinase inhibitor 14 MAP4K1 is a collaboration target under the cancer immunotherap" collaboration ith Roche
Slide 15: Pipeline
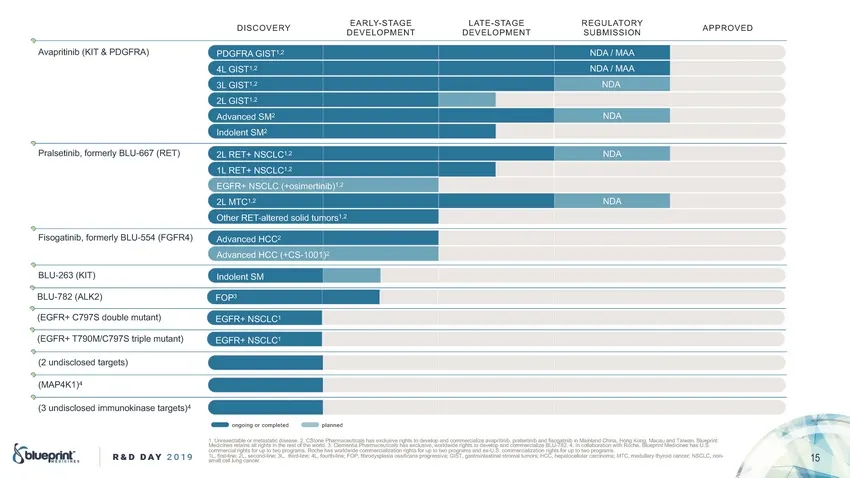
EA$L)-% &A GE LA&E-% &A GE $EG'LA&" $) DI%C"(E$) A##$"(ED DE(EL"# E !& DE(EL"# E !& %'B I%%I"! A=*892;262+ (KI& & #DGF$A) #DGF$A GI%&1,2 4L GI%&1,2 3L GI%&1,2 2L GI%&1,2 A-=*6,.-% 2 I6-74.6; % 2 #9*4:.;262+, /795.94@ BL'-667 ($E&) 2L $E&+ !%CLC1,2 1L $E&+ !%CLC1,2 EGF$+ !%CLC (+7:25.9;262+)1,2 2L &C
Slide 16: Submitted and planned new drug applications in 2020
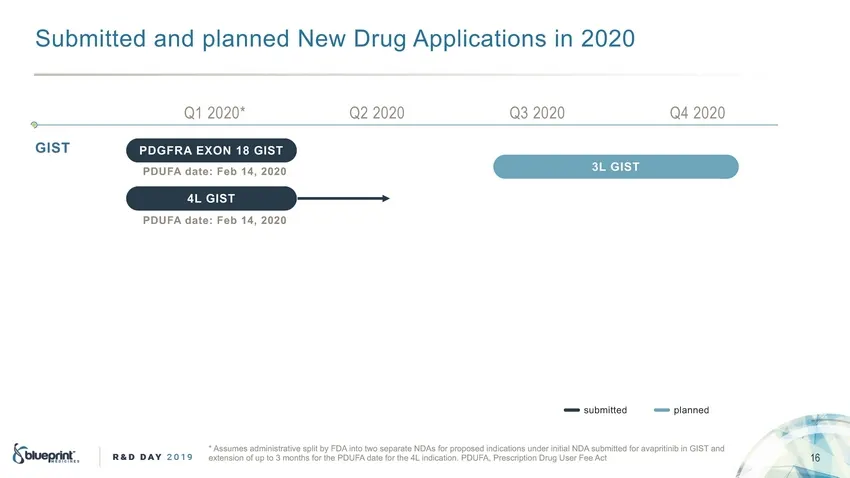
S%bmi$$ed and !lanned Ne' D"%g A!!lica$i n# in 2020 Q1 2020* Q2 2020 Q3 2020 Q4 2020 GIST PDGFRA EXON 18 GIST PDUFA date: Feb 14, 2020 3L GIST 4L GIST PDUFA date: Feb 14, 2020 #%bmi$$ed !lanned * A##%me# admini#$"a$i&e #!li$ b) FDA in$ $' #e!a"a$e NDA# f " !" ! #ed indica$i n# %nde" ini$ial NDA #%bm

Slide 17: Submitted and planned new drug applications in 2020
S%bmi$$ed and !lanned Ne' D"%g A!!lica$i n# in 2020 Q1 2020* Q2 2020 Q3 2020 Q4 2020 GIST PDGFRA EXON 18 GIST PDUFA da e: Feb 14, 2020 3L GIST 4L GIST PDUFA da e: Feb 14, 2020 SM ADVANCED SM #%bmi$$ed !lanned * A##%me# admini#$"a$i&e #!li$ b) FDA in$ $' #e!a"a$e NDA# f " !" ! #ed indica$i n# %nde" i
Slide 18: Submitted and planned new drug applications in 2020
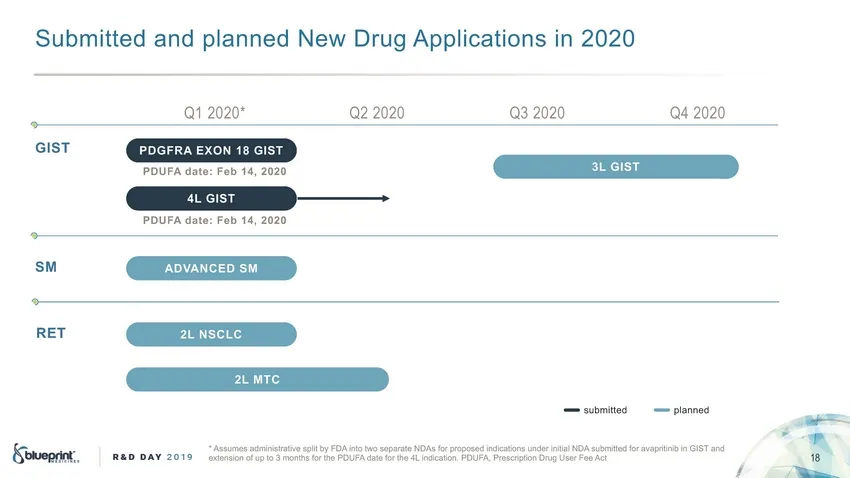
S%bmi$$ed and !lanned Ne' D"%g A!!lica$i n# in 2020 Q1 2020* Q2 2020 Q3 2020 Q4 2020 GIST PDGFRA EXON 18 GIST PDUFA da e: Feb 14, 2020 3L GIST 4L GIST PDUFA da e: Feb 14, 2020 SM ADVANCED SM RET 2L NSCLC 2L MTC #%bmi$$ed !lanned * A##%me# admini#$"a$i&e #!li$ b) FDA in$ $' #e!a"a$e NDA# f " !" ! #ed
Slide 19: R&D Day agenda
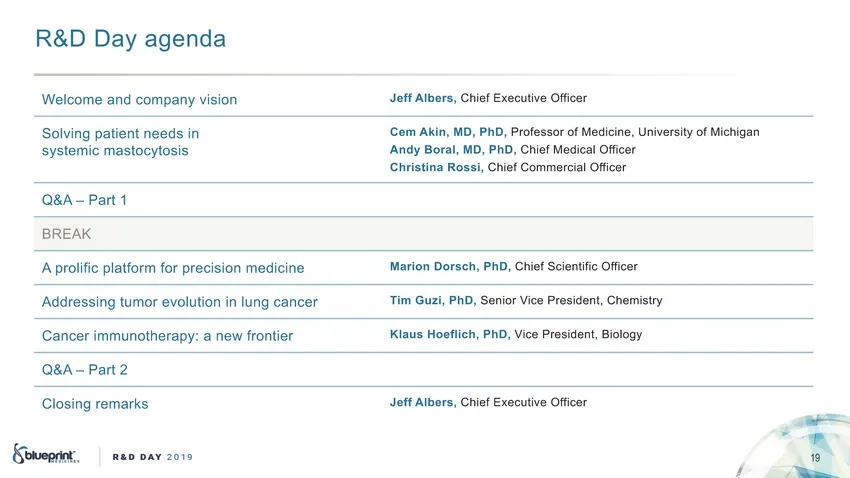
R&D Da+ age!da Jeff Albers, Chief E*ec'&i(e Office$ We c" e a!d c" #a!+ (i%i"! Cern Akin, MD, PhD, P$"fe%%"$ "f Medici!e, U!i(e$%i&+ "f Michiga! And Boral, MD, PhD, Chief Medica Office$ S" (i!g #a&ie!& !eed% i! %+%&eic a%&"c+&"%i% Christina Rossi, Chief C" e$cia Office$ Q&A , Pa$& 1 Marion Dorsch, P

Slide 20: Systemic mastocytosis
{Soweprint. SYSTEMIC MASTOCYTOSIS

Slide 21: Addressing patient needs in systemic mastocytosis
Addressing patient needs in systemic mastocytosis Cern Akin, M.D., Ph.D. Professor of Medicine, University of Michigan Andy Boral, M.D., Ph.D. Chief Medical Officer Christy Rossi Chief Commercial Officer J D v ng w th SM

Slide 22: Systemic mastocytosis is one disease with a common genetic driver
Systemic mastocytosis is one disease with a common genetic driver KIT D816V mutation frequency AD VANCED SYSTEMIC MASTO CYTO SIS -95% of patients INDOLENT SYSTEMIC MASTO CYTO SIS 22

Slide 23: Overview of indolent systemic mastocytosis
Overview of indolent systemic mastocytosis CEM AKIN, MD, PhD Professor of Medicine, University of Michigan

Slide 24: Disclosures
Di$cl!$&#e$ ) ) Cem Aki MD PhD I i 'e$%iga%!#: Bl&e"#i % Medici e$* ! g!i g Pha$e 2 PIONEER %#ial i d!le % $($%emic ma$%!c(%!$i$ ) ) C! $&l%a %: Bl&e"#i % Medici e$ N!'a#%i$ A'a"#i%i Medici ib i$ a i 'e$%iga%i! al age % bei g de'el!"ed b( Bl&e"#i % e$ a d ha$ !% bee a""#!'ed b( %he F!!d ad D#&g Admi

Slide 25: Patient with indolent SM
Pa/%!)/ 1 7 I) *'!)/ SM 6 6 6 6 6 6 6 6 45-4!a--*' "!(a'! Ha *).!/ *" .&%) '!.%*). a/ a#! 7 D%a#)*.! a/ a#! 14 b4 a .&%) b%*+.4 I)%/%a''4 *)'4 .4(+/*(. 2!-! .&%) '!.%*). a) !3!-c%.! %) 0c! 2$!!5%)# 29 4!a-. Na0.!a, %a--$!a, %)c-!a.! %/c$%)#, "'0.$%)#, b*)! +a%) Pa..! *0/ /2%c!, b'** +-!..0-! 2a. 0)

Slide 26: Patient with indolent SM: medications
Pa* e%* 1 1 I%d&#e%* SM 0 Med ca* &%): 1 1 1 1 1 1 1 1 1 1 1 1 1 1 Ce* ( / %e 10 $g da #. Fe-&fe%ad %e 180 $g da #. M&%*e#+"a)* 10 $g da #. Be%ad(.# e,e(. 4-6 h&+() H.d(&-./ %e a) %eeded D c#&fe%ac a) %eeded E' Pe% a) %eeded O$a# /+$ab &%ce $&%*h#. O$e'(a/&#e da #. Z&f(a% da #. Ra% * d %e 300 $g da

Slide 27: Patient with indolent SM: 51-year-old case
Pa,"e&, 2 4 I&d'$e&, SM 3 3 3 3 3 51-1ea*-'$d %a$e S#"& $e+"'&+ a+ a ,ee&a e* D"a &'+ed a, a e 31 b1 +#"& b"'(+1 T*1(,a+e /a+ 15, a&d &' b'&e %a**'/ b"'(+1 /a+ (e*f'*%ed "&","a$$1 A 4 e 47: De.e$'(ed $"fe-,!*ea,e&"& +1%(,'%+ E("+'de+ 'f abd'%"&a$ c*a%("& c'&+c"'-+&e++ , f$-+!"& , +!'*,&e++ 'f b*ea,!
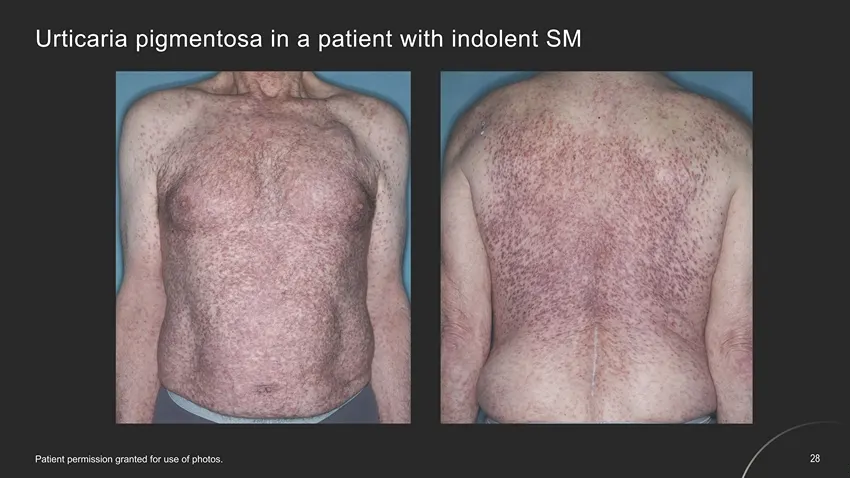
Slide 28: Urticaria pigmentosa in a patient with indolent SM
Urticaria pigmentosa in a patient with indolent SM 28 Patient permission granted for use of photos.
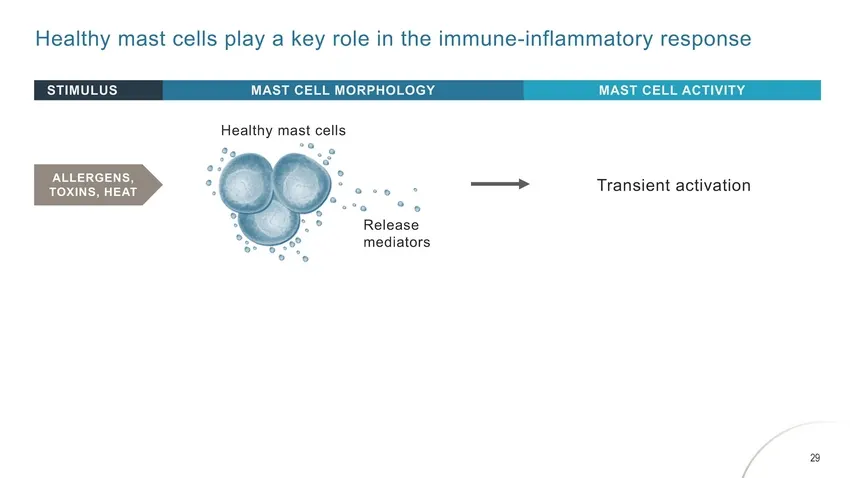
Slide 29: Healthy mast cells play a key role in immune response
Healthy mast cells play a key role in the immune-inflammatory response Healthy mast cells ALLERGENS, TOXINS, HEAT Transient activation Release mediators 29 STIMULUS MAST CELL MORPHOLOGY MAST CELL ACTIVITY
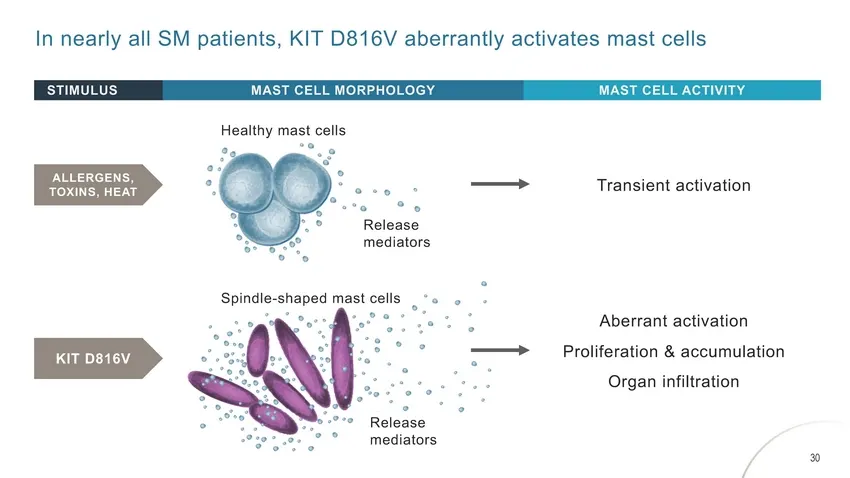
Slide 30: KIT D816V aberrantly activates mast cells
In nea"l' all SM !a$ en$#, KIT D816V abe""an$l' ac$ &a$e# ma#$ cell# Heal$h' ma#$ cell# ALLERGENS, TOXINS, HEAT T"an# en$ ac$ &a$ n Relea#e med a$ "# S! ndle-#ha!ed ma#$ cell# Abe""an$ ac$ &a$ n P" l fe"a$ n & acc%m%la$ n KIT D816V O"gan nf l$"a$ n Relea#e med a$ "# 30 STIMULUS MAST CELL MORPHOLOGY
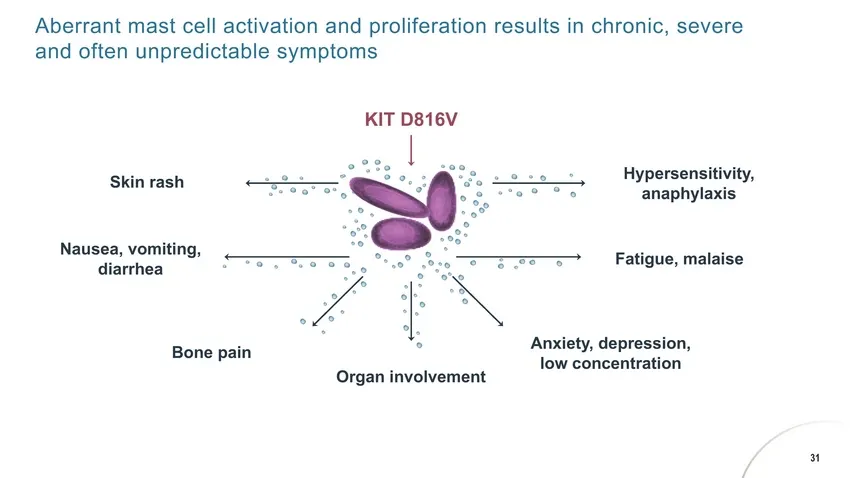
Slide 31: Aberrant mast cell activation results in chronic, severe symptoms
Aberrant mast cell activation and proliferation results in chronic, severe and often unpredictable symptoms KIT D816V Hypersens anaphylaxis Skin rash a ty, vomiting, diarrhea Fatigue, n Anxiety, depression, Bone pain : e low concentration Organ involvement
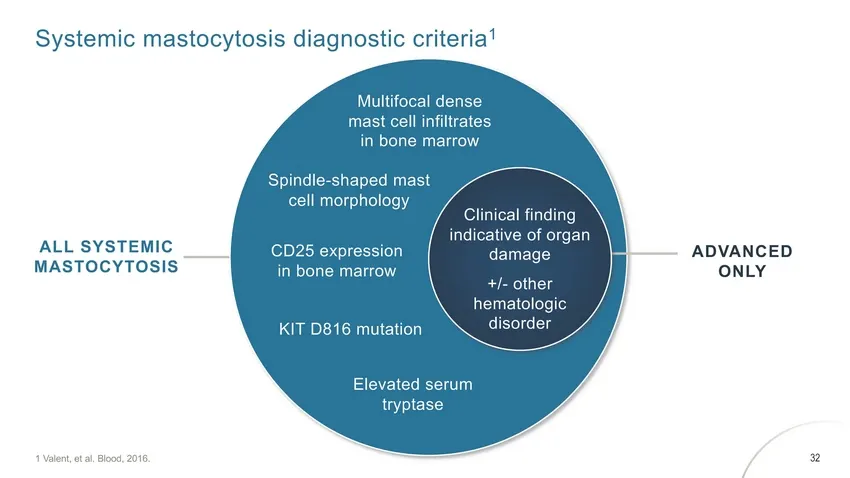
Slide 32: Systemic mastocytosis diagnostic criteria
diag"#&'ic c%i'e%ia1 S,&'e!ic !a&'#c,'#&i& C i"ica fi"di"g i"dica'i)e #f #%ga" da!age +/-#'he% he!a'# #gic di&#%de% ALL SYSTEMIC MASTOCYTOSIS AD VANCED ON LY 32 1 Va e"', e' a . 8 ##d, 2016.
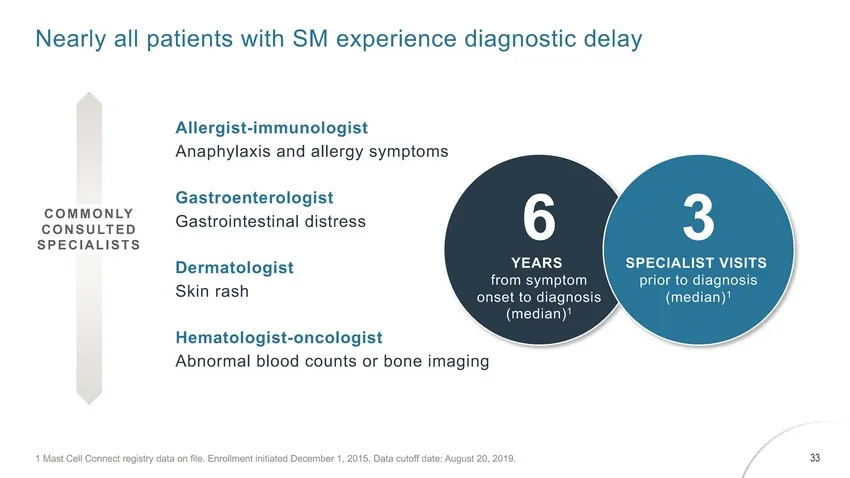
Slide 33: Indolent SM patients report high symptom burden
I-$.+%-3 SM /!3)%-32 1%/.13 ()'( 28,/3., "41$%-F1%04%-#8 .& ,.$%1!3% 3. 2%5%1% 28,/3.,2 6)3()-+!23 8%!1, $%2/)3% "%23 !5!)+!"+% 3(%1!/8 34 M!23 C%++ C.--%#3 1%')2318 $!3! .-&)+%. E-1.++,%-3 )-)3)!3%$ D%#%,"%1 1, 2015. D!3! #43.&& $!3%: A4'423 20, 2019. ISM (n=109) AdvSM (n=15) Gastrointestinal sympt
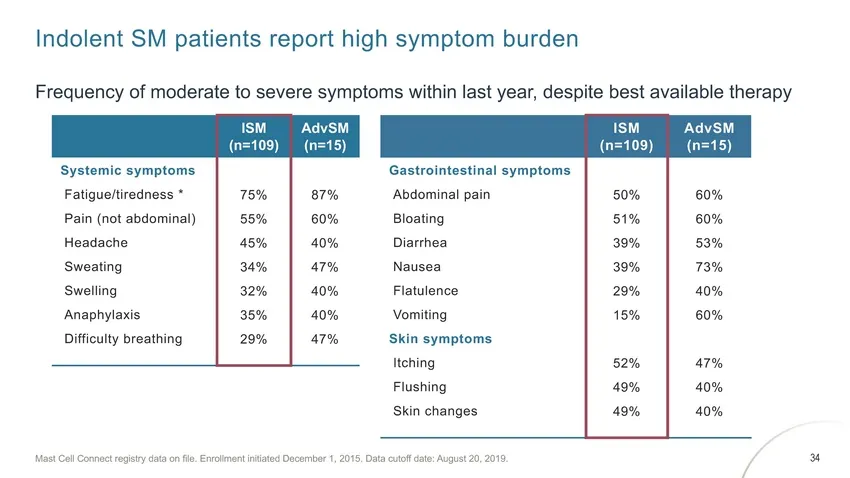
Slide 34: Indolent SM patients report high symptom burden
I-$.+%-3 SM /!3)%-32 1%/.13 ()'( 28,/3., "41$%-F1%04%-#8 .& ,.$%1!3% 3. 2%5%1% 28,/3.,2 6)3()-+!23 8%!1, $%2/)3% "%23 !5!)+!"+% 3(%1!/8 34 M!23 C%++ C.--%#3 1%')2318 $!3! .-&)+%. E-1.++,%-3 )-)3)!3%$ D%#%,"%1 1, 2015. D!3! #43.&& $!3%: A4'423 20, 2019. ISM (n=109) AdvSM (n=15) Gastrointestinal sympt
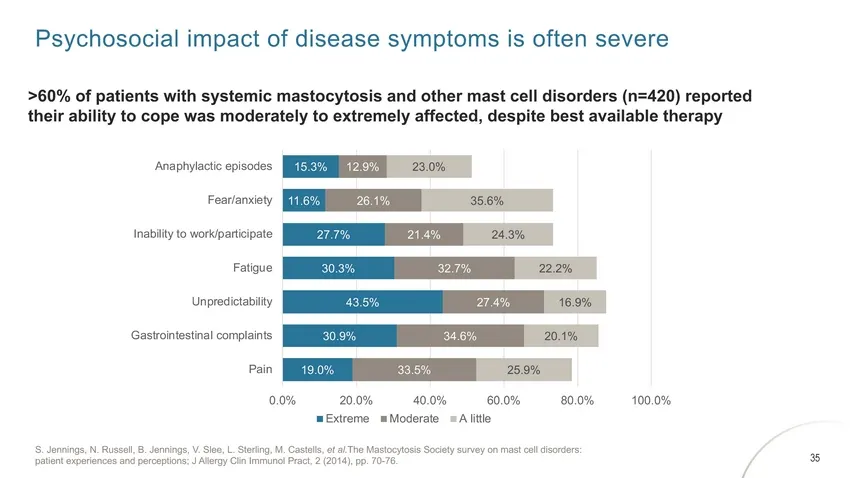
Slide 35: Patients report ability to cope moderately to extremely affected
6<(-363(.&0 .14&(7 3+ ).6*&6* 6<147316 .6 3+7*2 6*9*5* >60% of patients with systemic mastocytosis and other mast cell disorders (n=420) reported their ability to cope was moderately to extremely affected, despite best available therapy A2&4-<0&(7.( *4.63)*6 F*&5/&2;.*7< 2&'.0.7< 73 :35//4&57.(.4&7*
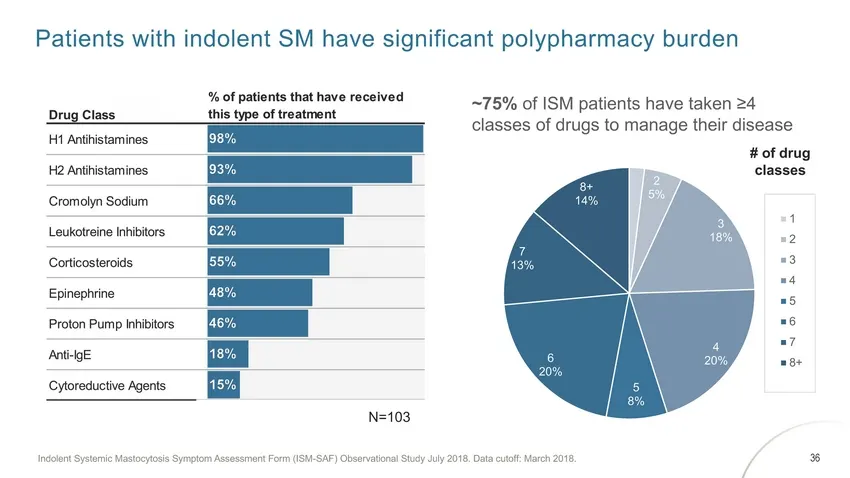
Slide 36: Patients in indolent SM use significant polypharmacy
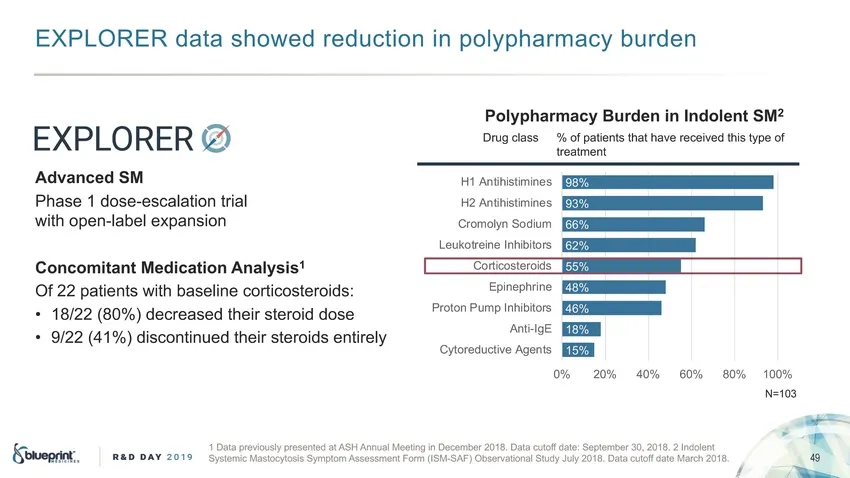
Pa.%!).-1%.$ %) *'!). SM $a0! -%#)%"%ca). +*'2+$a,(ac2 b/, !) -75% *" ISM +a.%!).-$a0! .a&!) 34 c'a--!-*" ,/#-.* (a)a#! .$!%, %-!a-! # of drug classes 8+ 14% 5% 3 18% 7 13% 4 20% 20% 5 8% N=103 36 I) *'!). S2-.!(%c Ma-.*c2.*-%-S2(+.*( A--!--(!). F*,( (ISM-SAF) Ob-!,0a.%*)a' S./ 2 J/'2 2018 Da.a c/.*
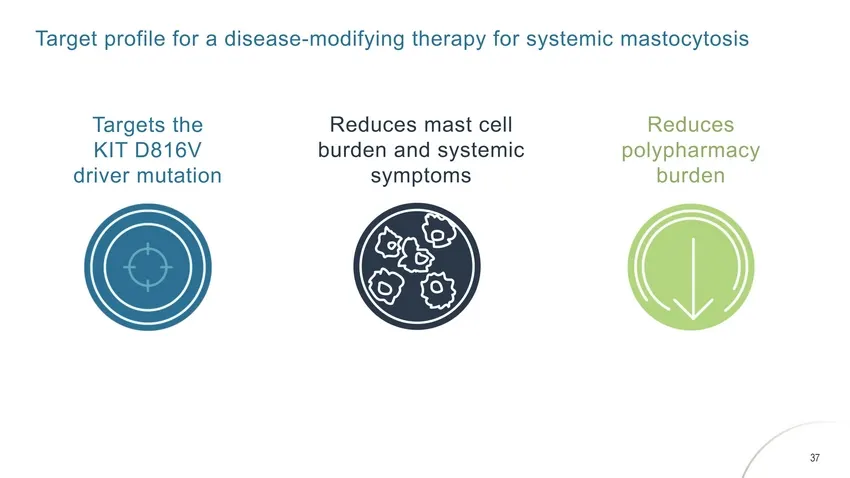
Slide 37: Target profile for a disease-modifying therapy
Target profile for a disease-modifying therapy for systemic mastocytosis Reduces mast cell burden and systemic symptoms Reduces polypharmacy burden Targets the K T D816V driver mutation 37

Slide 38: Avapritinib for indolent systemic mastocytosis
Avapritinib for indolent systemic mastocytosis ANDY BORAL, MD, PhD Chief Medical Officer
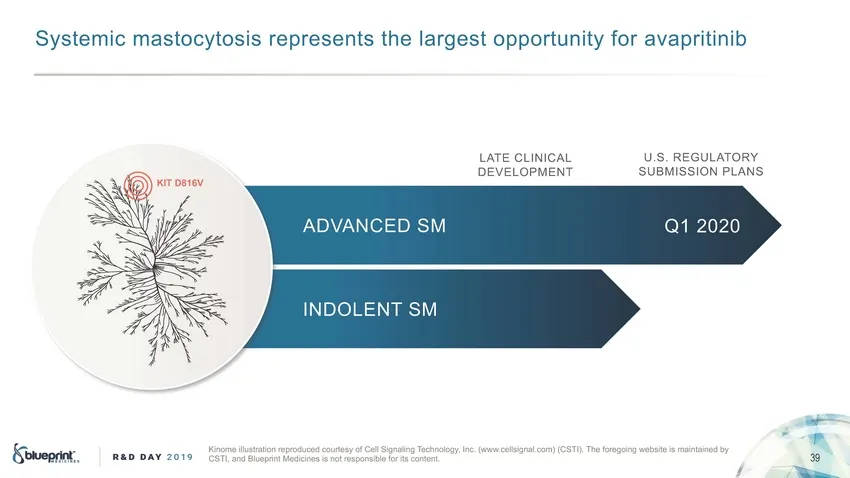
Slide 39: Systemic mastocytosis: U.S. regulatory submission plans
S1,-!'%c 'a,-)c1-),%, +!*+!,!(-, -$! &a+#!,-)**)+-.(%-1 ")+ a/a*+%-%(%b U.S. REGULATORY SUBMISSION PLANS LATE CLINICAL DEVELOPMENT KIT D816V ADVANCED SM Q1 2020 INDOLENT SM K%()'! %&&.,-+a-%)( +!*+) .c! c).+-!,1 )" C!&& S%#(a&%(# T!c$()&)#1, I(c. (000.c!&&,%#(a&.c)') (CSTI). T$! ")+!#)%(# 0!b,%-! %,
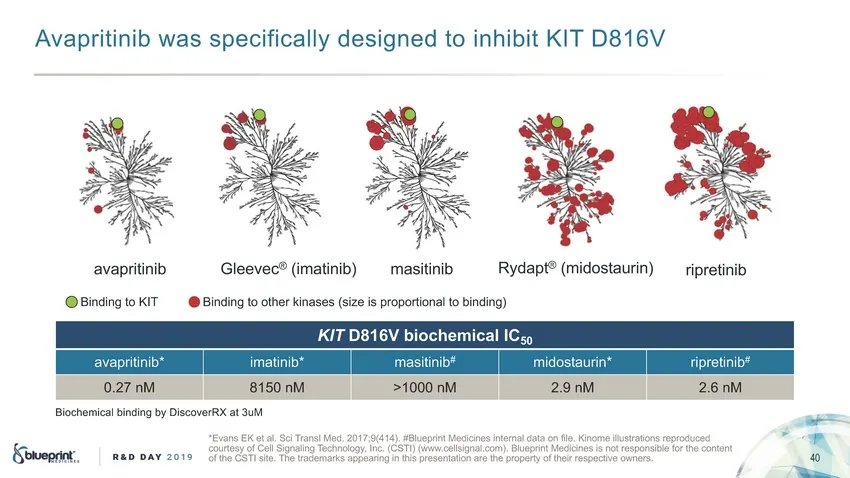
Slide 40: Avapritinib designed to inhibit KIT D816V
A5"01*3*.*# 6"2 20&$*'*$",,7 %&2*(.&% 3/ *.)*#*3 KIT 0816 R7%"039 (-*%/23"41*.) G,&&5&$9 (*-"3*.*#) "5"01*3*.*# -"2*3*.*# 1*01&3*.*# B*.%*.( 3/ KIT B*.%*.( 3/ /3)&1 +*."2&2 (2*8& *2 01/0/13*/.", 3/ #*.%*.() B*/$)&-*$", #*.%*.( #7 0*2$/5&1R! "3 34M *E5".2 EK &3 ",. S$* T1".2, M&%. 2017;9(414). #B,4&0
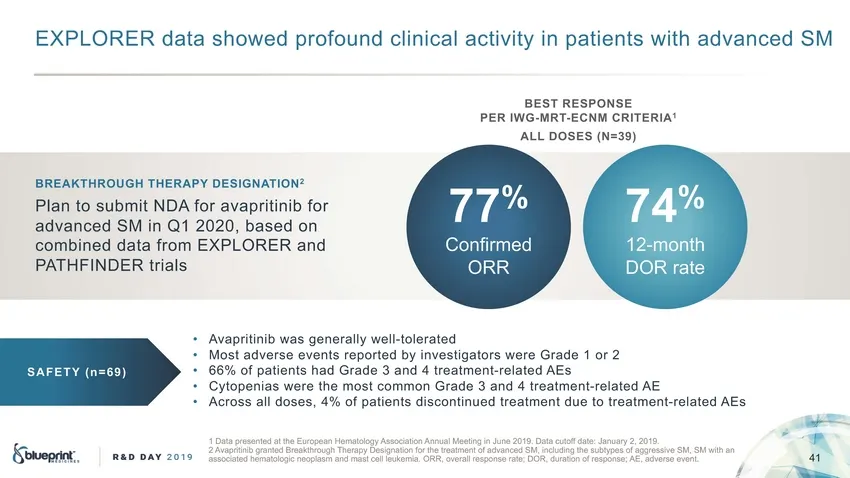
Slide 41: EXPLORER: advanced SM best response
E"PLORER # 3*07'& 120(05/& %-+/+%#-#%4+6+48 +/ 1#4+'/43 7+4* #&6#/%'& M BEST RESPONSE PER I!G-MRT-ECNM CRITERIA1 ALL DOSES (N=39) BREAKTHRO GH THERAP" DESIGNATION2 77% C0/(+2.'& ORR 74% 12-.0/4* DOR 2#4' P-#/ 40 35$.+4 NDA (02 #6#12+4+/+$ (02 #&6#/%'& M +/ Q1 2020, $#3'& 0/ %0.$+/'& # (20. E"P
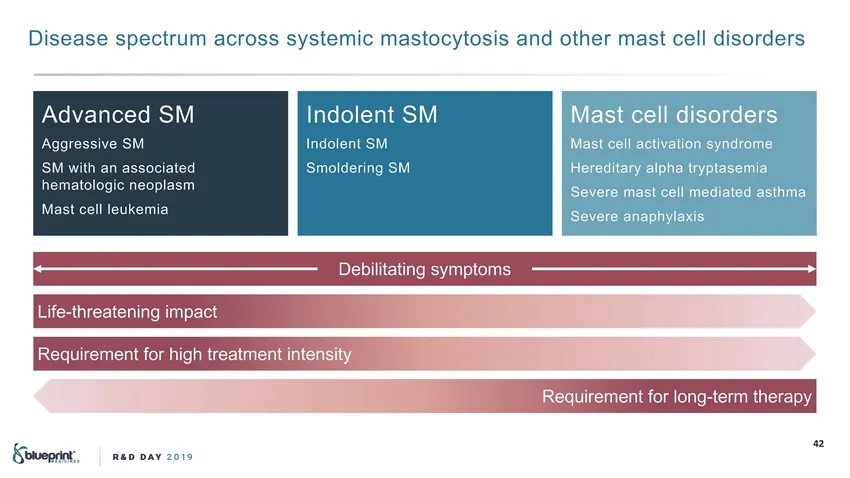
Slide 42: Disease spectrum across systemic mastocytosis and mast cell disorders
Disease spectrum across s"stemic mastoc"tosis and other mast cell disorders Life-threatening impact Requirement for high treatment intensit" Requirement for long-term therap" 42 Debilitating s"mptoms Mast cell disorders Mast cell activation s"ndrome Hereditar" alpha tr"ptasemia Severe mast cell medi

Slide 43: Comprehensive systemic mastocytosis clinical trial program
Comprehensive systemic mastocytosis clinical trial program Advanced SM Phase 1 dose-escalation trial with open-label expansion Advanced SM Phase 2 single-arm trial 43
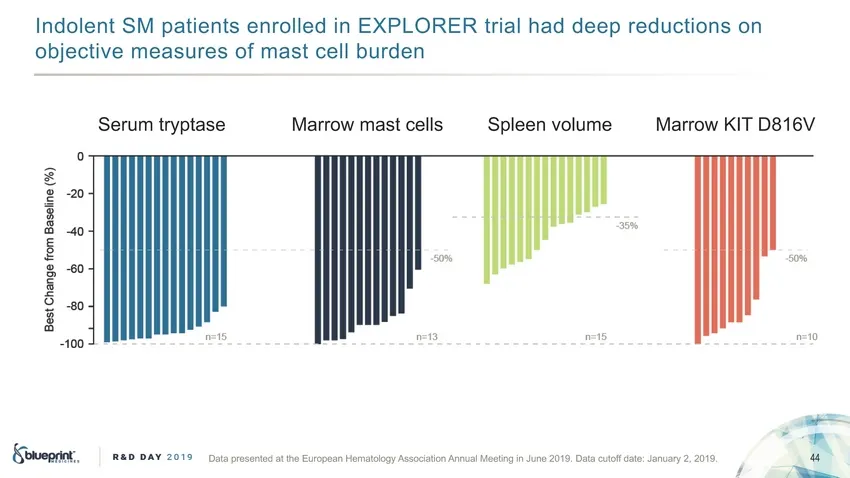
Slide 44: Indolent SM patients enrolled in EXPLORER
I'd(%e', SM )a,#e',+ e'*(%%ed #' EXPLORER ,*#a% "ad dee) *ed-c,#('+ (' (b$ec,#.e &ea+-*e+ ( &a+, ce%% b-*de' Se*-& ,*0),a+e Ma**(/ &a+, ce%%+ S)%ee' .(%-&e Ma**(/ KIT D816V 44 Da,a )*e+e',ed a, ,"e E-*()ea' He&a,(%(!0 A++(c#a,#(' A''-a% Mee,#'! #' J-'e 2019. Da,a c-,( da,e Ja'-a*0 2, 2019.
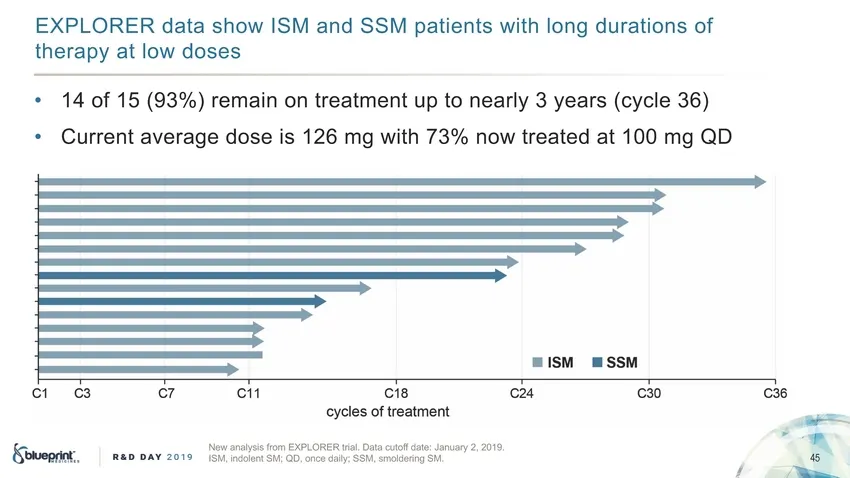
Slide 45: EXPLORER: ISM and SSM patients
EXPLORER " / .&+2 ISM *" SSM , /'#*/. 2'/& (+*% "0-/'+*. +$ /&#-,3 / (+2 "+.#. 4 4 14 +$ 15 (93%) -#) '* +* /-# /)#*/ 0, /+ *# -(3 3 3# -. (!3!(# 36) C0--#*/ 1#-%# "+.# '. 126 )% 2'/& 73% *+2 /-# /#" / 100 )% QD N#2 * (3.'. $-+) EXPLORER /-' (. D / !0/+$$ " /# J *0 -3 2, 2019. ISM, '*"+(#*/ SM; QD,
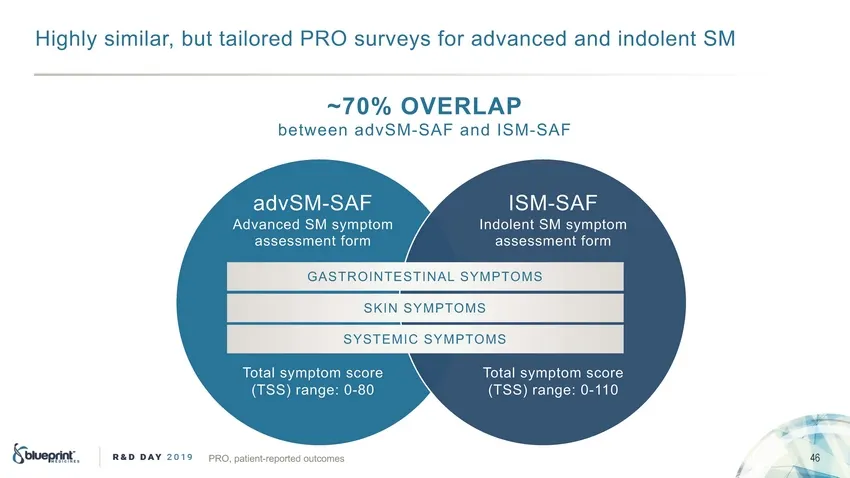
Slide 46: EXPLORER: reduction in polypharmacy burden
E# LO!E! '$5$ 4+18(' 3('6&5,10 ,0 21.:2+$3/$&: %63'(0 Polypharmacy Burden in Indolent SM2 D36* &.$44 % 1) 2$5,(054 5+$5 +$7( 3(&(,7(' 5+,4 5:2( 1) 53($5/(05 Advanced SM +$4( 1 '14(-(4&$.$5,10 53,$. 8,5+ 12(0-.$%(. (92$04,10 H1 A05,+,45,/,0(4 H2 A05,+,45,/,0(4 C31/1.:0 "1',6/ L(6-153(,0( I0+,%,5134 C
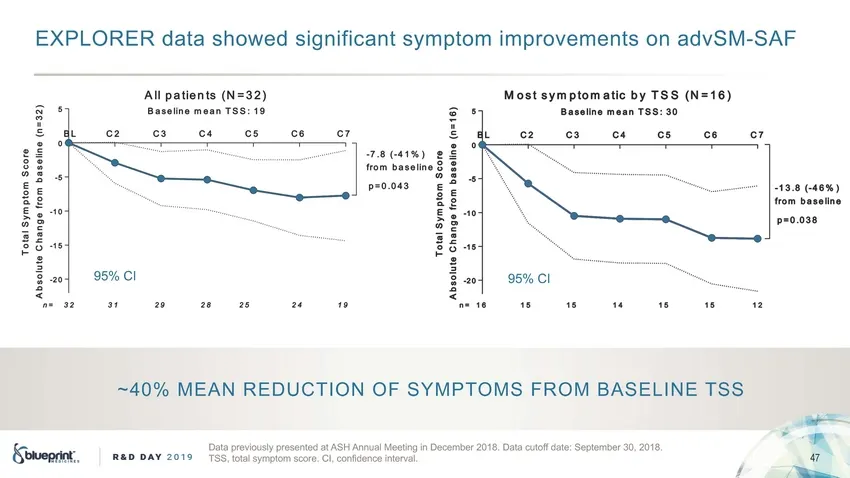
Slide 47: Patient case: systemic mastocytosis response
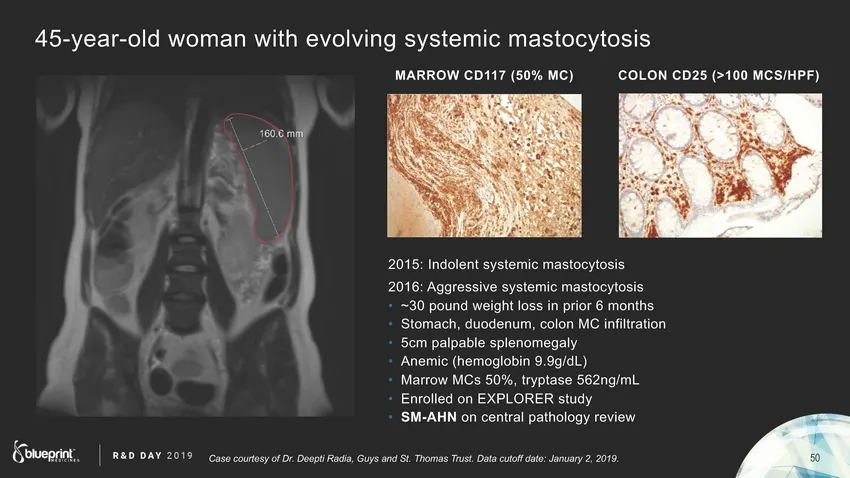
45-1!a+-)& 0)'a( 0%-$ !/)&/%(# ,1,-!'%c 'a,-)c1-),%, MARROW CD117 (50% MC) COLON CD25 (>100 MCS/HPF) 2015: I( )&!(-,1,-!'%c 'a,-)c1-),%, 2016: A##+!,,%/! ,1,-!'%c 'a,-)c1-),%, 3 3 3 3 3 3 3 230 *).( 0!%#$-&),, %( *+%)+ 6 ')(-$, S-)'ac$, .) !(.', c)&)( MC %("%&-+a-%)( 5c' *a&*ab&! ,*&!()'!#a&1 A(!'%c
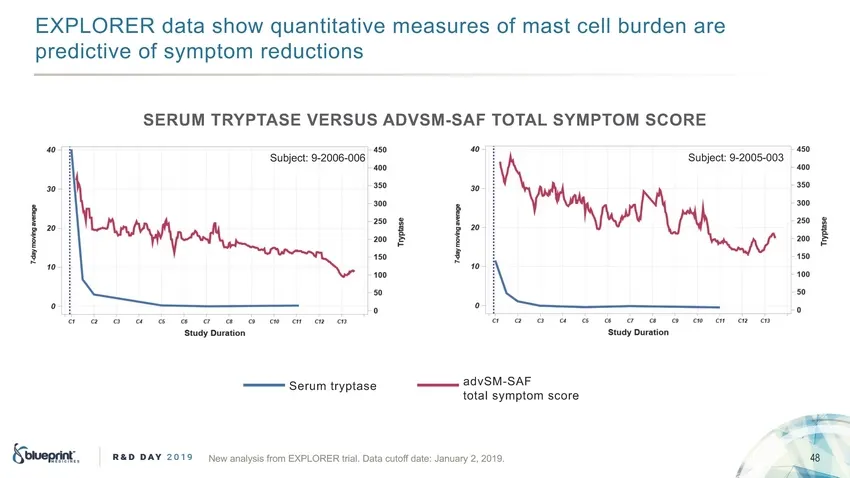
Slide 48: Mast cell burden predictive of symptom reductions
EXPLORER data show quantitative measures of mast cell burden are predictive of symptom reductions SERUM TRYPTASE VERSUS ADVSM-SAF TOTAL SYMPTOM SCORE ‘Subject: 8-2006-006 Subject: 9-2005.008 1 Study Duration ‘Study Duration Serum tryptase —— advSM-SAF total symptom score
Slide 49: EXPLORER reduction in polypharmacy burden
EXPLORER data showed reduction in polypharmacy burden EXPLORER & Advanced SM Phase 1 dose-escalation trial with open-label expansion Concomitant Medication Analysis’ Of 22 patients with baseline corticosteroids: + 18/22 (80%) decreased their steroid dose + 9/22 (41%) discontinued their steroids enti
Slide 50: Patient case: systemic mastocytosis response
45-1!a+-)& 0)'a( 0%-$ !/)&/%(# ,1,-!'%c 'a,-)c1-),%, MARROW CD117 (50% MC) COLON CD25 (>100 MCS/HPF) 2015: I( )&!(-,1,-!'%c 'a,-)c1-),%, 2016: A##+!,,%/! ,1,-!'%c 'a,-)c1-),%, 3 3 3 3 3 3 3 230 *).( 0!%#$-&),, %( *+%)+ 6 ')(-$, S-)'ac$, .) !(.', c)&)( MC %("%&-+a-%)( 5c' *a&*ab&! ,*&!()'!#a&1 A(!'%c
Slide 51: Bone marrow mast cells and serum tryptase
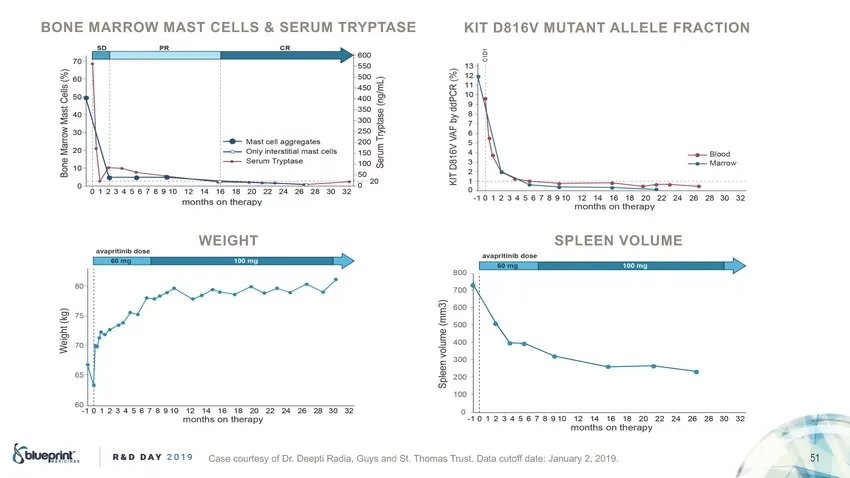
BONE MARROW MAST CELLS & SERUM TRYPTASE KIT D816V MUTANT ALLELE FRACTION WEIGHT SPLEEN VOLUME 51 Case courtesy of Dr. Deepti Radia, Guys and St. Thomas Trust. Data cutoff date: January 2, 2019.
Slide 52: Colon CD25, marrow CD117, MRI abdomen
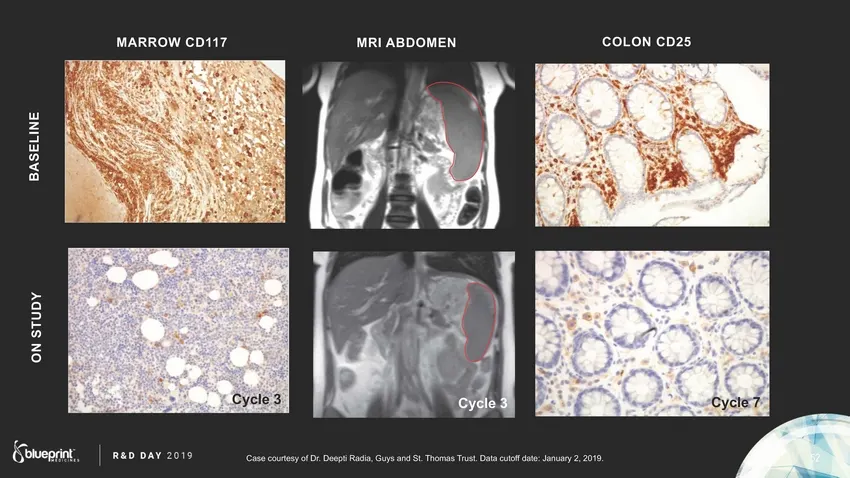
COLON CD25 MARROW CD117 MRI ABDOMEN Cycle 3 Cycle 7 Cycle 3 52 Case courtesy of Dr. Deepti Radia Guys and St. Thomas Trust. Data cutoff date: January 2 2019. BASELINE ON STUDY
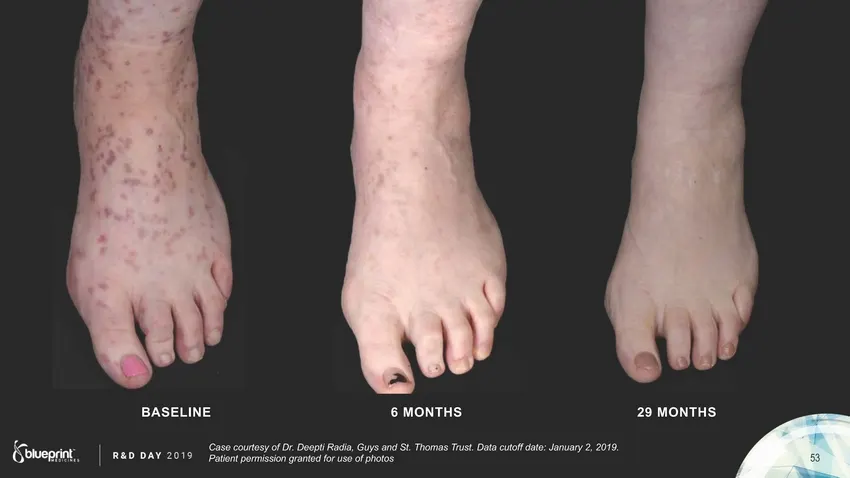
Slide 53: Baseline and months on study
BASELINE 6 MONTHS 29 MONTHS Case co rtes! of Dr. Deepti Radia, G !s and St. Thomas Tr st. Data c toff date: Jan ar! 2, 2019. atient permission ranted for se of photos 53
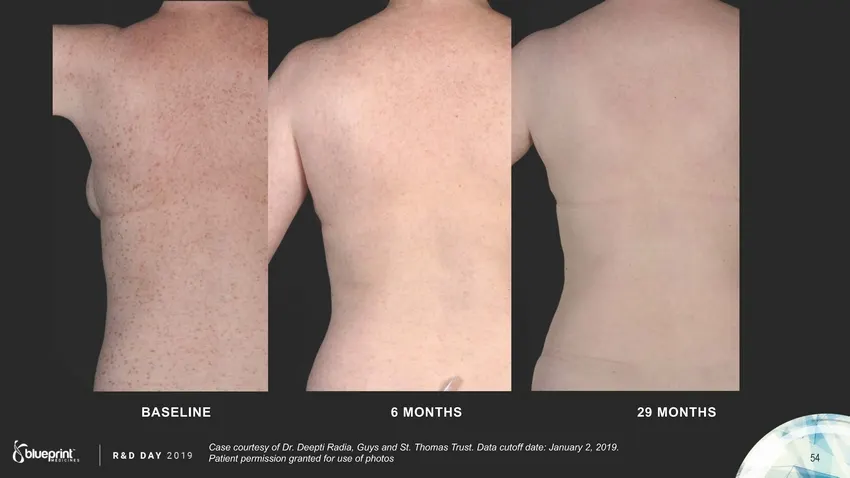
Slide 54: Baseline and months on study
BASELINE 6 MONTHS 29 MONTHS Case co rtes! of Dr. Deepti Radia, G !s and St. Thomas Tr st. Data c toff date: Jan ar! 2, 2019. atient permission ranted for se of photos 54

Slide 55: Comprehensive systemic mastocytosis clinical trial program
Comprehensive s stemic mastoc tosis clinical trial program Advanced SM Phase 1 dose-escalation trial with open-label expansion Advanced SM Phase 2 single-arm trial Indolent SM Phase 2 randomi!ed, double-blind, placebo-controlled trial 55
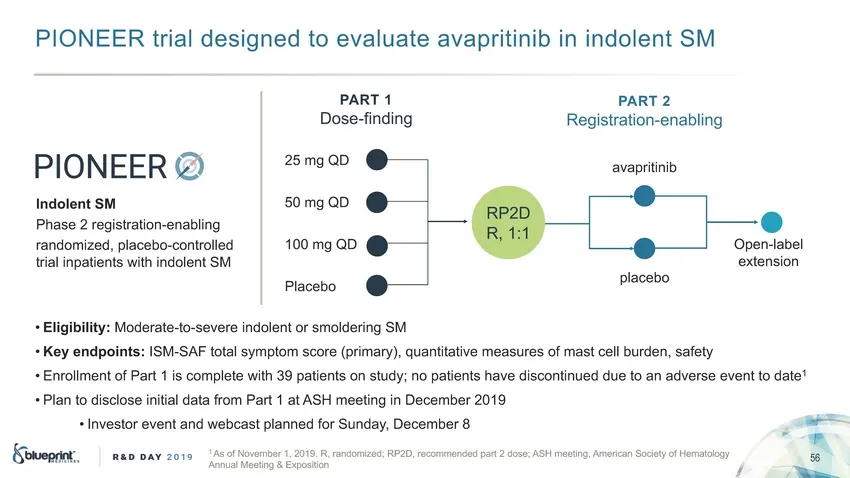
Slide 56: PIONEER trial in indolent SM
PIONEER /-&a' !".&$)"! /* "1a'0a/" a1a+-&/&)&b &) &)!*'")/ SM PART 1 D*."-#&)!&)$ PART 2 R"$&./-a/&*)-")ab'&)$ 25 ($ QD a1a+-&/&)&b 50 ($ QD indolent SM P%a." 2 -"$&./-a/&*)-")ab'&)$ -a)!*(&5"!, +'a"b*-*)/-*''"! /-&a' &)+a/&")/. 2&/% &)!*'")/ SM RP2D R, 1:1 100 ($ QD O+")-'ab"' "3/").&*) +'a "b* P'a

Slide 57: A comprehensive program for mast cell disorders
A comprehensive program for mast cell disorders CHRISTINA ROSSI Chief Commercial Officer

Slide 58: Systemic mastocytosis epidemiology
E:3$1'(' SM 23324671,6; %$5(' 21 ,1&4($5(' 71'(456$1',1* 2) 6+( ',5($5( SYSTEMIC MASTOCYTOSIS EPIDEMIOLOGY -75,000 34(8$/(16 3$6,(165 ,1 0$-24 0$4.(65 1 -20,000 patients $4( ,'(16,),$%/( 9,6+,1 &/$,05 '$6$ ,1 6+( 1,6(' S6$6(5 2 MOST AD LTS "ITH C TANEO S S#MPTOMS "ILL SHO" S#STEMIC DISEASE "HEN F LL
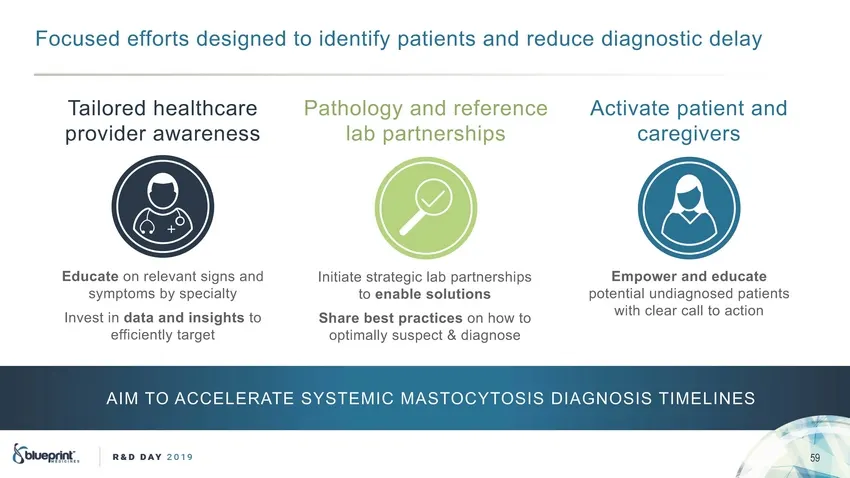
Slide 59: Focused efforts to identify patients and reduce diagnostic delay
Foc$"ed effo!#" de"igned #o iden#if' a#ien#" and !ed$ce diagno"#ic dela' Tailo!ed heal#hca!e !o%ide! a&a!ene"" Pa#holog' and !efe!ence Ac#i%a#e a#ien# and lab a!#ne!"hi " ca!egi%e!" Educate on !ele%an# "ign" and "'m#om" b' " ecial#' In%e"# in data and insights #o efficien#l' #a!ge# Empower and educa
Slide 60: Indication expansion: next-generation KIT inhibitor
We aim to make transformative precision therapies and expand their application to additional patient populations over time INDIC ATION EX PANSION A next-generation KIT inhibitor for mast cell disorders 60
Slide 61: Disease spectrum across systemic mastocytosis and mast cell disorders
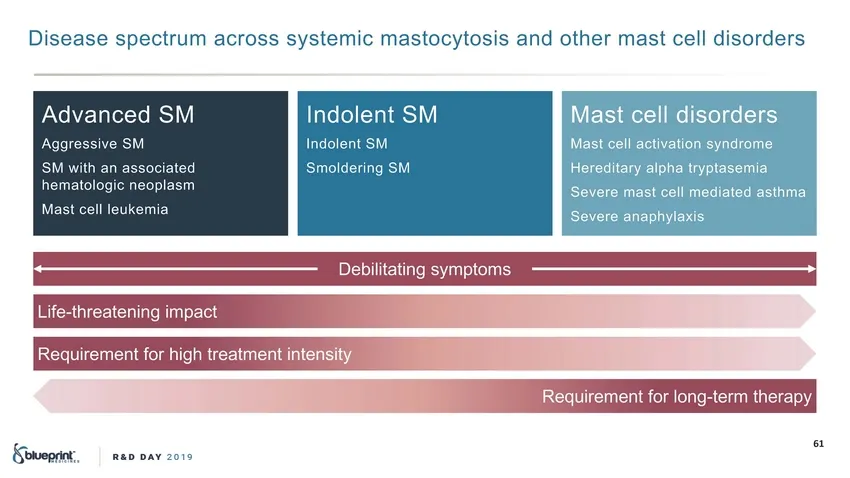
Disease spectrum across s"stemic mastoc"tosis and other mast cell disorders Life-threatening impact Requirement for high treatment intensit" Requirement for long-term therap" 61 Debilitating s"mptoms Mast cell disorders Mast cell activation s"ndrome Hereditar" alpha tr"ptasemia Severe mast cell medi
Slide 62: BLU-263 designed for mast cell disorders spectrum
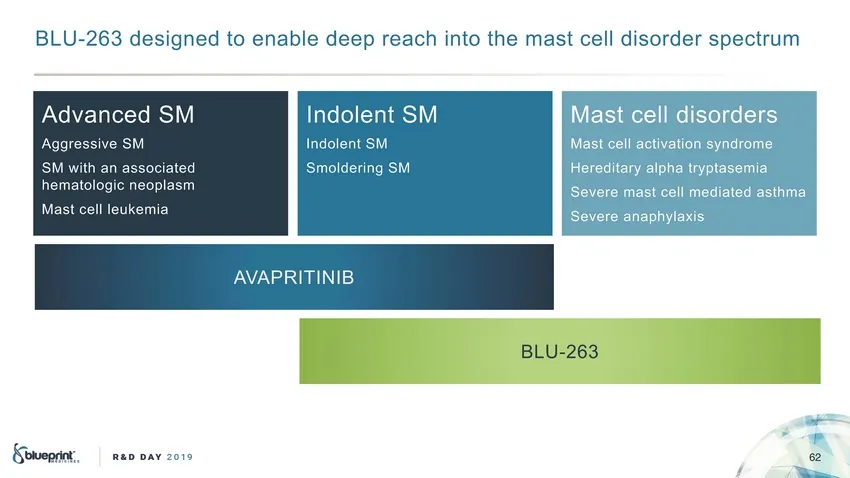
BLU-263 de"igned #o enable dee !each in#o #he ma"# cell di"o!de! " ec#!$m AVAPRITINIB BLU-263 62 Ma"# cell di"o!de!" Ma"# cell ac#i%a#ion "(nd!ome He!edi#a!( al ha #!(#a"emia Se%e!e ma"# cell media#ed a"#hma Se%e!e anah(la'i" Indolen# SM Indolen# SM Smolde!ing SM Ad%anced SM Agg!e""i%e SM SM &i#h an
Slide 63: BLU-263 profile
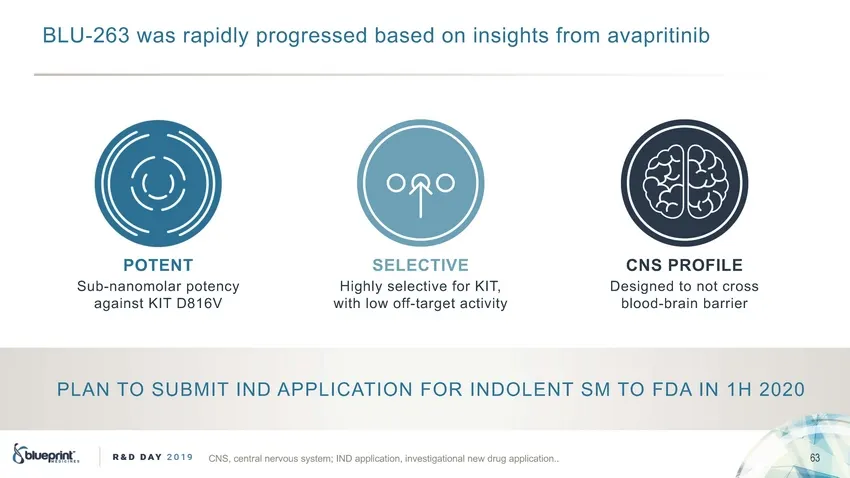
BLU-263 2a. -a,'"(3 ,-+%-#..#" a.#" +* '*.'%&/. $-+) a1a,-'/'*' POTENT -*a*+)+(a-,+/#*!3 SELECTIVE H'%&(3 .#(#!/'1# $+-K T, 2'/& (+2 +$$-/a-%#/ a!/'1'/3 CNS PROFILE D#.'%*#" /+ *+/ !-+.. S0 a%a'*./ K T D816V (++"--a'* a--'#-PLAN TO SUBM T ND APPL CAT ON FOR NDOLENT SM TO FDA N 1H 2020 63 CNS, !#*/-a
Slide 64: BLU-263 preclinical potency and selectivity
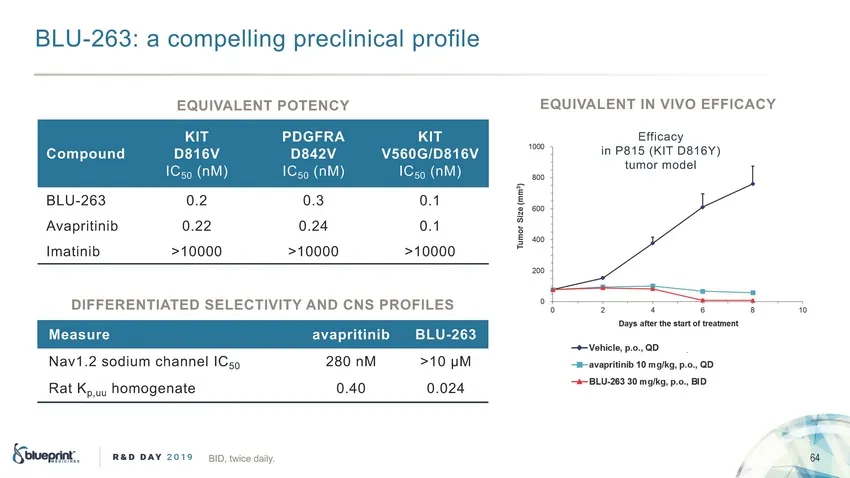
BLU-263: ",*-$))(+& -.$")(+(" ) -.,%()$ EQUIVALENT IN VIVO EFFICAC EQUIVALENT POTENC E%%(""4 (+ P815 (KIT D816Y) 01*,. *,#$) BLU-263 0.2 0.22 >10000 0.3 0.24 >10000 0.1 0.1 >10000 A2 I* -.(0(+(! 0(+(! DIFFERENTIATED SELECTIVIT AND CNS PROFILES N R 21.2 /,#(1* "' ++$) IC50 280 +M 0.40 >10 5M 0.024 0

Slide 65: Ongoing avapritinib clinical trials
Ongoing a apritinib clinical trials AVAPRITINIB AVAPRITINIB AVAPRITINIB 65 Mast cell disorders Mast cell actiation s#ndrome Hereditar# alpha tr#ptasemia Seere mast cell mediated asthma Se ere anaph#la"is Indolent SM Indolent SM Smoldering SM Adanced SM Aggressie SM SM !ith an associated hematologic
Slide 66: Planned BLU-263 clinical trials
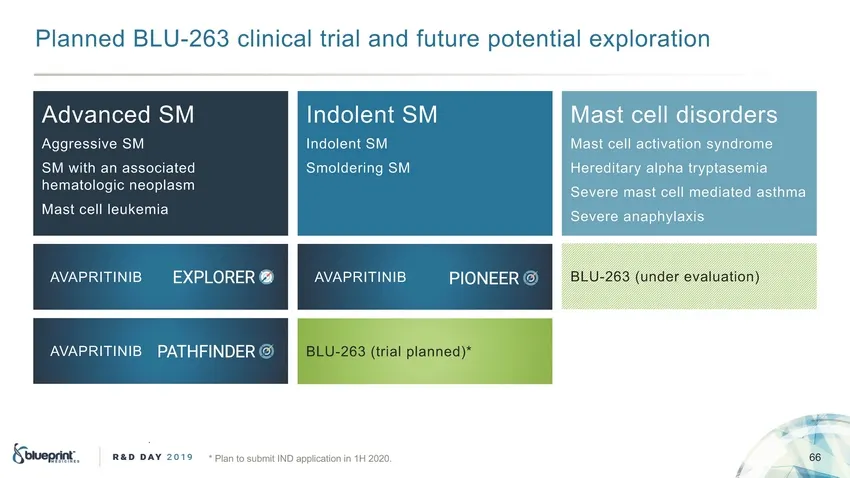
P$a&&ed BLU-263 c$"&"ca$ +)"a$ a&d f,+,)e ('+e&+"a$ e/($')a+"'& BLU-263 (,&de) e-a$,a+"'&) AVAPRITINIB AVAPRITINIB AVAPRITINIB BLU-263 (+)"a$ ($a&&ed)* 66 * P$a& +' *,b%"+ IND a(($"ca+"'& "& 1H 2020 Ma*+ ce$$ d"*')de)* Ma*+ ce$$ ac+"-a+"'& *0&d)'%e He)ed"+a)0 a$(!a +)0(+a*e%"a Se-e)e %a*+ ce$$ %ed"a

Slide 67: Q & A
Q & A

Slide 68: Break
b r e a k

Slide 69: A prolific platform for precision medicine
A prolific platform for precision medicine MARION DORSCH, PhD Chief Scientific Officer
Slide 70: Cancer is a genetic disease that evolves
Cancer is a genetic disease that evolves and becomes more elusive Cancer is a disease driven b enomic a errations Cancer evolves over time with new molecular chan es Tumors and their microenvironments are inherentlb complex 70

Slide 71: Blueprint Medicines built to tackle challenges of treating cancer
Bl&e"#i % Medici e$ i$ b&il% %! %ackle %he challe ge$ !f %#ea%i g ca ce# TRANSFORMATIVE BENEFIT URGENCY EFFICIENCY 71 * Re$ea#ch "!#%f!li! d#i'e b) "#!g#am$ (i%h high probability of success * Early go/no-go decisions (i%h a ga%ed, da%a-d#i'e !"e#a%ig m!del * S%#eamlied di$c!'e#) a""#!ach e abled b)
Slide 72: Proprietary library enables targeted kinase inhibitor design
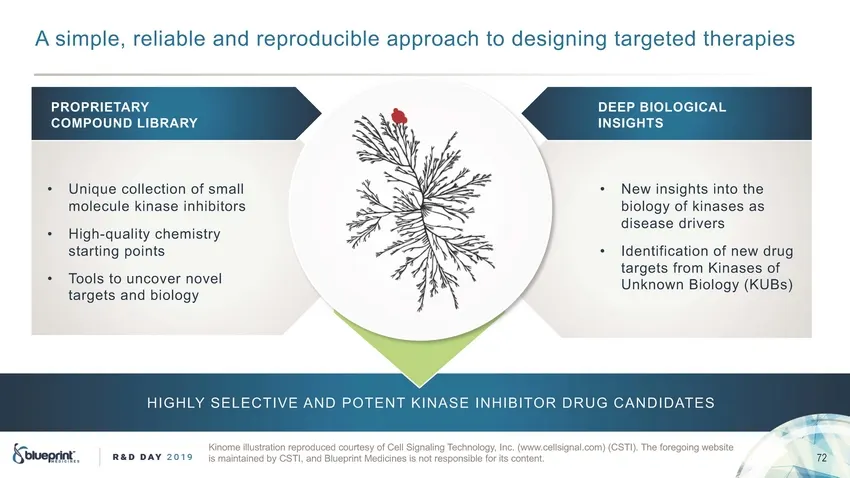
A ,#&)%e, +e%#ab%e a'd +e)+(d.c#b%e a))+(ac" -( de,#!'#'! -a+!e-ed -"e+a)#e, 2 U'#*.e c(%%ec-#(' ( ,&a%% &(%ec.%e $#'a,e #'"#b#-(+, H#!"-*.a%#-1 c"e&#,-+1 ,-a+-#'! )(#'-, T((%, -( .'c(/e+ '(/e% -a+!e-, a'd b#(%(!1 2 Ne0 #',#!"-, #'-( -"e b#(%(!1 ( $#'a,e, a, d#,ea,e d+#/e+, Ide'-# #ca-#(' ( 'e0 d+.!
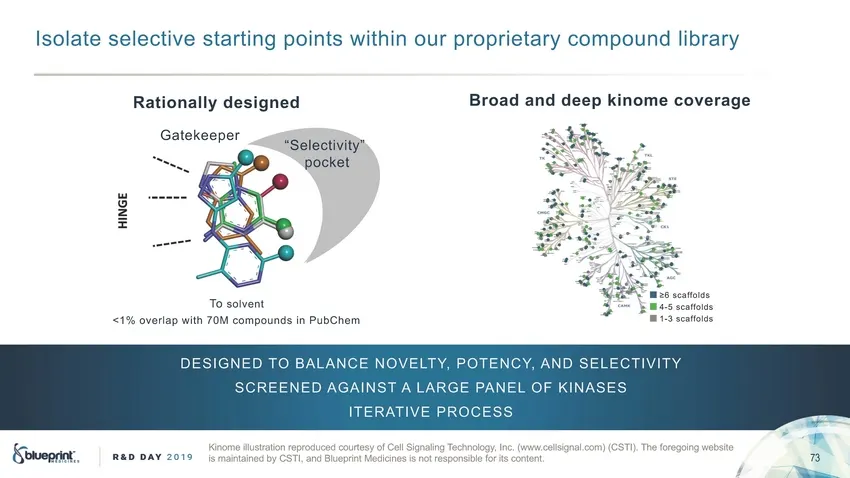
Slide 73: Kinase selectivity screening and design
I30-#4' 3'-'%4+6' 34#24+/) 10+/43 7+4*+/ 052 12012+'4#28 %0.105/& -+$2#28 Broad and deep kinome coverage Rationally designed GG##4','''11''12'2 :S'-'%4+6+48; 10%,'4 96 3%#(( 0-&3 4-5 3%#(( 0-&3 1-3 3%#(( 0-&3 0 30-6'/4 <1% 06'2-#1 7+4* ?OM %0.105/&3 +/ P5$C*'. DESIGNED O BALANCE NO!EL ", PO ENC ", A
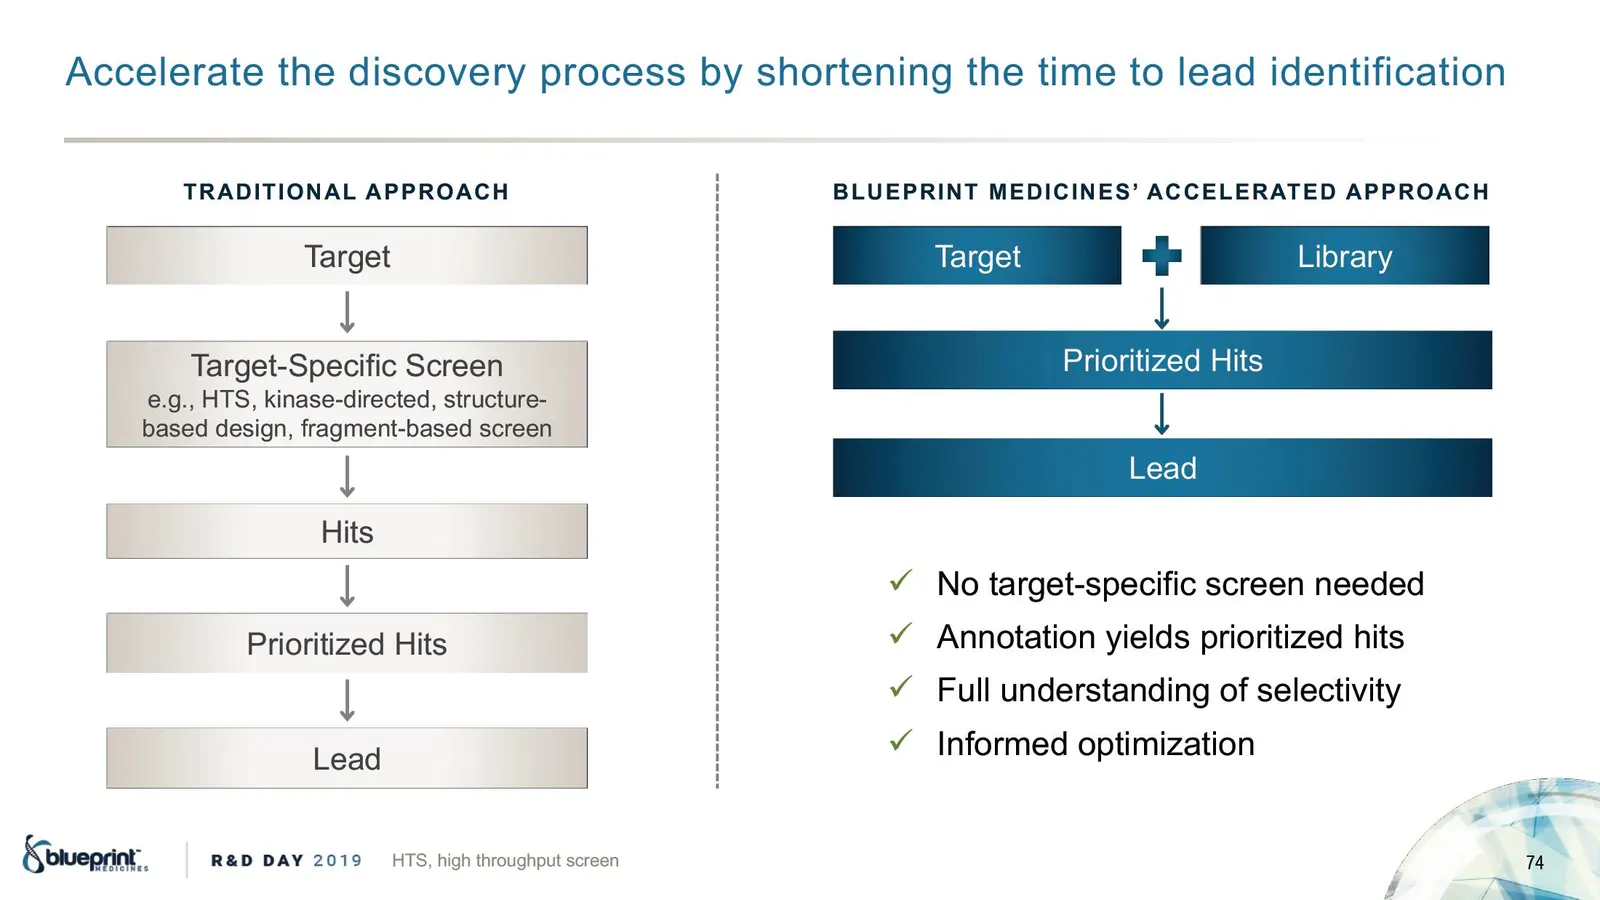
Slide 74: Accelerate discovery by shortening time to lead identification
Accelerate the disco!er" process b" shortening the time to lead identification TRADI TI O NAL A PPRO ACH BLUEPRI N T MEDI CI NES ' ACCELER ATED APPRO ACH Target Target Librar" Prioriti#ed Hits Target-Specific Screen e g , HTS, kinase-directed, str ct re-based design, fragment-based screen Lead Hits
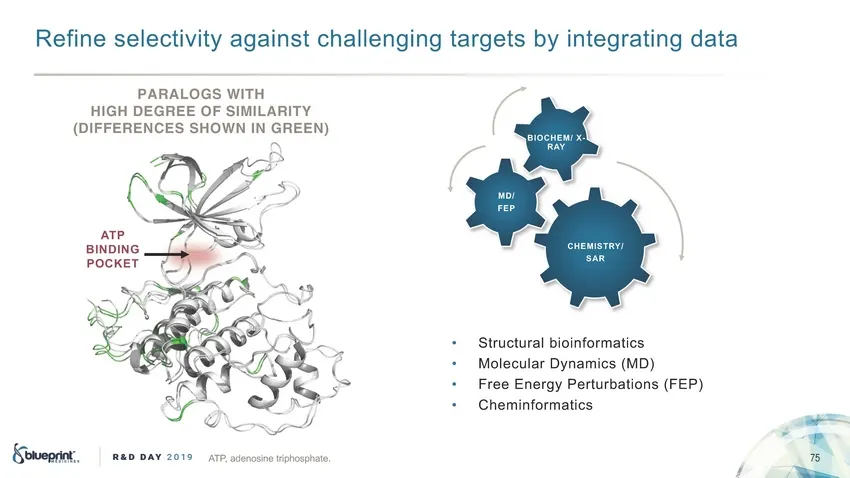
Slide 75: Refine selectivity against challenging targets
Ref ne selec " # aga ns challeng ng arge s b# n egra ng da a PARALOGS WITH HIGH DEGREE OF SIMILARITY (DIFFERENCES SHOWN IN GREEN) BIOCHEM/ X-R AY MD/ FE P ATP BINDING POCKET $ $ $ $ S r!c !ral b o nforma cs Molec!lar D#nam cs (MD) Free Energ# Per !rba ons (FEP) Chem nforma cs 75 ATP, adenos ne r pho
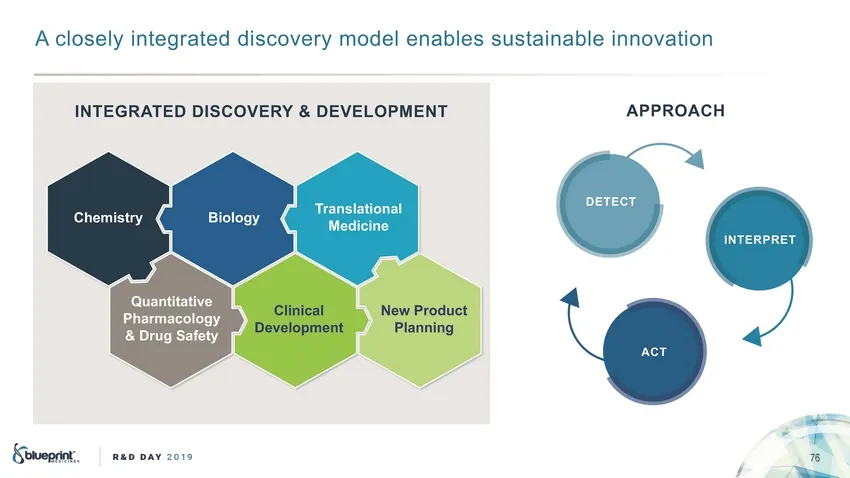
Slide 76: Closely integrated discovery model
A closely integrated discovery model enables sustainable innovation APPROACH DETECT INTERPRET ACT 76 INTEGRATED DISCOVERY & DEVELOPMENT Cli ical Ne( P#!d&c% De'el!"me%Pla i 9
Slide 77: Cancer is a genetic disease that evolves
Cancer is a genetic disease that evolves and becomes more elusive Cancer is a disease driven b enomic a errations Cancer evolves over time with new molecular chan es Tumors and their microenvironments are inherentlb complex 77
Slide 78: Rapidly drug targets in early clinical studies
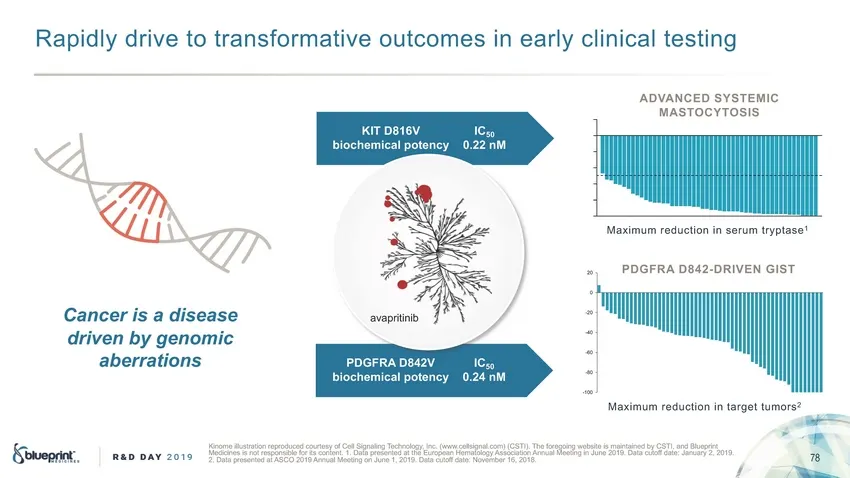
Ra)$d%1 d*$. ,( ,*a'+!(*&a,$. (-,c(& + $' a*%1 c%$'$ca% , +,$'" ADVANCED SYSTEMIC MASTOCYTOSIS KIT D816V e#!ca" &%'e$c( ICS0 0.22 $M b!%c Ma0$&-& * d-c,$(' $' + *-& ,*1),a+ 1 PDGFRA D842-DRIVEN IST Cancer is a disease driven by genomic aberrations a.a)*$,$'$b PDGFRA D842V b!%ce#!ca" &%'e$c( ICS0 0.2
Slide 79: Leverage clinical insights to enable next-generation inhibitors
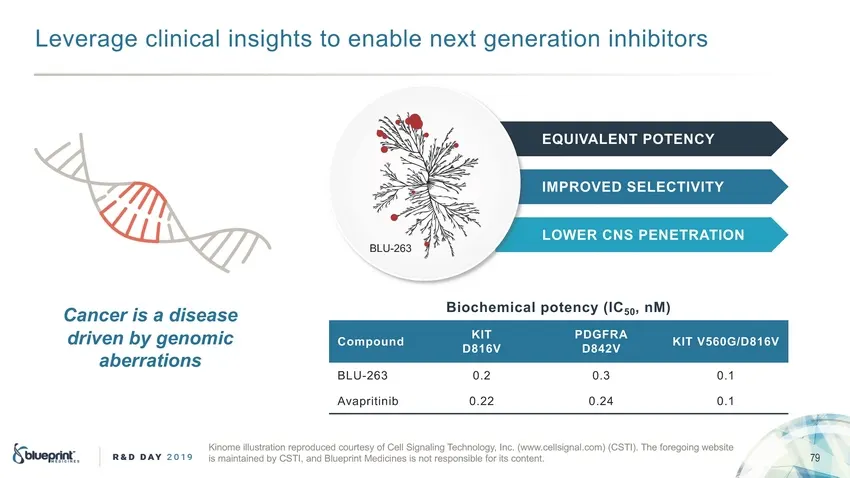
Le)e%age c i"ica i"&igh'& '# e"ab e "e+' ge"e%a'i#" i"hibi'#%& EQUI ALENT POTENC" IMPRO ED SELECTI IT" LO!ER CNS PENETRATION BLU-263 B(,$'&*($#) -,.&+$0 (IC50, +M) Cancer is a disease driven by genomic aberrations D816 D842 BLU-263 0.2 0.3 0.1 A)a$%i'i"ib 0.22 0.24 0.1 Ki"#!e i (&'%a'i#" %e$%#d(ced
Slide 80: Predict and prevent resistance prospectively
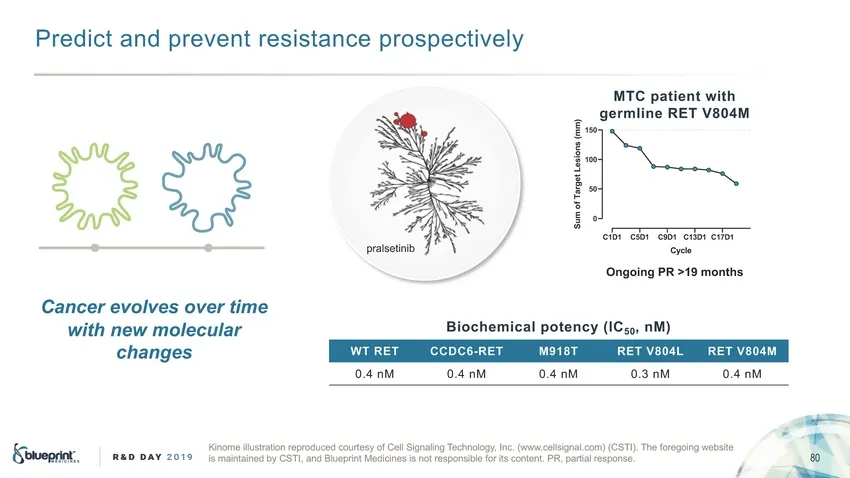
P edic" and p e$en" e!i!"ance p o!pec"i$el& MTC %a( e#( ) (h ge&"! #e RET V804M 150 100 50 0 C1D1 C5D1 C9D1 C13D1 C17D1 Cycle p al!e"inib O#g$ #g PR >19 "$#(h' Cancer evolves over time with new molecular changes 8 $che" ca! %$(e#c* (ICS0, #M) WT RET CCDC6-RET M918T RET V804L RET V804M 0.4 nM 0.4 nM
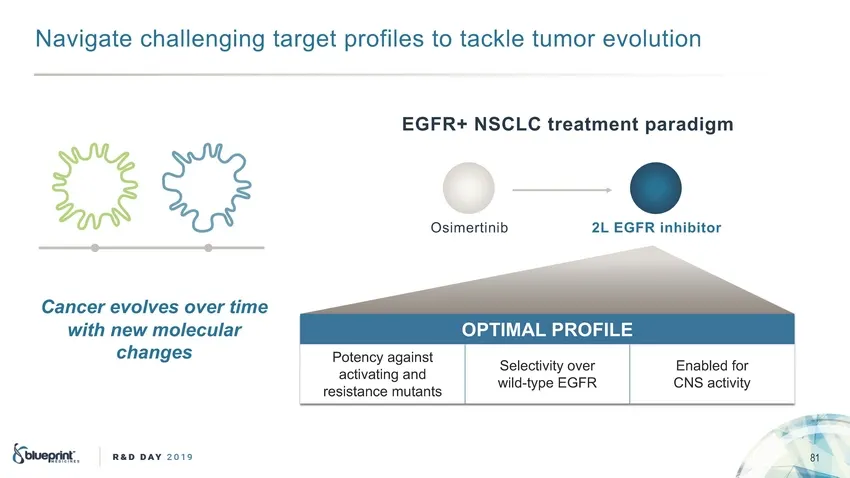
Slide 81: Navigate challenging target profiles to tackle tumor evolution
Navigate challenging target profiles to tackle tumor evolution EGFR+ NSCLC treatment paradigm Osimertinib 2L EGFR inhibitor Cancer evolves over time with new molecular changes CNS activit! 81 OPTIMAL PROFILE Potenc! against activating and resistance mutants Selectivit! over ild-t!pe EGFR Enabled for
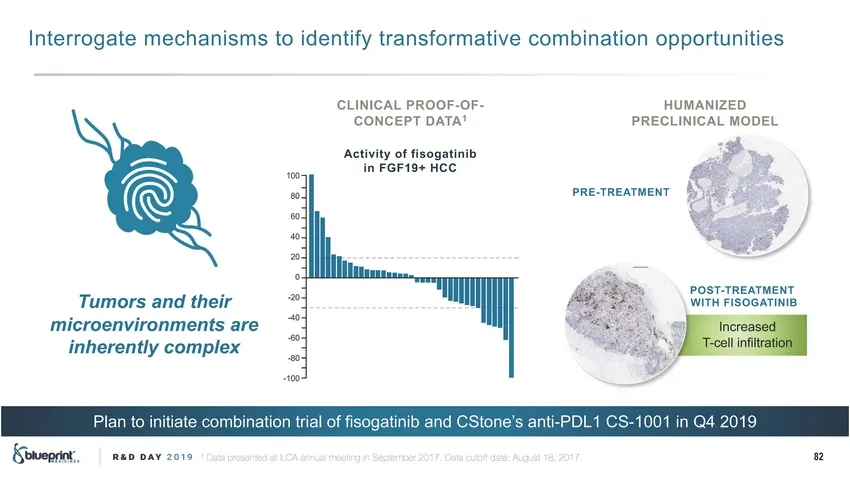
Slide 82: Interrogate mechanisms to identify combination opportunities
ln"e oga"e mechani!m! "o iden"if% " an!fo ma"i$e combina"ion oppo "#ni"ie! CLINICAL PROOF-OF-CONCEPT DATA1 HUMANIZED PRECLINICAL MODEL Ac#i$i#% !f fi"!ga#i ib i FGF19+ HCC 100 PRE-TREATMENT 80 60 40 20 0 POST-TREATMENT WITH FISOGATINIB Tumors and their microenvironments are inherently complex -20 -4
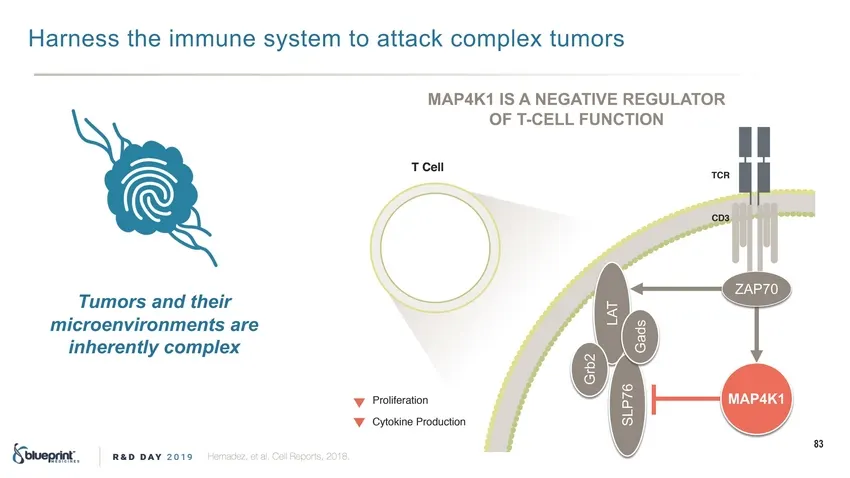
Slide 83: Harness immune system to attack complex tumors
Harness the immune s stem to attack complex tumors MAP4K1 IS A NEGATIVE REGULATOR OF T-CELL FUNCTION ZAP?O Tumors and their microenvironments are inherently complex MAP4K1 83 Hernadez, et al. Cell Reports, 2018. Grb2 Gads

Slide 84: Blueprint Medicines built to tackle challenges of treating cancer
Bl&e"#i % Medici e$ i$ b&il% %! %ackle %he challe ge$ !f %#ea%i g ca ce# TRANSFORMATIVE BENEFIT URGENCY EFFICIENCY 84 * Re$ea#ch "!#%f!li! d#i'e b) "#!g#am$ (i%h high probability of success * Early go/no-go decisions (i%h a ga%ed, da%a-d#i'e !"e#a%ig m!del * S%#eamlied di$c!'e#) a""#!ach e abled b)

Slide 85: Continued productivity: planned research milestones in 1H 2020
Cont nued product v ty: planned research m lestones n 1H 2020 85

Slide 86: [LOGO]
[LOGO]

Slide 87: Addressing tumor evolution in lung cancer
Addressing tumor evolution in lung cancer TIM GUZI, PhD Senior Vice President, Chemistry L.O. v ng w th NSCLC
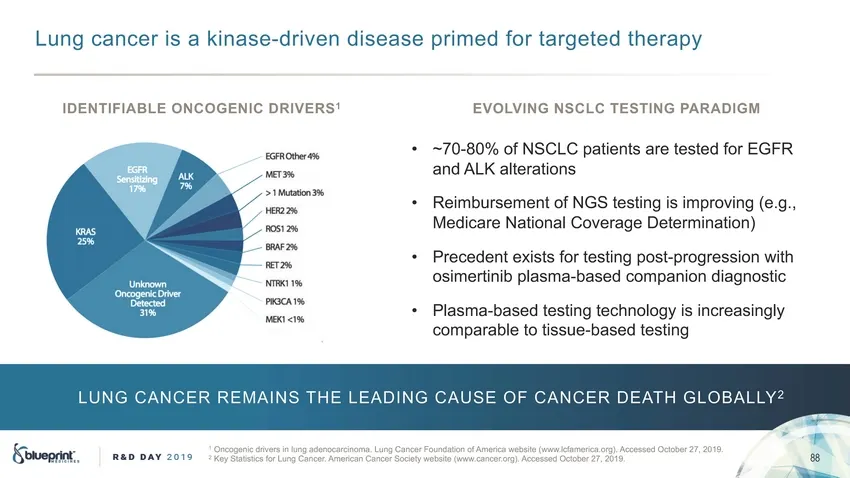
Slide 88: Lung cancer is a molecularly driven disease
L4.( $".$&1 *2 " +*."2&-%1*5&. %*2&"2& 01*-&% '/1 3"1(&3&% 3)&1"08 IDENTIFIABLE ONCOGENIC DRIVERS1 EVOLVING NSCLC TESTING PARADIGM : 970-80% /' NSCLC 0"3*&.32 "1& 3&23&% '/1 EGFR ".% ALK ",3&1"3*/.2 : R&*-#412&-&.3 /' NGS 3&23*.( *2 *-01/5*.( (&.(., M&%*$"1& N"3*/.", C/5&1"(& D&3&1-*."3*/.) : P1&$&%
Slide 89: Tumor evolution and three approaches for durable benefit
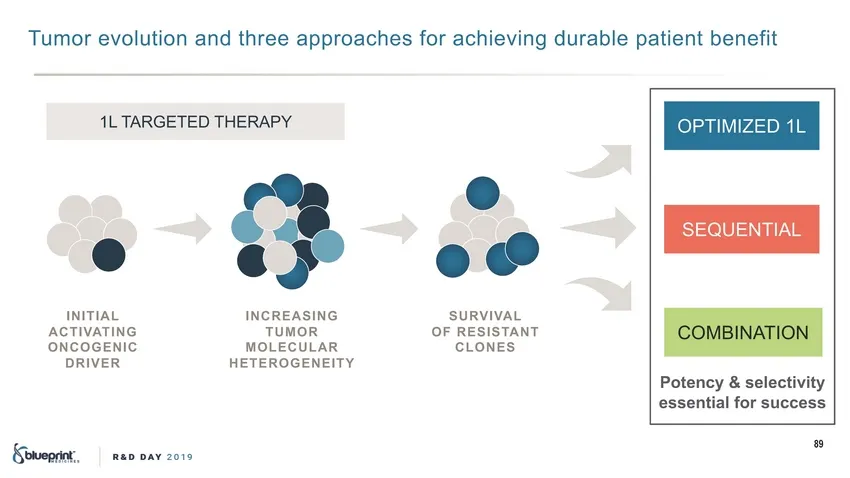
T(!#% e)# ('i#" a"d 'h%ee a$$%#ache& f#% achie)i"g d(%ab e $a'ie"' be"efi' INITIAL ACTI VAT ING ONCOGENIC DRIVER INCREASING TUMOR MOLECULAR HETEROGENEITY SUR V I VAL OF RESIS TANT CLONES 89 1L TARGETED THERAPY Po enc# & selec i"i # essen ial for s!ccess COMBINATION SEQUENTIAL OPTIMIZED 1L
Slide 90: Closely integrated discovery model
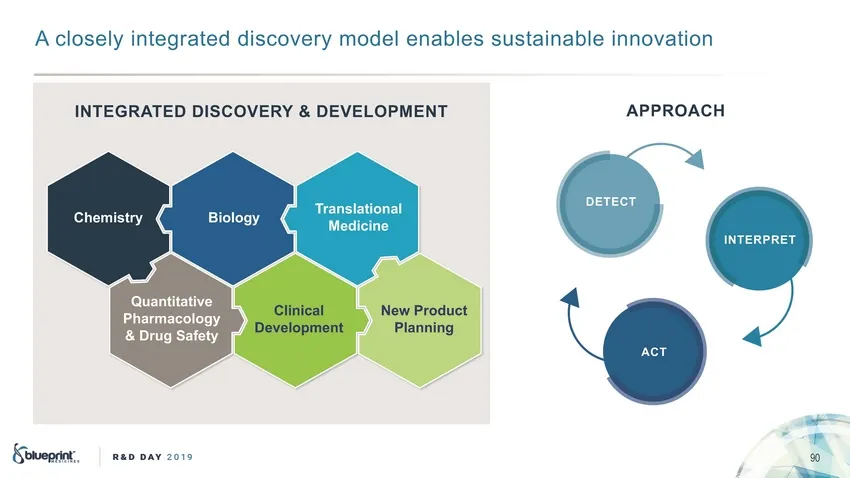
A closely integrated discovery model enables sustainable innovation APPROACH DETECT INTERPRET ACT 90 INTEGRATED DISCOVERY & DEVELOPMENT Cli ical Ne( P#!d&c% De'el!"me%Pla i 9
Slide 91: NSCLC patients with RET fusions have no highly effective treatment options
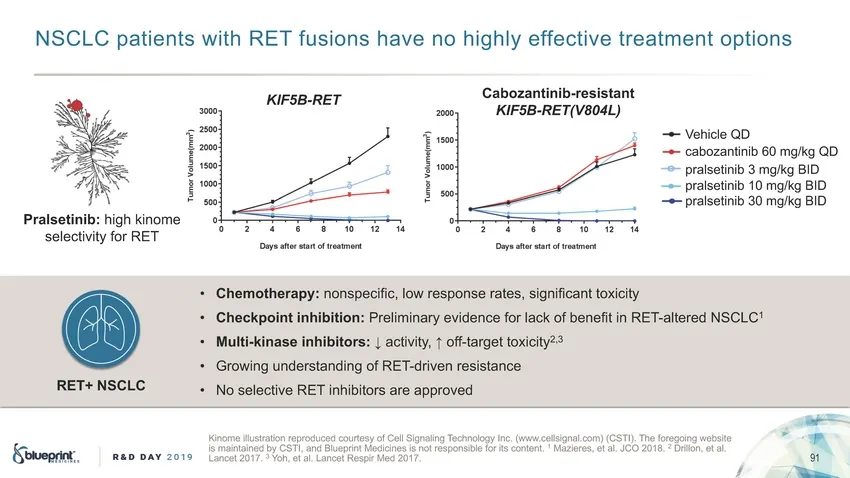
NSCLC 0"3*&.32 6*3) RET '42*/.2 )"5& ./ )*(),8 &''&$3*5& 31&"3-&.3 /03*/.2 Cabozantinib-resistant KIF58-RET(V804L) KIF58-RET &)*$,& QD $"#/9".3*.*# 60 -(/+( QD 01",2&3*.*# 01",2&3*.*# 01",2&3*.*# 3 -(/+( BID 10 -(/+( BID 30 -(/+( BID Pralsetinib: )*() +*./-& 2&,&$3*5*38 '/1 RET : : : : : Chemotherap
Slide 92: Promising data supporting pralsetinib in RET+ NSCLC
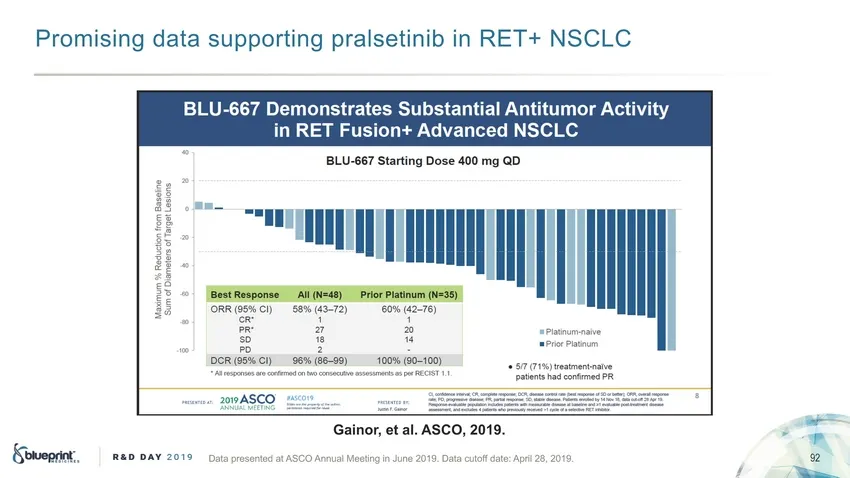
P%#!i&i"g da'a &($$#%'i"g $%a &e'i"ib i" RET+ NSCLC Gainor, et al. ASCO, 2019. 92 Da'a $%e&e"'ed a' ASCO A""(a Mee'i"g i" J("e 2019. Da'a c('#ff da'e: A$%i 28, 2019.
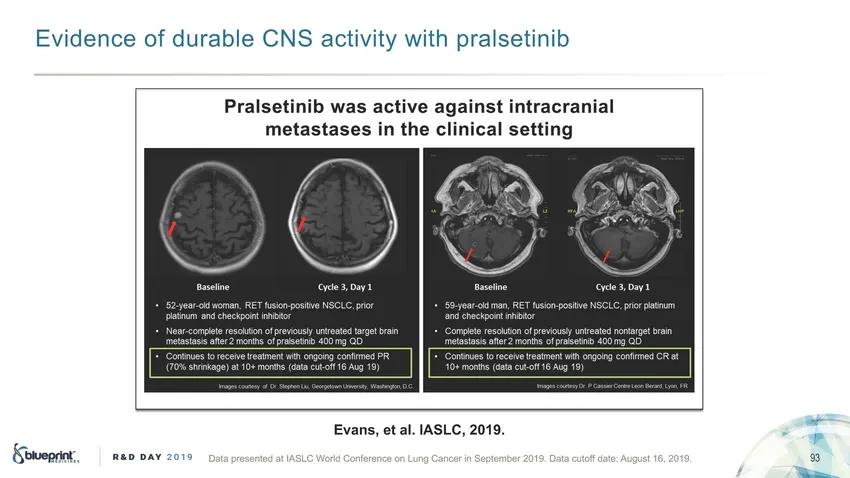
Slide 93: Evidence of durable CNS activity with pralsetinib
E%idence of d$!able CNS ac#i%i#' &i#h !al"e#inib Evans, et al. IASLC, 2019. 93 Da#a !e"en#ed a# IASLC Wo!ld Confe!ence on L$ng Cance! in Se #embe! 2019. Da#a c$#off da#e: A$g$"# 16, 2019.
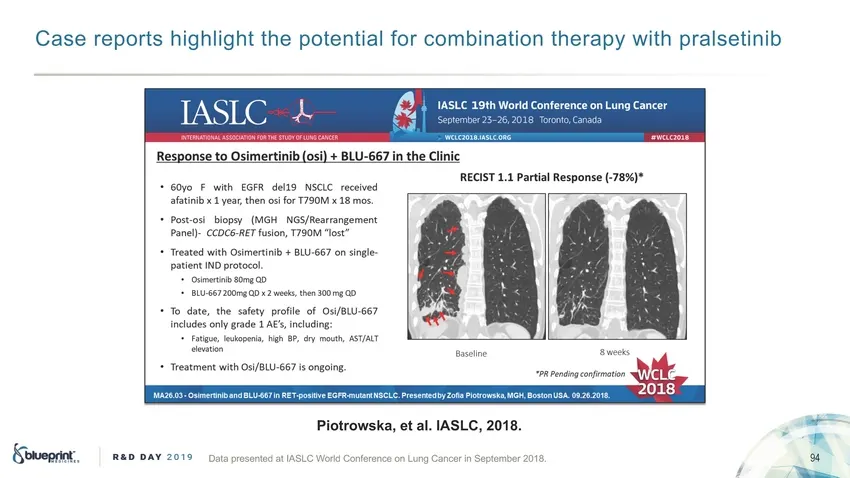
Slide 94: Case reports highlight combination potential with pralsetinib
Case reports h gh ght the potent a for comb nat on therap! th pra set n b Piotrowska, et al. IASLC, 2018. 94 Data presented at IASLC Wor d Conference on Lung Cancer n September 2018.
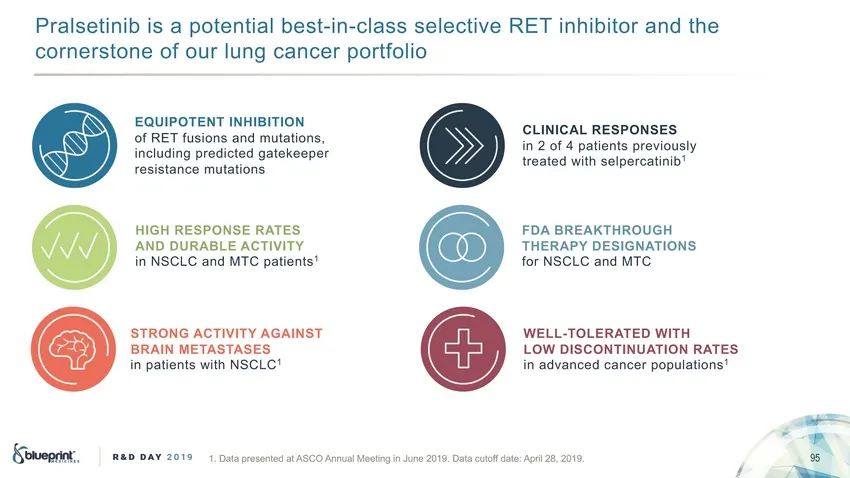
Slide 95: Pralsetinib: potential best-in-class selective RET inhibitor
P(a#)e*!%!b !) a '&*e%*!a# be)*-!%-c#a)) )e#ec*!,e RET !% c&(%e()*&%e &f &+( #+%g ca%ce( '&(*f&#!& !b!*&( a%d * e EQUIPOTENT INHIBITION &f RET f+)!&%) a%d $+*a*!&%), !%c#+d!%g '(ed!c*ed ga*e"ee'e( (e)!)*a%ce $+*a*!&%) CLINICAL RESPONSES !% 2 &f 4 'a*!e%*) '(e,!&+)#. 1 *(ea*ed -!* )e#'e(ca*!%!b HIGH
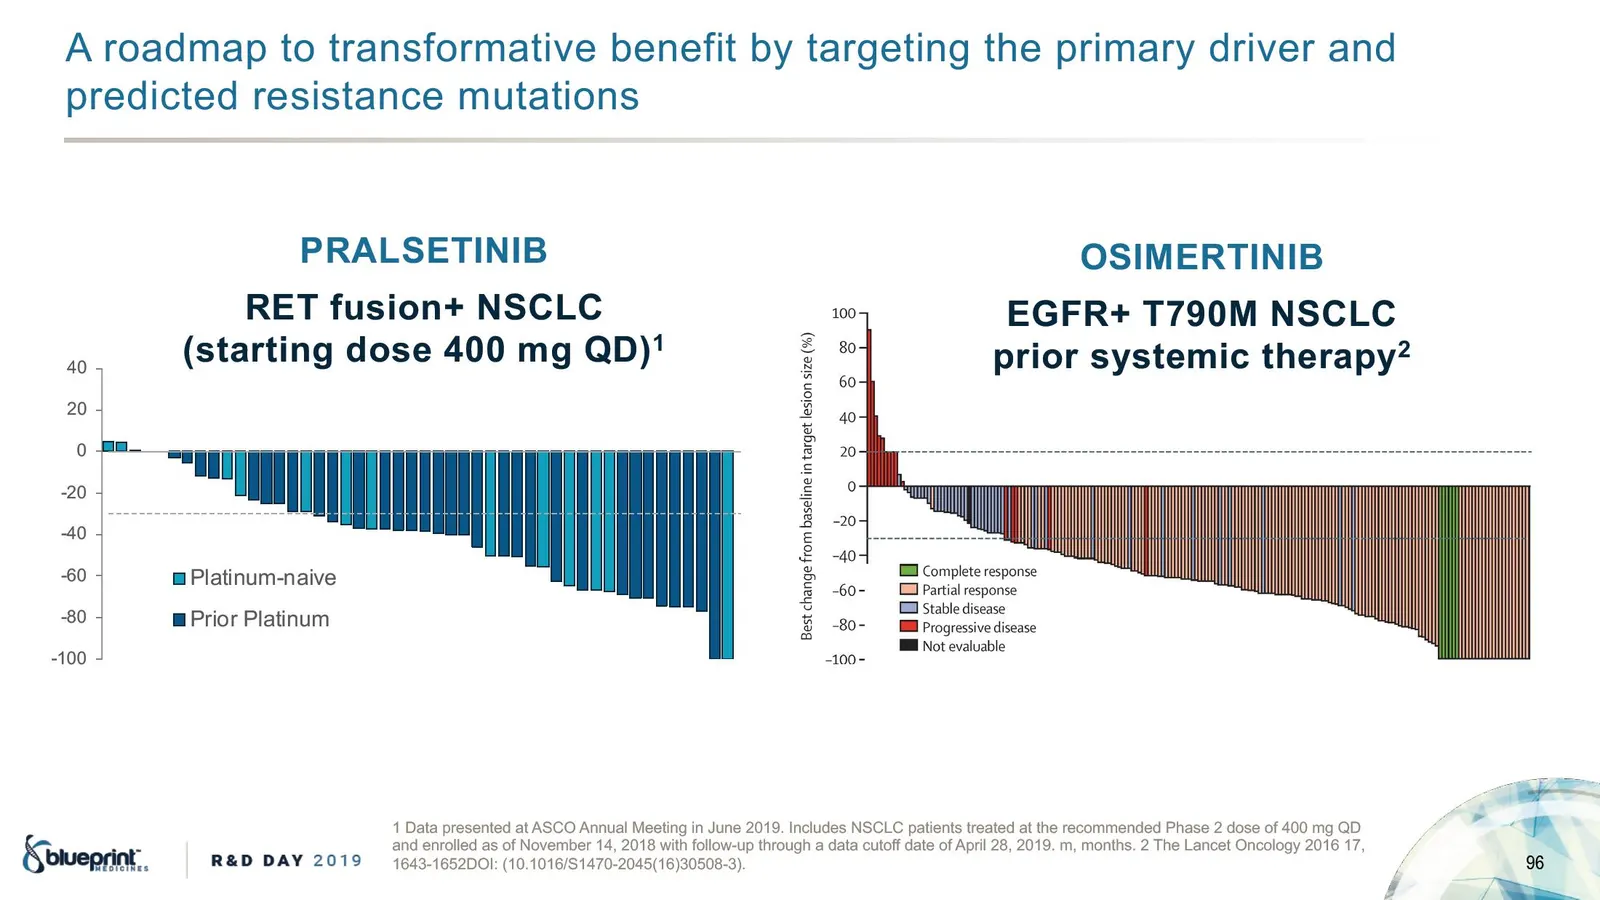
Slide 96: Pralsetinib response compared with prior therapies
A ., #* - 0, 0. +/%,.* +"$ *10 0(2$ !$+$%(0 !4 0 0(,+/ .&$0(+& 0'$ -.(* .4 #.(2$. +# -.$#("0$# .$/(/0 PRALSETINIB RET +)#&%+ NSCLC ()*a(*#%! d&)e 400 $! QD) OSIMERTINIB EGFR+ T790M NSCLC '(#&( ),)*e$#c *"e(a',2 1 40 20 0 -20 -40 -60 P) 0(+1*-+(2$ -80 -100 1 D 0 -.$/$+0$# 0 ASCO A++1 ) M$$0(+& (+ J1+

Slide 97: EGFR resistance mutations following osimertinib
E& *"$'" da,a +#(-)(, ',$a% * a,& +$+,a'c )*(!$% + !(%%(-$'" !$*+,-%$' a'd + c('d-%$' (+$& *,$'$b ,* ', $' EGFR+ NSCLC + C797S + T790M a'd C797S E.(' 19/L858R T790M C797S C797S EGFR+ CS TMCS ONCOGENIC DRIVER FOLLOWING 1L OSIMERTINIB FOLLOWING 2L OSIMERTINIB 98
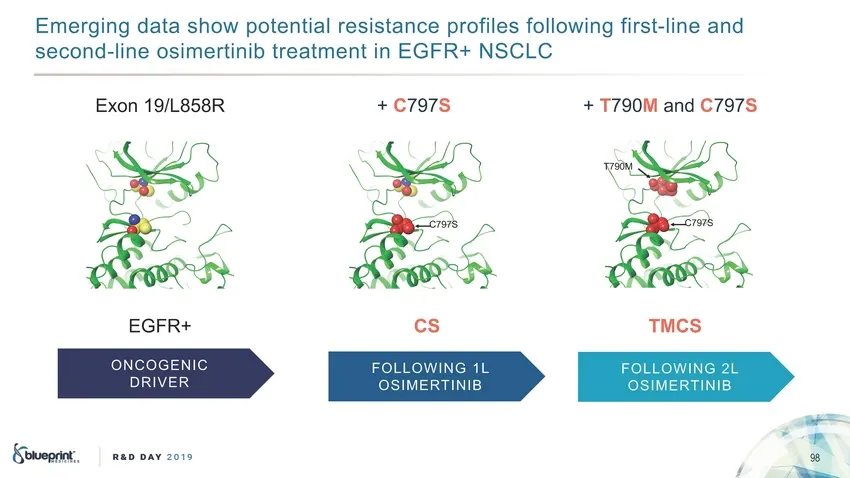
Slide 98: EGFR resistance mutations following osimertinib
E& *"$'" da,a +#(-)(, ',$a% * a,& +$+,a'c )*(!$% + !(%%(-$'" !$*+,-%$' a'd + c('d-%$' (+$& *,$'$b ,* ', $' EGFR+ NSCLC + C797S + T790M a'd C797S E.(' 19/L858R T790M C797S C797S EGFR+ CS TMCS ONCOGENIC DRIVER FOLLOWING 1L OSIMERTINIB FOLLOWING 2L OSIMERTINIB 98
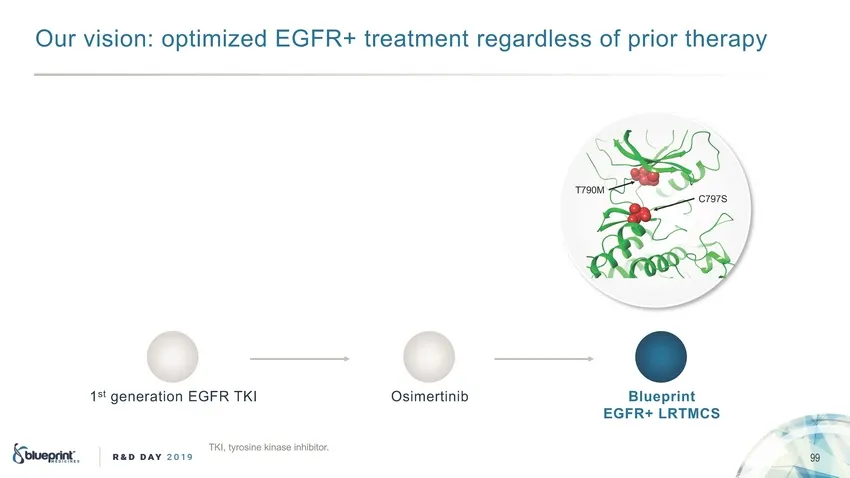
Slide 99: Optimized EGFR+ treatment regardless of prior therapy
O&# ' $ ! : !"% m )ed EGFR+ %#ea%me % #ega#d e$$ !f "# !# %he#a"( T790M C797S 1$% ge e#a% ! EGFR TKI O$ me#% b Blueprint EGFR+ LRTMCS TKI, %(#!$ e k a$e h b %!#. 99
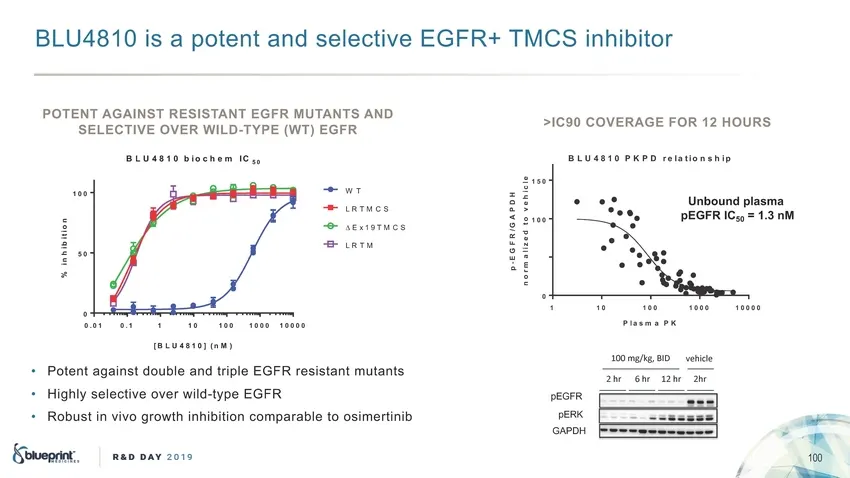
Slide 100: BLU4810 potent and selective EGFR+ TMCS inhibitor
BLU4810 i& a $#'e"' a"d &e ec'i)e EGFR+ TMCS i"hibi'#% POTENT AGAINST RESISTANT EGFR MUTANTS AND >IC90 COVERAGE FOR 12 HOURS SELECTIVE OVER ILD-T!PE ( T) EGFR B L U 4 8 1 0 b i o c h e m I C 50 8 L U 4 8 1 0 P K P D e l a " i o n ! h i p 150 W T 100 %"*&" = 1.3 'M L R T M C S 100 Δ E X 1 9 T M C S L
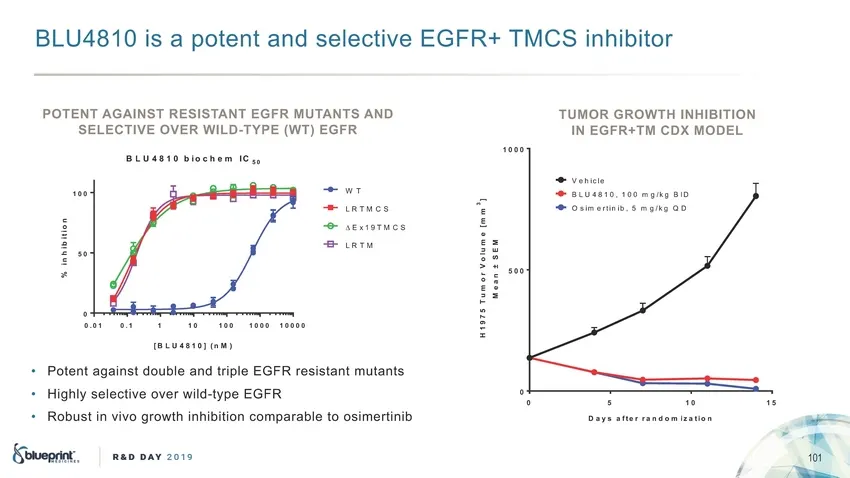
Slide 101: BLU4810 potent and selective EGFR+ TMCS inhibitor
BLU4810 # a ! $en$ and #elec$ &e EGFR+ TMCS nh b $ " POTENT AGAINST RESISTANT EGFR MUTANTS AND SELECTIVE OVER WILD-TYPE (WT) EGFR TUMOR GROWTH INHIBITION IN EGFR+TM CDX MODEL 1000 B L U 4 8 1 0 b i o c h e m I C 50 W T 100 L R T M C S Δ E X 1 9 T M C S L R T M 50 500 0 0. 01 0. 1 1 10 100 1 000 1000
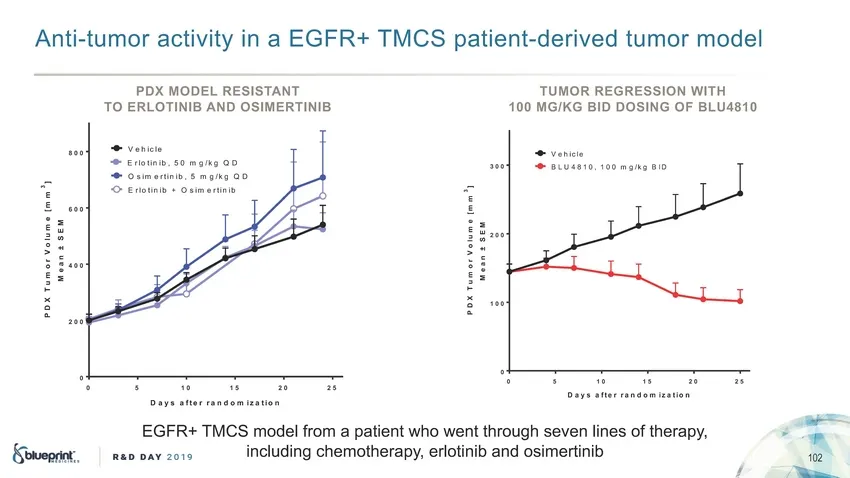
Slide 102: Anti-tumor activity in EGFR+ TMCS PDX model
Anti-tumor acti it" in a EGFR+ TMCS patient-deri ed tumor model PDX MODEL RESISTANT TO ERLOTINIB AND OSIMERTINIB TUMOR REGRESSION WITH 1OO MG/KG BID DOSING OF BLU481O B 0 0 3 0 0 0 0 2 0 0 4 0 0 1 0 0 2 0 0 0 0 0 5 1 0 1 5 2 0 2 5 0 5 1 0 1 5 2 0 2 5 D a y s a f t e r r a n d o m i z a t i o n D a !
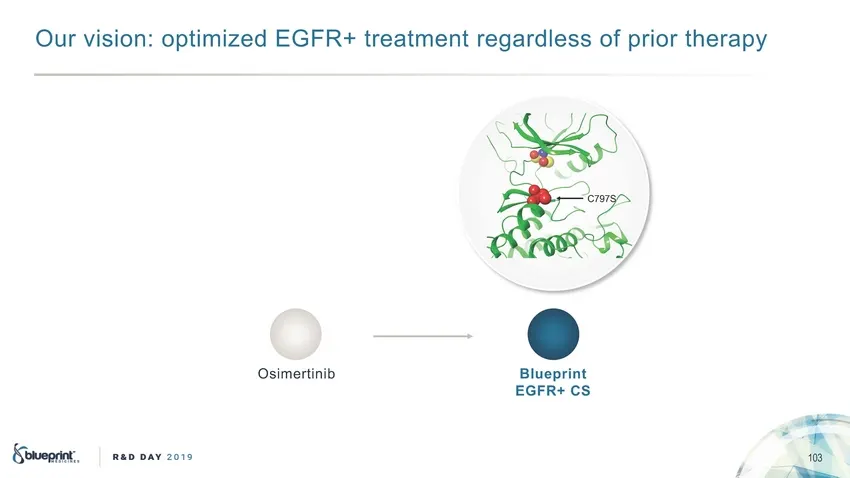
Slide 103: Our vision: optimized EGFR+ treatment
Our vision: optimi ed EGFR+ treatment regardless of prior therapy C797S Osimertinib Blueprint EGFR+ CS 103
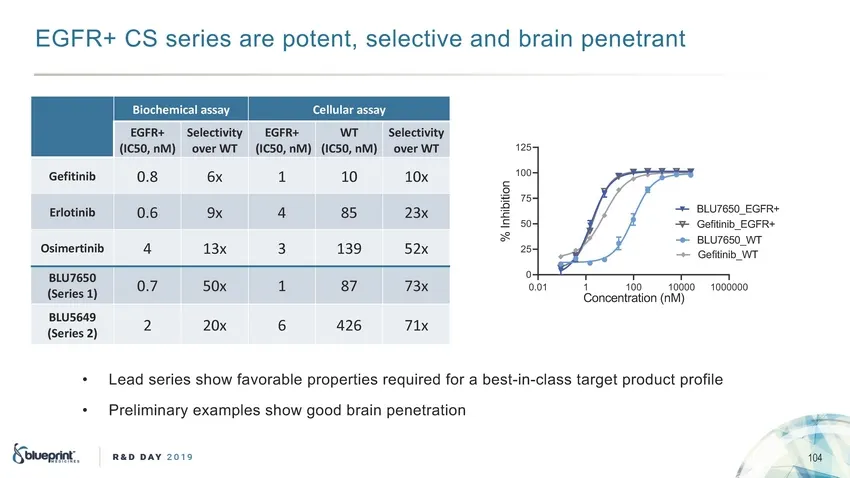
Slide 104: EGFR+ CS series potent, selective and brain penetrant
EGFR+ CS series are potent, selecti e and brain penetrant 125 100 75 7650 EGFR+ b EGFR+ 650 WT b WT 50 25 0 0.01 1 100 10000 1000000 C"!ce!$#a$ "! (!M) $ $ Lead series sho! fa orable properties required for a best-in-class target product profile Preliminar# e"amples sho! good brain penetration 104 %
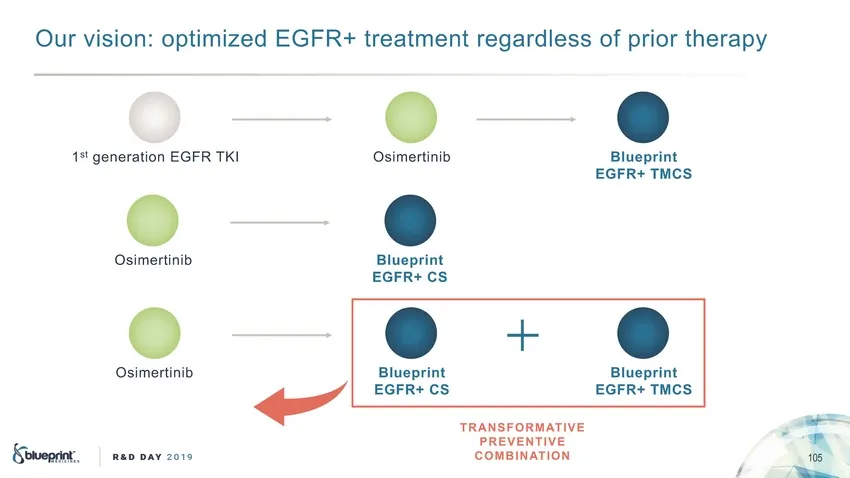
Slide 105: Our vision: optimized EGFR+ treatment
Our vision: optimi ed EGFR+ treatment regardless of prior therapy 1st generation EGFR TKI Osimertinib Blueprint EGFR+ TMCS Osimertinib Blueprint EGFR+ CS Osimertinib Blueprint EGFR+ CS Blueprint EGFR+ TMCS TRANSFO RM AT I V E PREVENTIVE C O MB IN AT ION 105
Slide 106: Delivering durable benefit to additional patient populations
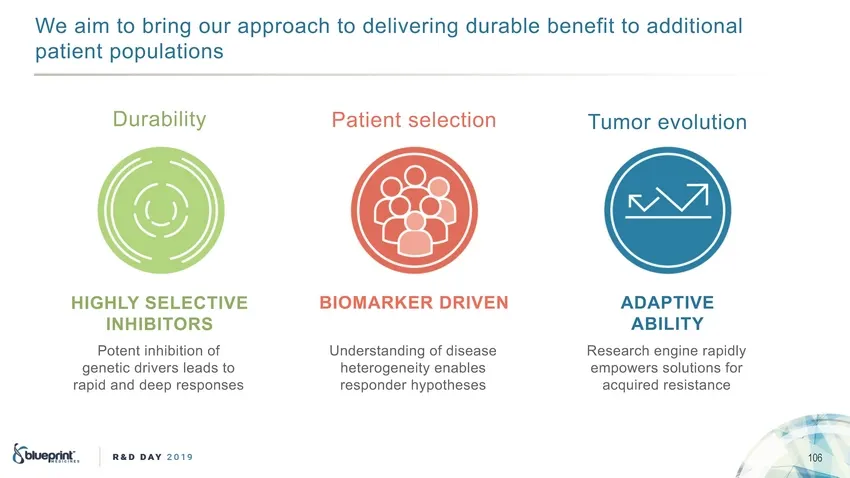
We aim to bring our approach to delivering durable benefit to additional patient populations Durability Patient selection Tumor evolution HIGHLY SELECTIVE INHIBITORS Potent inhibition of genetic drivers leads to rapid and deep responses BIOMARKER DRIVEN ADAPTIVE ABILITY Research engine rapidly empow

Slide 107: Cancer immunotherapy: a new frontier for kinase medicines
Cancer immunotherapy: a new frontier for kinase medicines KLAUS HOEFLICH, PhD Vi ce President, Biology
Slide 108: Impact of cancer immunotherapy
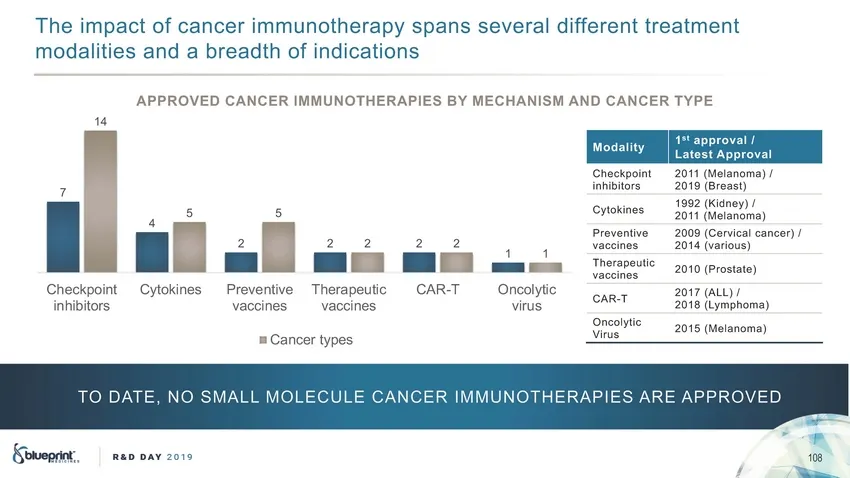
T'% (+.!#1 -& #!,#%/ (++2,-1'%/!.4 0.!,0 0%3%/!* $(&&%/%,1 1/%!1+%,1 +-$!*(1(%0 !,$ ! "/%!$1' -& (,$(#!1(-,0 APPROVED CANCER IMMUNOTHERAPIES BY MECHANISM AND CANCER TYPE 14 Latest Appro al ? 5 5 4 2 2 2 2 2 1 1 2010 (P/-01!1%) 3!##(,%0 C'%#).-(,1 (,'("(1-/0 C41-)(,%0 P/%3%,1(3% 3!##(,%0 T'%/!.%21(#
Slide 109: Kinase inhibition: new approach to anti-tumor immune response
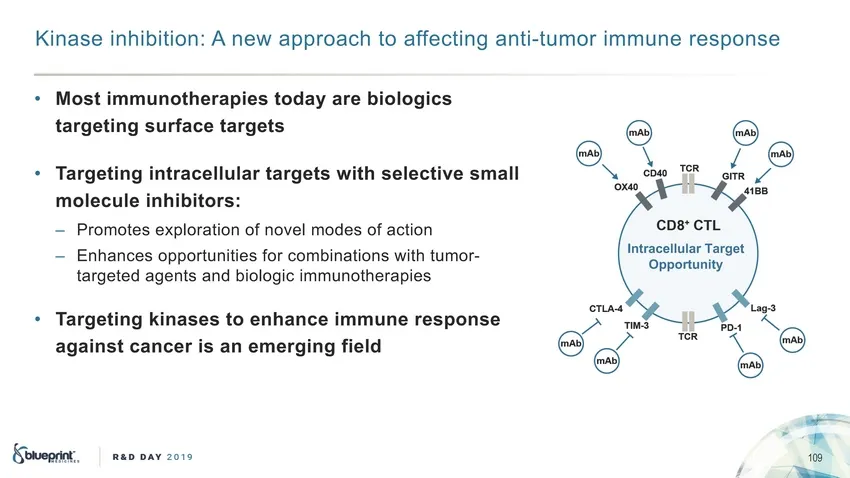
Kinase inhibition: A new approach to affecting anti-tumor immune response • Most immunotherapies today are biologics targeting surface targets • Targeting intracellular targets with selective small molecule inhibitors: - - Promotes exploration of novel modes of action Enhances opportunities for comb
Slide 110: Cancer immunotherapy complements precision medicine strategy
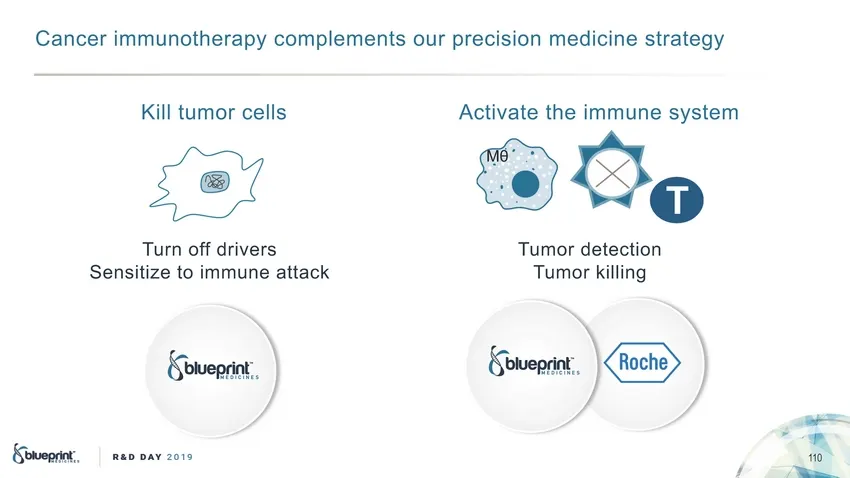
Cancer immunotherapy complements our precision medicine strategy Kill tumor cells Activate the immune system M8 Turn off drivers Sensitize to immune attack Tumor detection Tumor killing 110
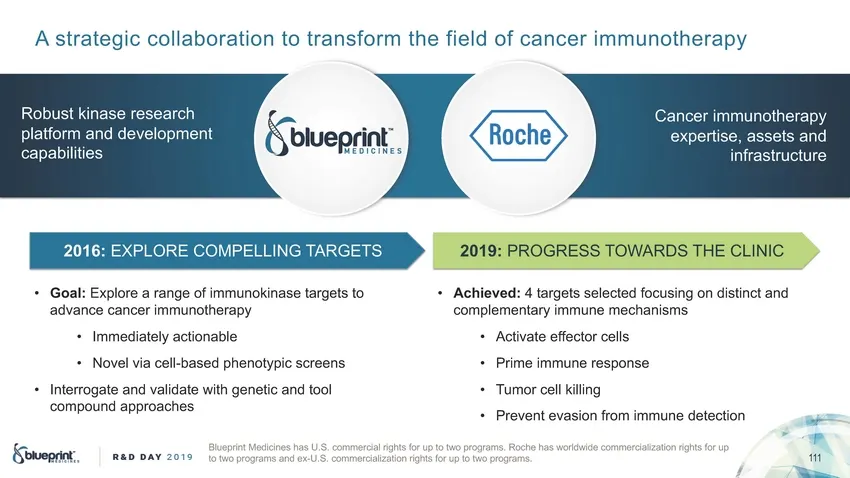
Slide 111: Strategic collaboration with Roche in cancer immunotherapy
A )*(a*eg!c c&##ab&(a*!&% *& *(a%)f&($ * e f!e#d &f ca%ce( !$$+%&* e(a'/ R&b+)* "!%a)e (e)ea(c Ca%ce( !$$+%&* e(a'/ '#a*f&($ a%d de,e#&'$e%* ca'ab!#!*!e) e.'e(*!)e, a))e*) a%d !%f(a)*(+c*+(e 2016: EXPLORE COMPELLING TARGETS 2019: PROGRESS TOWARDS THE CLINIC 1 Goal: E.'#&(e a (a%ge &f !$$+%&"!%a)e *a
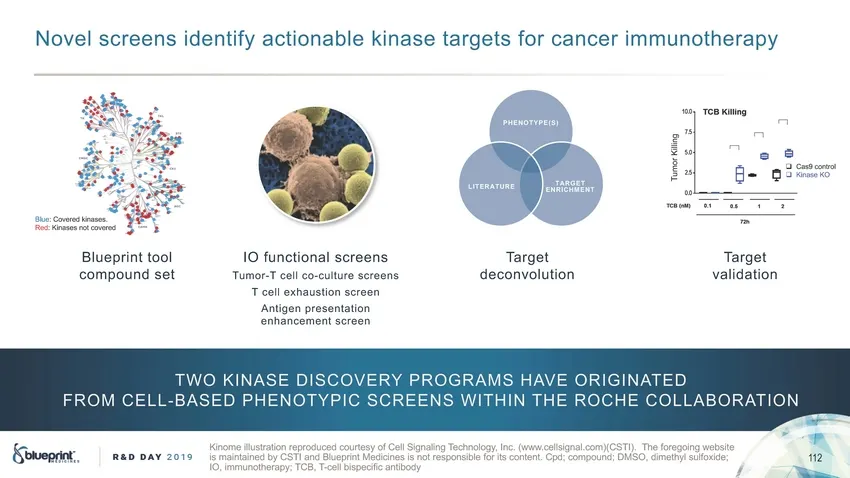
Slide 112: Novel kinase immunotherapy targets
N,2#) /!.##+/ '"#+0'$5 a!0',+a )# ('+a/# 0a.%#0/ $,. !a+!#. '**1+,0&#.a-5 0 Ca/9 !,+0.,) 0 K'+a/# KO LITERATURE B)1#: C,2#.#" ('+a/#/. R#": K'+a/#/ +,0 !,2#.#" B)1#-.'+0 0,,) !,*-,1+" /#0 IO $1+!0',+a) /!.##+/ T1*,.-T !#)) !,-!1)01.# /!.##+/ T !#)) #4&a1/0',+ /!.##+ A+0'%#+ -.#/#+0a0',+ #+&a+!#*#+0

Slide 113: Platform explores new kinase biology: MAP4K1
Our scientific platform enables us to e!plore ne kinase biolog", iNNO VATiON representing even larger opportunities to impact patient care immunokinase inhibitor 113 MAP4K1 is a collaboration target under the cancer immunotherap" collaboration ith Roche.
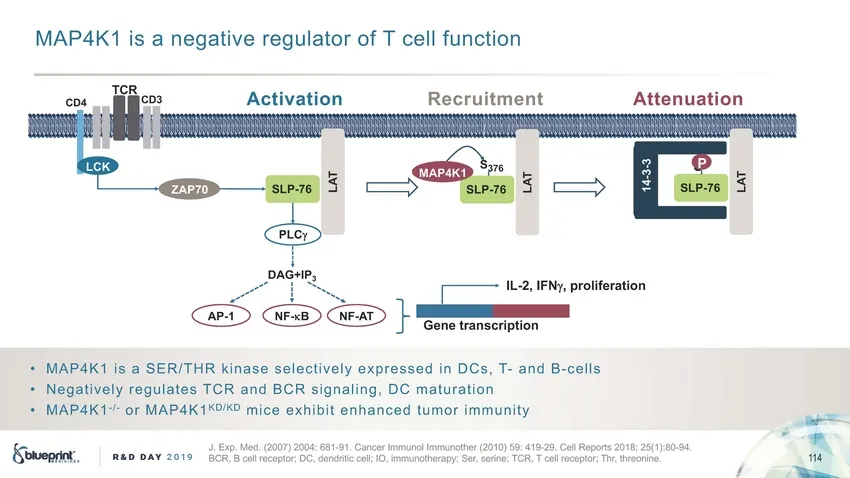
Slide 114: MAP4K1 is a negative regulator of T cell function
MAP4K1 +3 # /')#4+6' 2')5-#402 0( " %'--(5/%4+0/ TCR Ac( *a( $# Rec&) ("e#( A((e#)a( $# CD3 CD4 SP S376 LCK MAP4K1 SLP-76 SLP-76 ZAP70 SLP-76 PLCγ DAG+IP3 IL-2, IFNγ, %&$! fe&a( $# AP-1 NF-κB NF-AT Ge#e (&a#'c& %( $# 9 9 9 M AP4K1 +3 # !E /"H ,+/#3' 3'-'%4+6'-8 '712'33'& +/ DC3, "-#/& B-%'--3 N ')#4
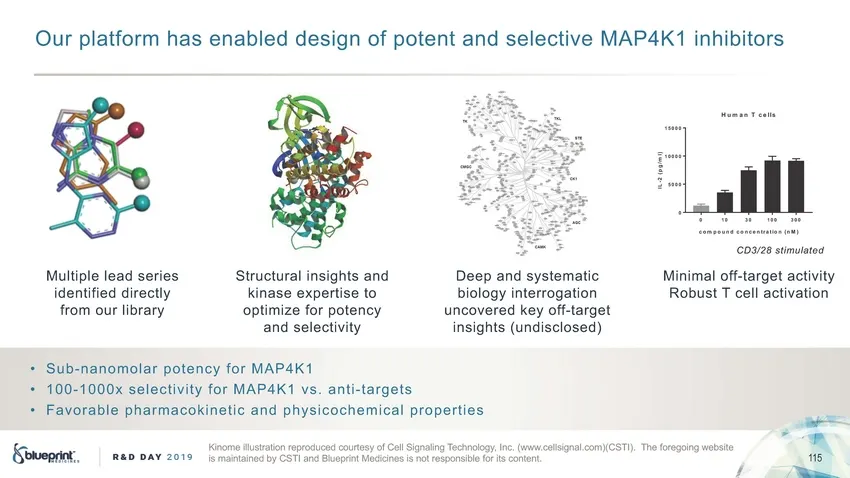
Slide 115: Platform enabled design of potent, selective MAP4K1 inhibitors
O)& %!a(f$&" ha' e#ab!ed de'ig# $f %$(e#( a#d 'e!ec(i*e MAP4K1 i#hibi($&' H u m a n T ceI I s 15000 10000 5000 0 0 1 0 3 0 100 300 c o m p ou n d c on c e nt r a t i on ( nM ) C03/28 stimulated M)!(i%!e !ead 'e&ie' ide#(ified di&ec(!-f&$" $)& !ib&a&-S(&)c()&a! i#'igh(' a#d i#a'e e,%e&(i'e ($ $%(i"i.
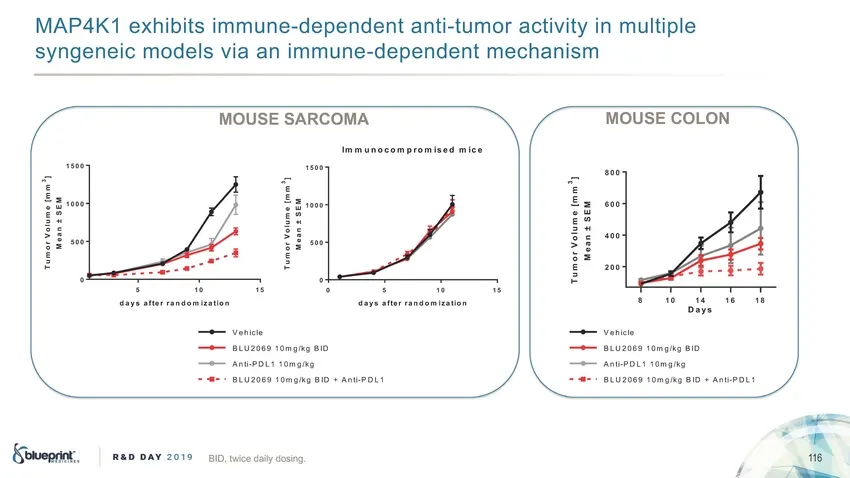
Slide 116: MAP4K1 immune-dependent anti-tumor activity in syngeneic models
MAP4K1 e!hibits immune-dependent anti-tumor activit" in multiple s"ngeneic models via an immune-dependent mechanism MOUSE COLON MOUSE SARCOMA l m u n o c o m p r o m i s e d m i c e 1 5 0 0 1 5 0 0 8 0 0 1 0 0 0 6 0 0 1 0 0 0 4 0 0 5 0 0 5 0 0 2 0 0 0 0 5 1 0 1 5 0 5 1 0 1 5 8 1 0 1 4 D y s 1 6 1 8
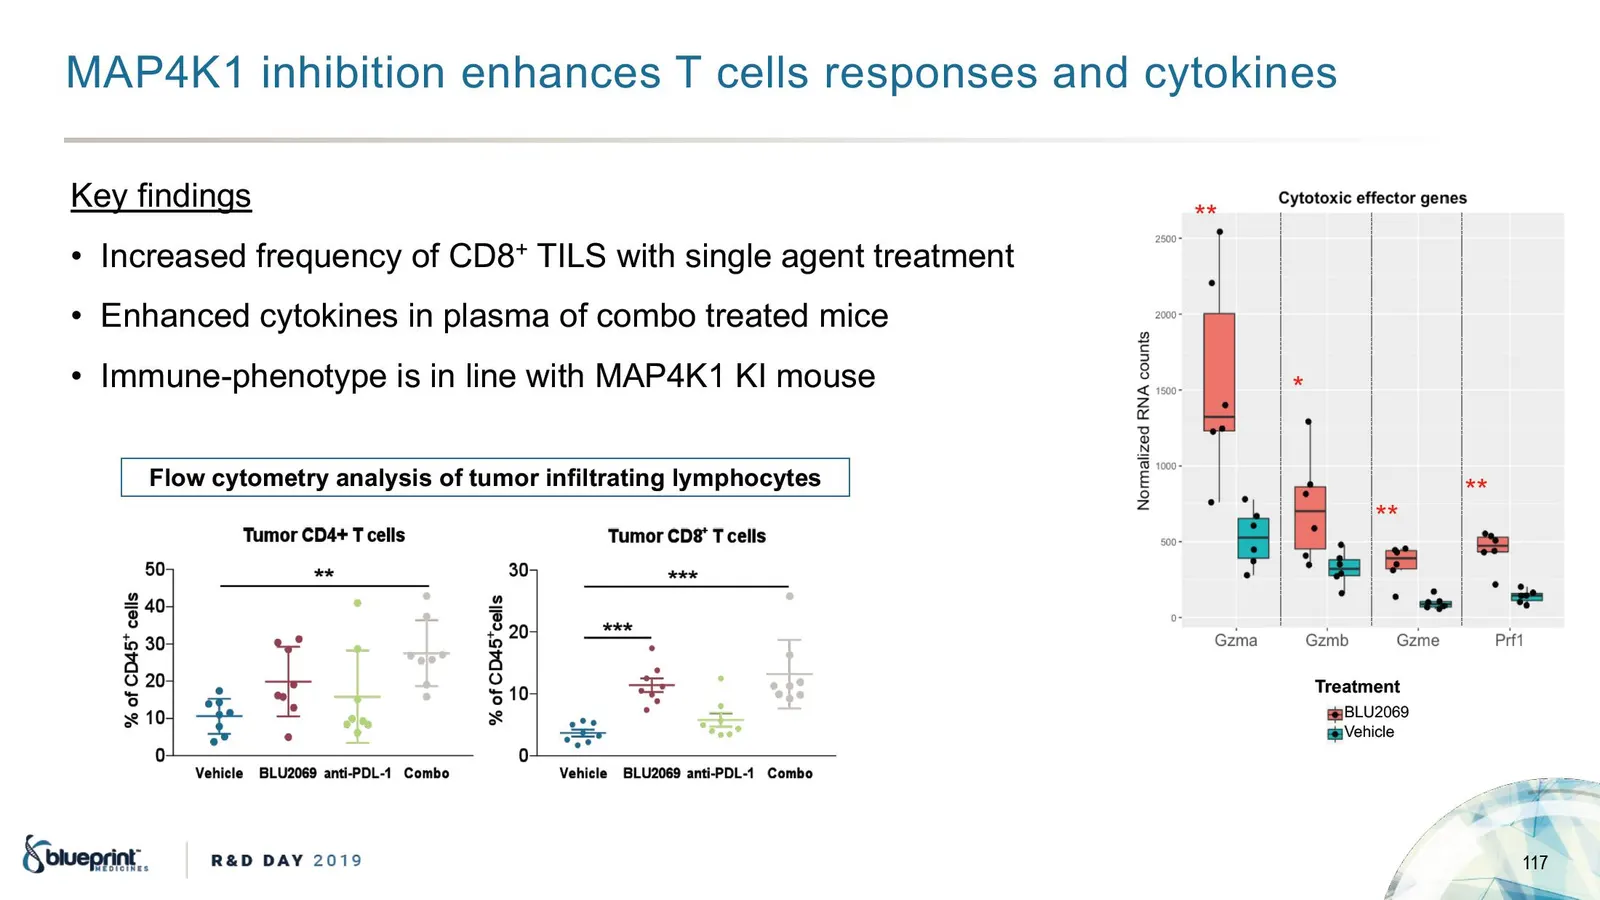
Slide 117: MAP4K1 inhibition enhances T cell responses
MAP4K1 "&!"b","'& e&!a&ce+ T ce$$+ *e+('&+e+ a&d c/,'#"&e+ Ke/ f"&d"& + ** I&c*ea+ed f*e)-e&c/ 'f CDB+ TILS .",! +"& 0 0 0 $e a e&, ,*ea,%e&, E&!a&ced c/,'#"&e+ "& ($a+%a 'f c'%b' ,*ea,ed %"ce I%%-&e-(!e&',/(e "+ "& $"&e .",! MAP4K1 KI %'-+e * ** ** Treatment BLU2069 Ve!"c$e 117 Flow cytometry analy
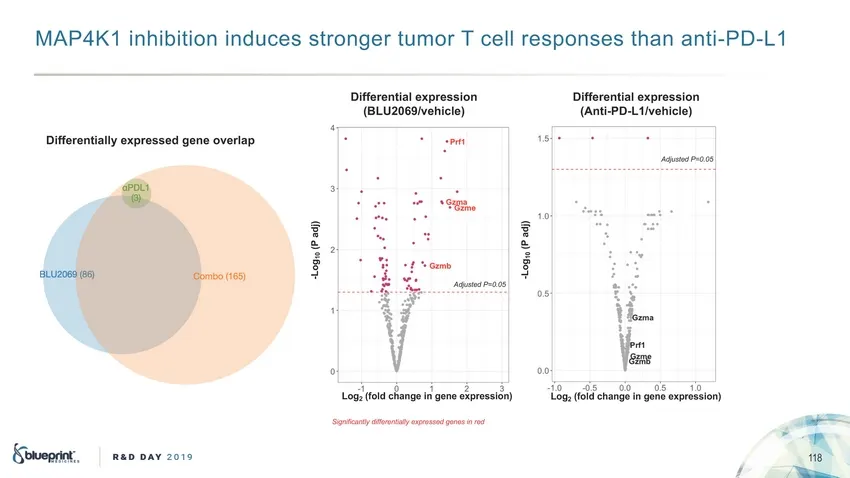
Slide 118: MAP4K1 inhibition induces stronger tumor T cell responses than anti-PD-L1
MAP4K1 nh b t on nduces stronger tumor T cell responses than ant -PO-L1 Differen ial e"pression (BLU2069/!ehicle) Differen ial e"pression (An i-PD-L1/!ehicle) Differen iall# e"pressed gene o!erlap Ad usted p::0 05 Ad usted p::0 05 Log2 (fold change in gene e"pression) Log2 (fold change in gene e"pre
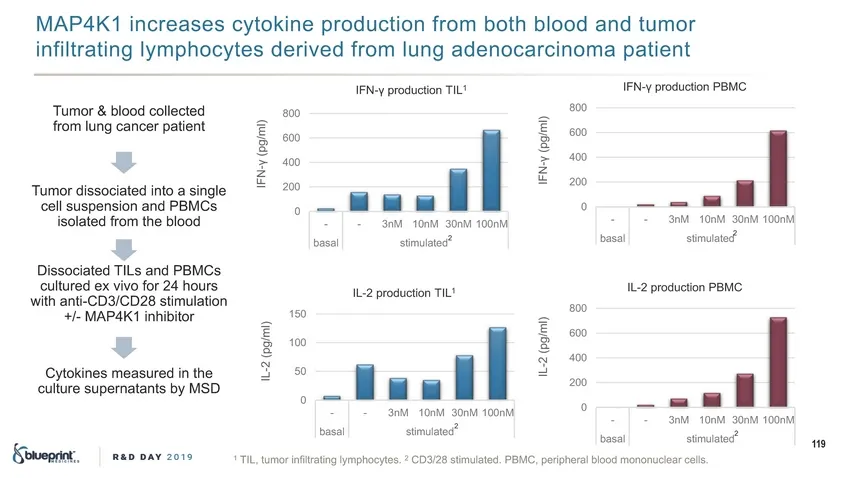
Slide 119: MAP4K1 inhibition in human blood and tumor samples
MAP4K1 $(c+ a, , c2-)%$( *+)d.c-$)( !+)' b)-# b&))d a(d -.')+ $(!$&-+a-$(" &2'*#)c2-, d +$/ d !+)' &.(" ad ()ca+c$()'a *a-$ (-IFN production PBMC FN-y product on T L1 800 T.')+ & b&))d c)&&c-d !+)' &.(" ca(c+ *a-$(-800 600 600 400 400 200 200 T.')+ d$,,)c$a-d $(-) a ,$("& c&& ,.,*(,$)( a(d PBMC, 0 0

Slide 120: Diverse portfolio of cancer immunotherapy targets
Uniq"e and di#er e por!folio of no#el cancer imm"no!herap% !arge! & MAP4K1 pa!h !o de#elopmen! candida!e i repre en!a!i#e of !he broader "ndi clo ed cancer imm"no!herap% por!folio "nder !he Roche collabora!ion ► Plan !o nomina!e po!en!ial fir candida!e in 1H 2020 !-in-cla MAP4K1 de#elopmen! & Collab

Slide 121: Our platform: high success rate, efficiency, expansion
O+*$&&# &( *!e +*+(e HIGH SUCCESS RATE - EFFICIENCY - PLATFORM EXPANSION 121 GIST 'a*"e%* ,")"* @ B$+e'("%* Med"c"%e), 2019.

Slide 122: Q & A
Q & A

Slide 123: Closing remarks - Jeff Albers
Jeff Albers r e m a r k s Chief Executive Officer
Slide 124: Third quarter 2019 financial highlights
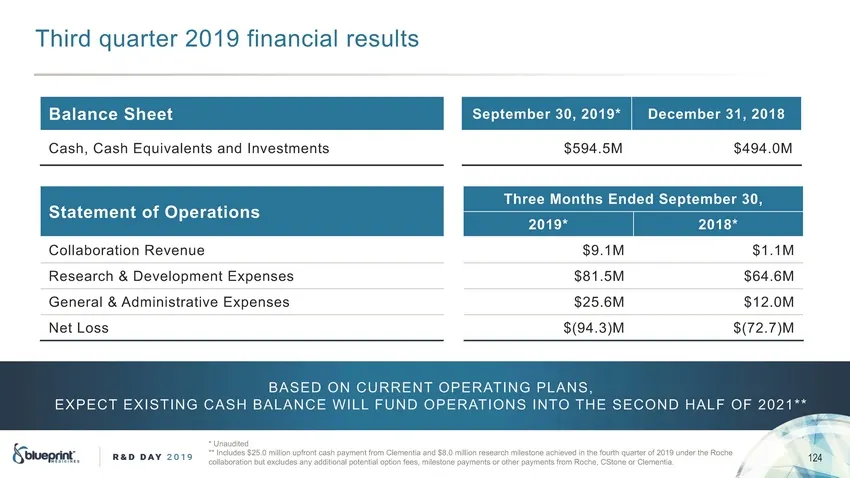
#-.5* 48'57+5 2019 ,.1'1).'/ 5+68/76 BA"ED ON C$!!EN# O E! A# ING LAN", E& EC# E&I"#ING CA"H BALANCE %ILL F$ND O E! A# ION" IN#O # HE "ECO ND HAL F O F 2 0 2 1 * * * $1'8*.7+* ** I1)/8*+6 $25.0 0.//.21 83,5217 )'6-3';0+17 ,520 C/+0+17.' '1* $8.0 0.//.21 5+6+'5)-0./+6721+ ')-.+9+* .1 7-+ ,2857-48'57+
Slide 125: Pursuing a high-impact approach across our portfolio
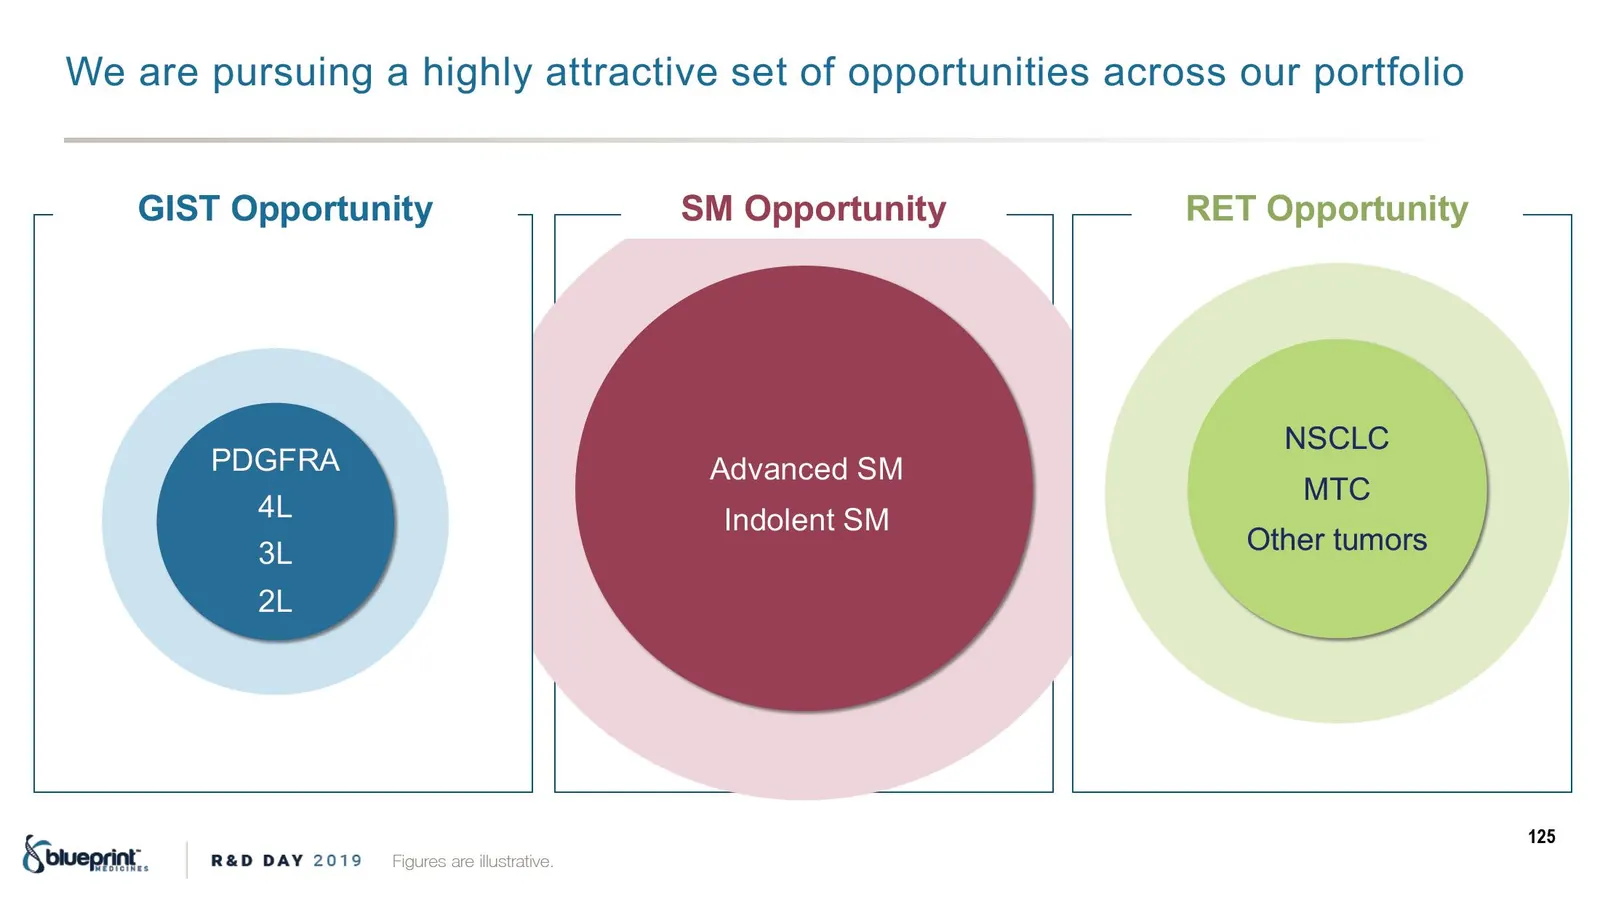
We a!e $!"$ ng a h gh & a##!ac# %e "e# of o o!#$n # e" ac!o"" o$! o!#fo o GIST Opportunity SM Opportunity RET Opportunity NSCLC M0TC O#he! #$mo!" PDGFRA 4aL 3L 2L Ad%anced SM Indo en# SM 125 Figures are illustrative.
Slide 126: Pipeline
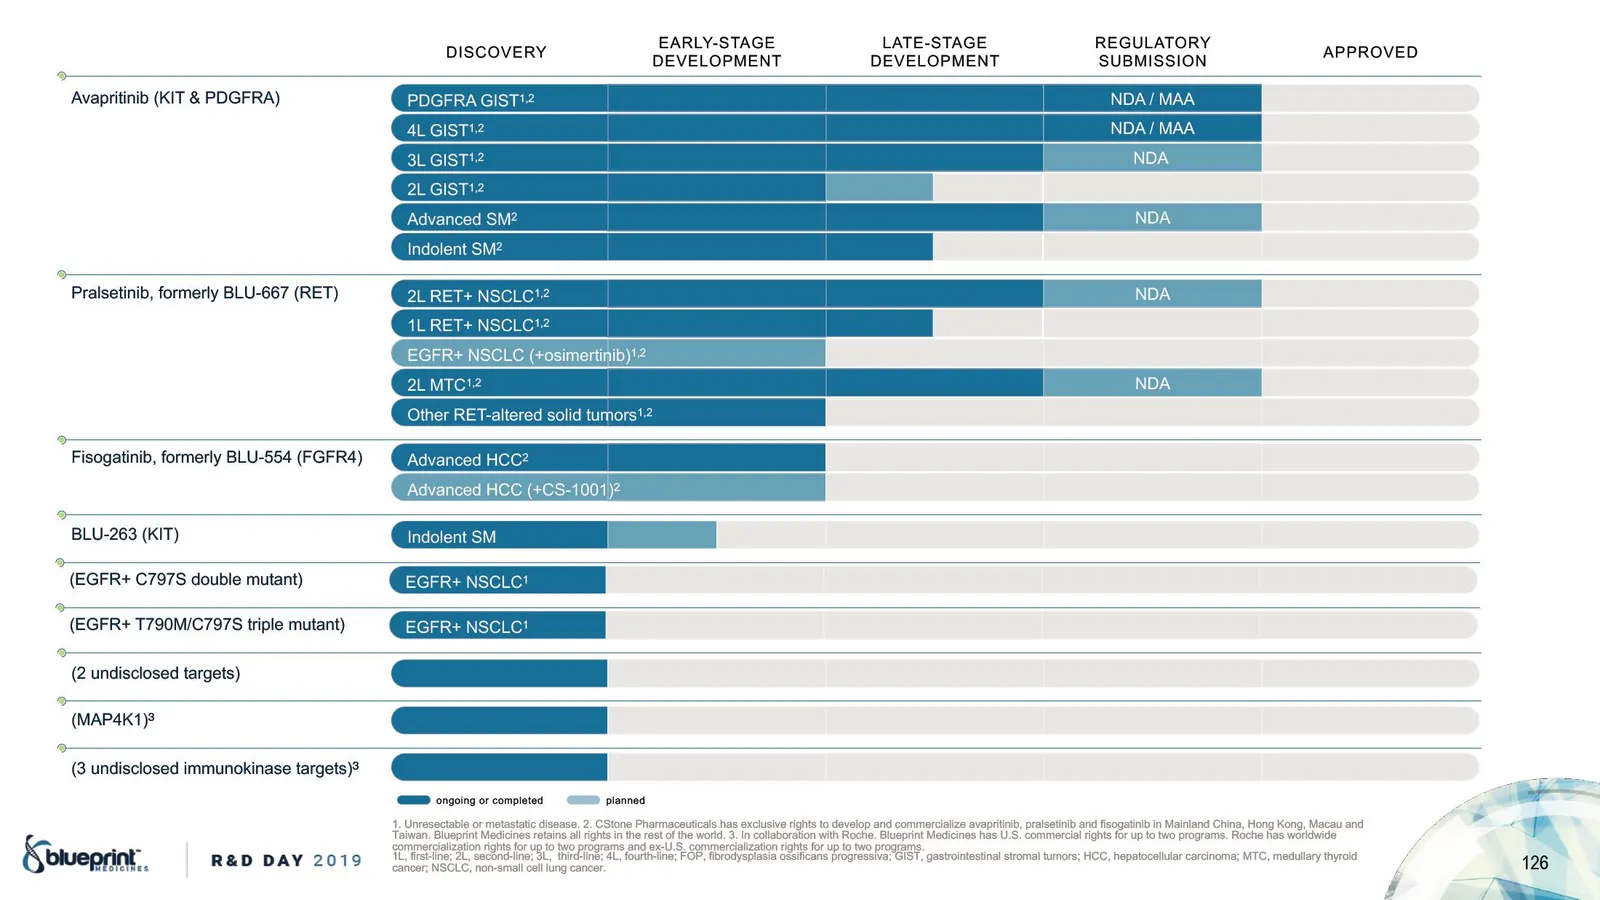
EA#L(-$ %A GE LA%E-$ %A GE DE'EL!"ME #EG&LA%! #( $&BMI$$I! DI$C!'E#( A""#!'ED DE'EL!"ME % % A<)781:151* (KI% & "DGF#A) "DGF#A GI$%1,2 4L GI$%1,2 3L GI$%1,2 2L GI$%1,2 A,<)5+-, $M2 I5,63-5: $M2 "8)39-:151*, .684-83? BL&-667 (#E%) 2L #E%+ $CLC1,2 1L #E%+ $CLC1,2 EGF#+ $CLC (+6914-8:151*)1,2 2L M%C1,2

Slide 127: Thank you
thank you
Source: SEC EDGAR · 8-K filed Nov 5, 2019
More decks from Blueprint Medicines Corp
 Q1 2025 Earnings Presentation14 slides · May 1, 2025
 Q4 2024 Earnings Presentation12 slides · Feb 13, 2025
 J.P. Morgan Healthcare Conference 202525 slides · Jan 13, 2025
 Technical Presentation (April 2024)19 slides · Apr 25, 2024
 J.P. Morgan Healthcare Conference 202425 slides · Jan 8, 2024
 AAAAI 2023 Annual Meeting35 slides · Feb 27, 2023